Related Experiment Video
Updated: Jan 8, 2026
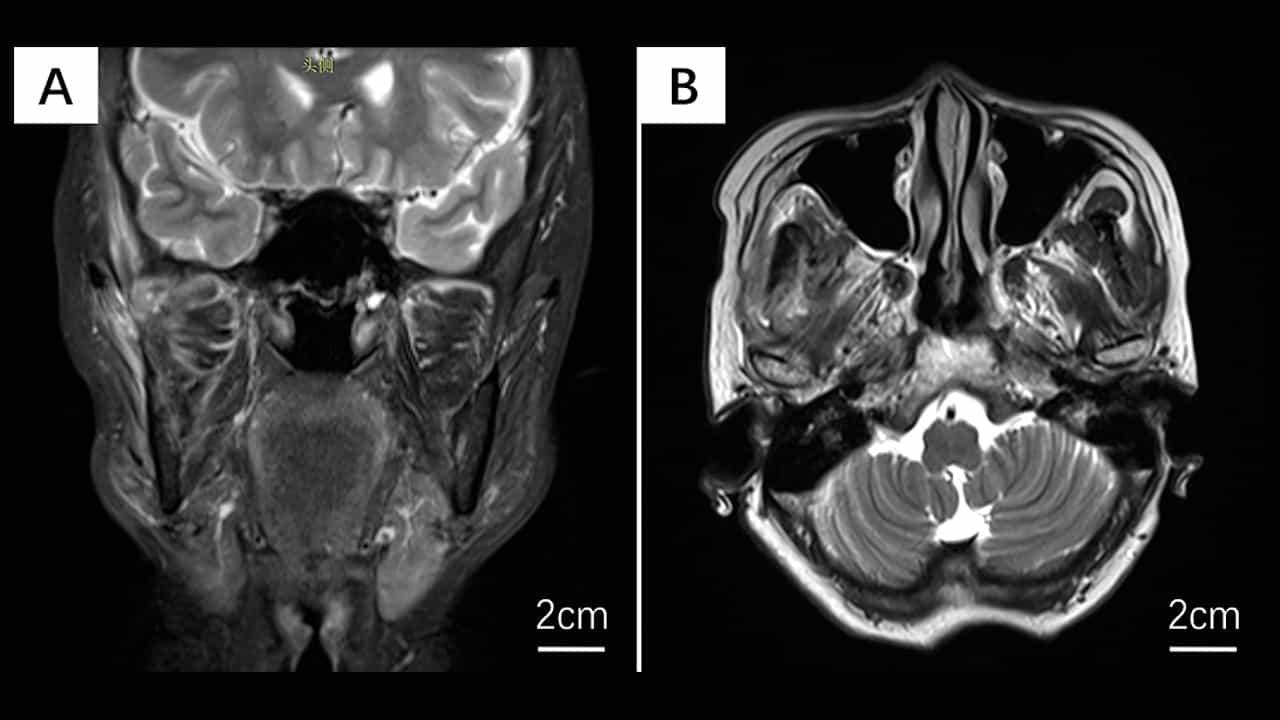

Lateral Molar Approach-Driven Transoral Endoscopic Procedure for Benign Infratemporal Fossa Tumor Resection
Published on: August 15, 2025
Facial Nerve Outcomes After Infratemporal Fossa Approach Type A With Anterior Rerouting for Class C-D Tympanojugular
Yi Sun1,2, Giuseppe Fancello2,3, Melcol Hailu Yilala2,4
1Department of Otorhinolaryngology, Head and Neck Surgery, The Second Affiliated Hospital of Anhui Medical University, Hefei, China.

Objectives:
To analyze the facial nerve outcomes after removing the infratemporal fossa approach type A (IFTA) with anterior rerouting for class C-D tympanojugular paragangliomas (TJPs).
Methods:
We evaluated the medical records and follow-up visits of patients with class C-D TJPs treated with IFTA between 1989 and 2023 at 2 quaternary referral institutions.
Results:
Of the 258 patients surgically treated for modified Fisch Class C-D TJPs, 154 cases were selected based on the selection criteria: 29 (18.8%) patients were classified as having a Class C1 TJP, while 86 (55.8%) had a Class C2 and 39 (25.3%) had a Class C3-4 TJP. Among the included subjects, 146/154 (94.81%) had normal-to-moderately impaired (grades I-II and III) facial nerve function at the last follow-up, including 27/29 (93.1%) patients with C1 TJPs, 81/86 (94.19%) patients with C2 TJPs, and 38/39 (97.44%) patients with C3-4 TJPs. Total tumor removal was achieved in 25 out of 29 (86.2%) patients with C1 TJPs, 67 out of 86 (77.9%) patients with C2 TJPs, and 31 out of 39 (79.5%) patients with C3-4 TJPs.
Conclusions:
The main goal of TJP treatment is complete tumor removal, especially in young patients with a higher expected lifespan. IFTA is an appropriate approach for the resection of class C-D TJPs. With anterior rerouting of the facial nerve, adequate exposure to the jugular foramen, infralabyrinthine areas, and intratemporal internal carotid artery minimizes morbidity and avoids mortality. Postoperative facial asymmetry, mostly of recovery to grade I-II and III, is the price paid to achieve a higher total tumor resection rate and a lower rate of recurrence and complications.