Related Experiment Video
Updated: Jan 8, 2026
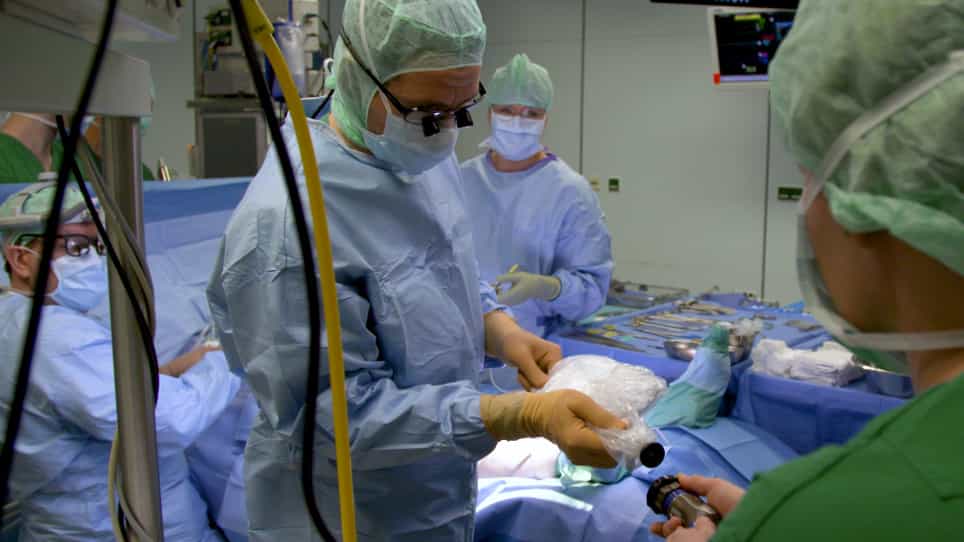

Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
Techniques for harvesting the saphenous vein in coronary artery bypass grafting: a network systematic review and
Chuang Liu1,2,3, Ming-Xuan Zhang4, Xin-Liang Guan1,2,3
1Department of Cardiovascular Surgery, Beijing An Zhen Hospital, Capital Medical University, Beijing, China.

Insights
No-touch vein harvesting (NT) reduces graft failure and occlusion in coronary artery bypass grafting (CABG). However, NT has higher leg wound infection rates compared to open or endoscopic vein harvesting, with similar mortality outcomes.
Area of Science:
- Cardiovascular Surgery
- Vascular Surgery
- Surgical Techniques
Background:
- Coronary artery bypass grafting (CABG) is a critical procedure for treating coronary artery disease.
- The saphenous vein graft (SVG) is commonly used, but its long-term patency is influenced by harvesting technique.
- Optimal SVG harvesting methods, including open vein harvesting (OVH), endoscopic vein harvesting (EVH), and no-touch vein harvesting (NT), are debated.
Purpose of the Study:
- To compare the efficacy of OVH, EVH, and NT techniques for SVG harvesting in CABG.
- To evaluate the impact of different harvesting methods on key clinical outcomes using a network meta-analysis.
Main Methods:
- A systematic search of randomized controlled trials (RCTs) was conducted in PubMed, Web of Science, and the Cochrane Central Registry.
- Data from 26 RCTs involving 7254 patients were analyzed.
- Outcomes assessed included graft failure, graft occlusion, mortality, revascularization, myocardial infarction (MI), and leg wound infection rates.
Main Results:
- No-touch vein harvesting (NT) demonstrated significantly lower graft failure rates compared to OVH and EVH.
- NT also showed significantly lower graft occlusion rates than OVH.
- Conversely, NT was associated with the highest leg wound infection rate among the three techniques.
Conclusions:
- No-touch vein harvesting (NT) offers superior long-term graft patency by reducing failure and occlusion.
- The increased risk of leg wound infection with NT requires careful consideration and management.
- Surgeons must balance the benefits of improved graft longevity against potential harvest site complications.
Objective:
The optimal technique for harvesting the saphenous vein (SVG) in coronary artery bypass grafting (CABG) remains undetermined. This study aimed to assess the efficacy of open vein harvesting (OVH), endoscopic vein harvesting (EVH) and no-touch vein harvesting (NT) in CABG using a network meta-analysis of randomised controlled trials (RCTs).
Methods:
RCTs evaluating the outcomes in patients undergoing CABG with the SVG using OVH, EVH or NT were identified through a systematic search of PubMed, Web of Science and the Cochrane Central Registry up to August 2025. The outcomes analysed included graft failure, graft occlusion, mortality, revascularisation, myocardial infarction (MI) and leg wound infection rates.
Results:
Data from 26 RCTs involving 7254 patients meeting the inclusion criteria were analysed. The network meta-analysis indicated that the graft failure rate in the NT group was significantly lower than in the OVH group (relative risk (RR) 0.62; 95% CI 0.40 to 0.96) and the EVH group (RR 0.41; 95% CI 0.21 to 0.80). The graft occlusion rate in the NT group was significantly lower than in the OVH group (RR 0.66, 95% CI 0.52 to 0.84). However, the leg wound infection rate in the NT group was the highest. No significant differences were observed in mortality, revascularisation and MI rates among the three groups.
Conclusion:
NT was associated with lower graft failure and graft occlusion rates, yet it had higher leg wound infection rates, while mortality, revascularisation and MI rates remained comparable among the three techniques. These findings require cautious interpretation, and it is important to balance harvest site complications and the desirability of long-term graft patency.


