Related Experiment Video
Updated: Jan 7, 2026
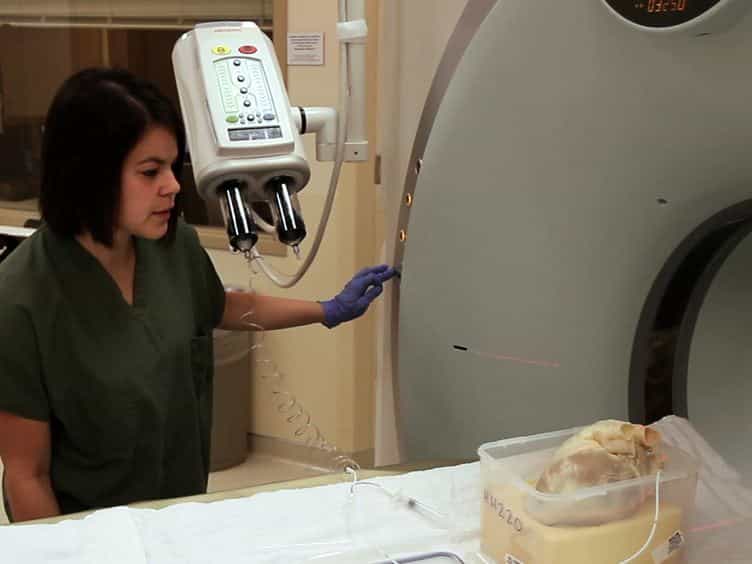

Anatomical Reconstructions of the Human Cardiac Venous System using Contrast-computed Tomography of Perfusion-fixed Specimens
Published on: April 18, 2013
Feasibility of estimating cardiac indices using cardiac surgery anesthesia records in a multicenter cohort
Emily A Balczewski1,2, Graciela Mentz3, Karandeep Singh4,5
1Medical Scientist Training Program, University of Michigan Medical School, Ann Arbor, MI, USA.

Insights
Estimating cardiac index (CI) in cardiac surgery patients using routine data is possible for population studies. However, this method has limited accuracy for identifying individual patients with low CI.
Area of Science:
- Anesthesiology
- Cardiovascular Physiology
- Medical Informatics
Background:
- Cardiac index (CI) is crucial for assessing end-organ perfusion in cardiac surgery.
- Routine CI measurement is not universally applied, necessitating accurate estimation methods.
Purpose of the Study:
- To evaluate the accuracy of estimating CI using routine perioperative data.
- To assess the reliability of these estimates in identifying low CI in adult cardiac surgical patients.
Main Methods:
- Analysis of anesthesia records from 5,989 adult cardiac surgery patients with thermodilution CI.
- Application of four published formulas using blood pressure and heart rate, adjusted for patient and procedural factors.
- Bland-Altman analysis and Cohen's kappa for concordance and classification accuracy.
Main Results:
- The Liljestrand and Zander formula showed mean absolute errors of 0.45-0.47 L/min/m².
- Classification accuracy for low CI was limited (Cohen's kappa 0.26 pre-bypass, 0.20 post-bypass).
- Adjusted estimates provide population-level CI data but lack individual precision.
Conclusions:
- Routinely collected perioperative data can generate population-level CI estimates in cardiac surgery.
- Individual-level identification of low CI using these estimation methods is currently limited.
- Findings support the use of adjusted CI estimates for large-scale perioperative hemodynamic research.
Abstract:
Cardiac index (CI) is a key physiologic indicator correlated with end-organ perfusion in cardiac surgical patients, yet it is not routinely measured in all cases. This study evaluated the accuracy of estimating CI using routinely available physiologic monitor data, adjusted for relevant patient, physiologic, and procedural factors documented in perioperative anesthesia records. We analyzed anesthesia records from adult cardiac surgical patients with thermodilution-based CI measurements across seven US hospitals from 2014 to 2022. Four published formulas-based on intraoperative blood pressure and heart rate-were used to estimate CI in generalized linear models, with adjustment for perioperative patient and procedure characteristics. Bland-Altman analysis compared adjusted CI estimates to reference thermodilution CI values. The ability of each estimator to classify patients with low CI (< 2.2 L/min/m²) was assessed for concordance. In a cohort of 5,989 patients, the median (IQR = interquartile range) thermodilution-based CIs were 2.1 (1.8-2.6) and 2.4 (2.0-2.9) L/min/m² before and after cardiopulmonary bypass, respectively. The best-performing formula, Liljestrand and Zander, achieved mean absolute errors of 0.45 and 0.47 L/min/m² before and after bypass, respectively. However, its reliability in classifying low CI was limited (Cohen's kappa = 0.26 pre-bypass, 0.20 post-bypass). Routinely collected physiologic and patient data can be used to generate population-level cardiac index estimates in adult cardiac surgery patients when appropriately adjusted, though individual-level discrimination of low CI is limited. These findings inform future large-scale perioperative hemodynamic research.


