Related Experiment Video
Updated: Jan 7, 2026

Author Spotlight: Development of a Minimally Invasive Large-Animal Model for Reliable and Reproducible Cardiovascular Research
Published on: October 20, 2023
Acute effects of aerobic exercise on aortic wall stress in thoracic aortic disease
Rachel J Skow1, Stephen J Foulkes1,2, Richard B Thompson3
1Integrated Cardiovascular Exercise Physiology and Rehabilitation (iCARE) Laboratory, Faculty of Nursing, College of Health Sciences, University of Alberta, Edmonton, Alberta, Canada.

Abstract:
Patients with thoracic aortic disease (TAD; aneurysm and dissection) with well-controlled blood pressure are recommended to perform regular aerobic exercise of light-to-moderate intensity; however, the biomechanical impact on the aortic wall remains unknown. The aim of this study was to quantify aortic wall stress (AWS) and aortic mechanical efficiency [AME; AWS normalized to cardiac output (Qc)] during aerobic exercise in individuals with TAD. Fourteen participants with stable TAD (3 females, age 69 ± 9 yr; 8 with unrepaired aneurysms) and 11 age-matched controls (CON, 4 females, age 68 ± 7 yr) underwent comprehensive cardiac and aortic evaluation using magnetic resonance imaging. Assessments included Qc and aortic structural parameters (diameter and wall thickness), measured both at rest and during light-to-moderate intensity stepping exercise. Ascending AWS increased in response to light-to-moderate intensity exercise across both groups (P < 0.01), with no significant group-by-exercise interaction effect (P = 0.793). A similar pattern was observed in the descending aorta. Importantly, all AWS values measured during exercise remained below the established threshold for aneurysmal rupture (850-1,200 kPa), with the maximum recorded value being 323 kPa. Patients with TAD tended to exhibit lower AME (higher AWS/Qc slopes) in the ascending aorta (16.8 ± 12.8 vs. 9.2 ± 4.0 kPa/L/min; P = 0.062) but not in the descending aorta (P = 0.119). Our study provides new evidence to support the physical activity guidelines for people with aortic disease participating in moderate-intensity aerobic exercise. By integrating individual risk profiles with biomechanical data, we can continue to advance clinical understanding of safe and effective exercise in this population.NEW & NOTEWORTHY Patients with thoracic aortic disease (n = 14) did not show elevated aortic wall stress compared with age-matched controls (n = 11) during exercise. Aortic mechanical efficiency (increase in aortic wall stress relative to increase in cardiac output during exercise) may be impaired in patients with thoracic aortic disease. All exercise-induced aortic wall stress values remained well below the aneurysmal rupture threshold (800-1,200 kPa).


Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:26
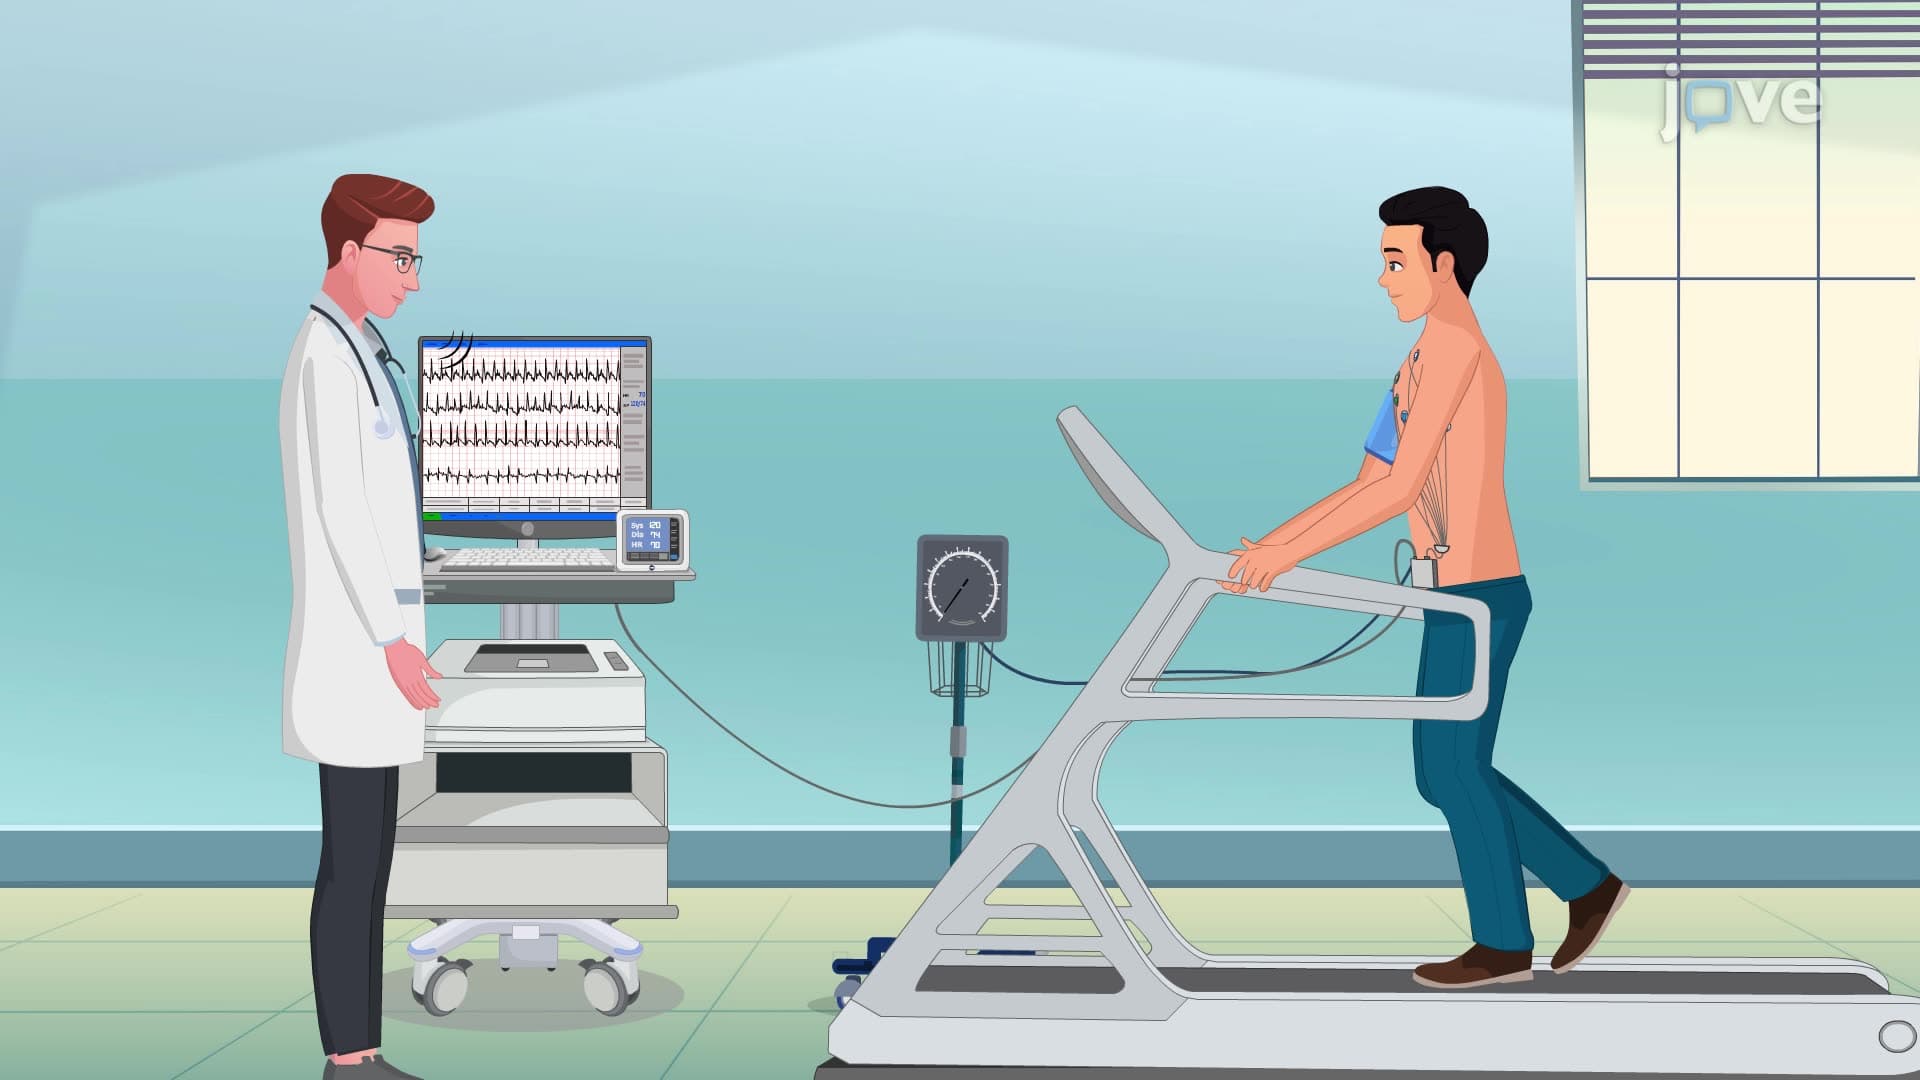
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:25
Aortic Regurgitation III: Medical Management
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...