Related Experiment Video
Updated: Jan 7, 2026
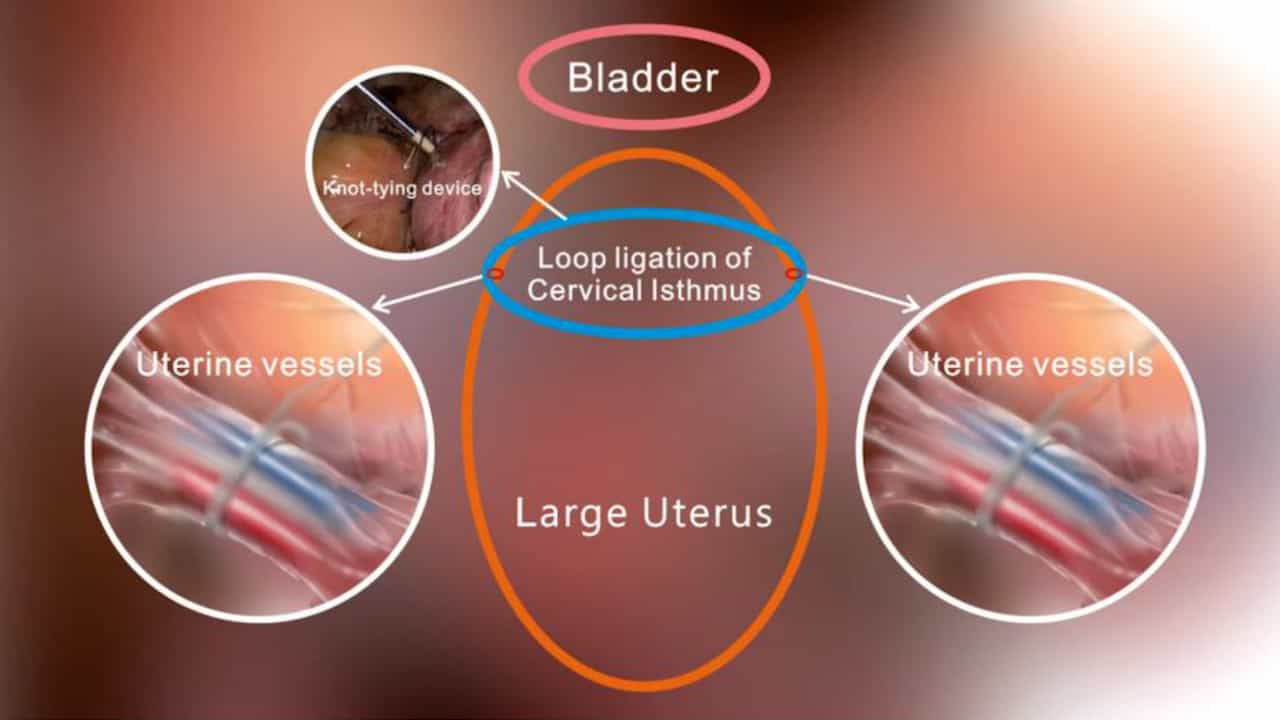
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Uterus-preserving surgery for diffuse adenomyosis via transumbilical single-port laparoscopy: combining dual-flap
Yunlei Cao1, Jialin Tian1, Xishi Liu1
1Obstetrics & Gynecology Hospital of Fudan University, Shanghai Key Lab of Reproduction and Development, Shanghai Key Lab of Female Reproductive Endocrine Related Diseases, Shanghai 200433, People's Republic of China.

Objective:
To present an innovative approach of transumbilical single-port laparoscopic adenomyomectomy using the double-flap method combined with transient bilateral uterine artery occlusion, specifically for patients desiring uterine preservation.
Design:
A narrated video demonstrating the surgical technique in four steps.
Subjects:
A 42-year-old female with diffuse adenomyosis, moderate anemia, and a desire to preserve the uterus.
Exposure:
The procedure was conducted via a transumbilical single-port laparoscopic approach. A 2.5-cm umbilical incision was made for inserting a single-port device, through which both the laparoscope and surgical instruments were introduced (Fig. 1). Intraoperatively, bilateral uterine arteries were temporarily occluded with bulldog clamps, and adenomyomectomy was performed using the double-flap technique. Initially, methylthioninium was administered into the uterine cavity to facilitate delineation of the uterine horns, cavity, and fallopian tube openings. A midline incision was made on the anterior uterine serosa and extended sagittally to the uterine cavity, then continued along the fundus and posterior uterine wall to the lesion margin. Adenomyotic tissue was meticulously excised, with a 0.5-1-cm myometrial layer preserved beneath the serosa and above the endometrium to avoid injury to the serosa, fallopian tube openings, and endometrium. After excising the lesions, the uterine cavity was sutured closed, and the uterine myometrium was reconstructed via the double-flap technique to restore the uterus to its normal anatomical structure.
Main Outcome Measures:
Perioperative blood loss, operative duration, anatomical restoration, symptom relief, and maintenance of normal uterine anatomy.
Results:
Intraoperative blood loss was 50 mL, and the procedure lasted 75 minutes. Postoperatively, the patient's symptoms improved markedly; her dysmenorrhea visual analogue scale score dropped from 7 to 2, anemia resolved within 3 months, and uterine size reduced from 8×8×7 cm to 5×5×4 cm. Postoperative 3-month magnetic resonance imaging showed restoration of the normal morphology of the uterine cavity (Fig. 2).
Conclusion:
Compared with traditional laparoscopy, single-port laparoscopy is less invasive without significantly prolonging operative time. Temporary uterine artery occlusion effectively reduces intraoperative blood loss and perioperative transfusion needs, especially in anemic patients. The double-flap technique maximizes adenomyotic lesion resection while preserving normal uterine anatomy, making this integrated approach a promising uterus-preserving option for adenomyosis patients.