Related Experiment Video
Updated: Jul 9, 2026
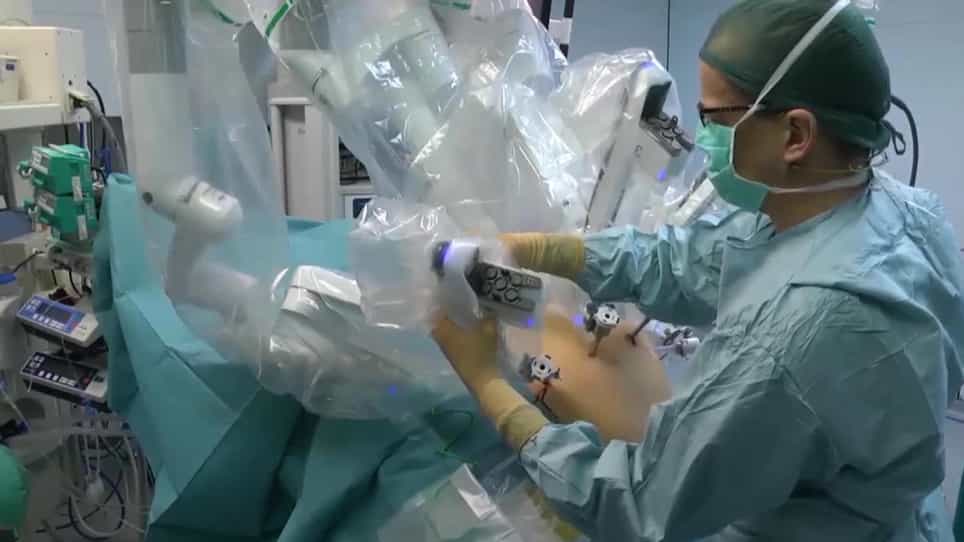
Robot-Assisted Radical Antegrade Modular Pancreatosplenectomy Including Resection and Reconstruction of the Spleno-Mesenteric Junction
Published on: January 3, 2020
[Comparison of adjuvant S-1 plus gemcitabine with S-1 monotherapy for pancreatic adenocarcinoma: real-world data]
1Department of Medical Oncology, Chinese Academy of Medical Sciences & Peking Union Medical College Peking Union Medical College Hospital, Beijing 100730, China Department of Internal Medicine, Chinese Academy of Medical Sciences & Peking Union Medical College Peking Union Medical College Hospital, Beijing 100730, China.

Abstract:
Objective: The optimal adjuvant treatment regimen for pancreatic cancer after surgery remains undetermined. This study aimed to compare the efficacy and safety of S-1 combined with gemcitabine (GS) versus S-1 monotherapy in adjuvant therapy for pancreatic cancer. Methods: A retrospective analysis was conducted on postoperative pancreatic ductal adenocarcinoma (PDAC) patients who received GS or S-1 adjuvant chemotherapy at Peking Union Medical College Hospital from March 2016 to September 2024. Clinicalopathological characteristics, molecular features, treatment details, efficacy outcomes, and toxicity data were collected via electronic medical records and telephone follow-up. Results: A total of 454 patients were included, with 313 receiving GS and 141 receiving S-1. GS-treated patients were generally younger (median age: 62 vs. 66 years, P<0.001). The median disease-free survival (DFS, 15.4 vs. 12.5 months, P=0.150) and overall survival (OS, 33.5 vs. 24.7 months, P=0.150) showed trends toward prolongation in the GS group compared with the S-1 group. In CA19-9-positive patients prior to adjuvant chemotherapy, GS therapy significantly prolonged DFS (10.7 vs. 8.8 months, P=0.040) and OS (28.2 vs. 19.8 months, P=0.003) compared with S-1 monotherapy. However, the GS group had a higher incidence of grade ≥3 adverse events [59.3%(128/216) vs. 39.4%(26/66), P=0.007], particularly neutropenia [40.7%(88/216) vs. 19.7%(13/66), P=0.003] and fatigue [19.0%(41/216) vs. 7.6%(5/66), P=0.045]. Molecular analysis revealed that TP53 gene variants may predict poor survival outcomes, but no association was observed between homologous recombination repair-related gene variants and treatment efficacy of GS or S-1. Conclusions: GS adjuvant therapy demonstrates trends toward improved DFS and OS compared with S-1 monotherapy in postoperative pancreatic cancer patients, though without statistical significance. GS was superior to S-1 in CA19-9-positive patients. The correlation between genetic mutation profiles and adjuvant treatment outcomes in pancreatic cancer requires further exploration.


