Related Experiment Video
Updated: Jan 7, 2026
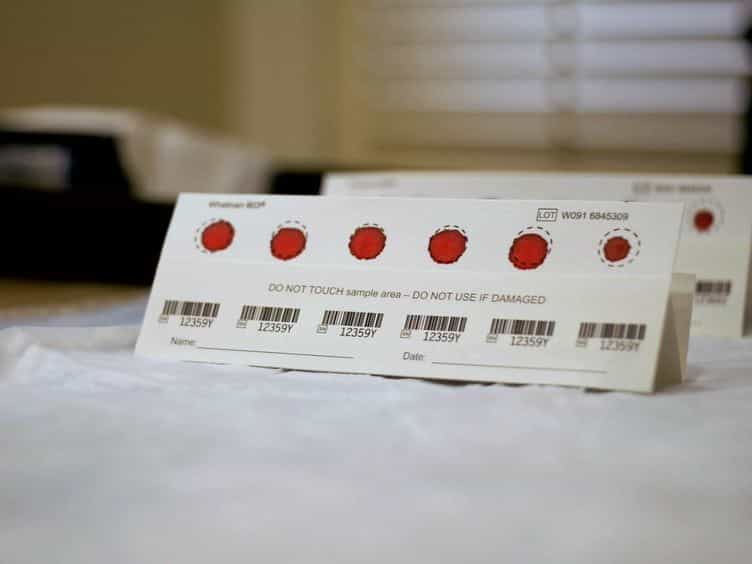

Dried Blood Spot Collection of Health Biomarkers to Maximize Participation in Population Studies
Published on: January 28, 2014
Biomarkers
Fuqiang Gao1, Joel Ramirez2,3, Melissa F Holmes1
1Dr. Sandra Black Centre for Brain Resilience and Recovery, Sunnybrook Research Institute, Toronto, ON, Canada.

Background:
The origin of MRI focal white matter hyperintensities (fWMH) is not fully understood. Recent evidence suggests the perivascular surface of arterioles and venules may serve as cerebral lymphatics for homeostasis of interstitial fluid and toxic metabolite clearance. This system could be injured by age-related vascular wall damage, particularly venous collagenosis in Alzheimer's disease (AD), where fWMH could be an early marker of this injury. We investigated whether fWMH spatially co-localize with deep medullary vessels (DMV), and change dynamically reflecting vasogenic edema.
Method:
107 AD and 30 controls (age=74) were included with baseline and follow-up MRI. fWMH were foci <10mm on T2/FLAIR. DMVs were linear visible streaks on T1, invert-T2 or SWI. T2/FLAIR was co-registered to T1 space. The spatial relationship of each fWMH with DMV was classified as either 'perivascular positive' if an fWMH was overlapped/centered by a DMV or otherwise as 'perivascular negative'. Each fWMH was followed for change over time in 70 AD and 19 controls. We reasoned that fWMH would exhibit dynamic change if they reflect vasogenic edema.
Result:
At the baseline, 1630 fWMH were identified, with 91.6% perivascular positive. They distributed mostly in the frontal (60.2%) and occipitoparietal (32.2%) region, along the angles of the lateral ventricles, areas with highest distribution of intramedullary venules, suggesting perivenular distribution. In follow-up, 1098 fWMH showed change over time. 1019 (92.8%) of 1098 fWMH were perivascular positive with 8.5% decreased, 31.9% increased and 59.6% unchanged over 1.5 years. AD had a higher rate of fWMH increase (χ2=6.23, p = 0.012), while controls had a higher rate of fWMH unchanged over time (χ2=5.16, p = 0.023). Most DMVs connected to lateral ventricles and had trans-cerebral features, consistent with intramedullary veins. Small venular infarctions were sometimes observed.
Conclusion:
Most fWMH were distributed along DMVs, particularly. Their dynamic progression was compatible with being fluid in nature and not necessarily indicative of ischemiaas previously thought. fWMH could relate to multiple underlying pathologies, but venous insufficiency of deep intramedullary venules may be an important substrate of fWMH in AD and aging.
Insights
Focal white matter hyperintensities (fWMH) are primarily located near deep medullary vessels (DMVs), suggesting a connection to venous insufficiency in Alzheimer's disease (AD) and aging. These fWMH appear fluid-like and may indicate early vascular changes.
Area of Science:
- Neuroimaging
- Cerebrovascular Health
- Alzheimer's Disease Research
Background:
- The origin of focal white matter hyperintensities (fWMH) on MRI remains unclear.
- Emerging evidence points to perivascular spaces as cerebral lymphatics, potentially affected by vascular aging and Alzheimer's disease (AD).
- fWMH may serve as early indicators of venous collagenosis and lymphatic dysfunction in AD.
Purpose of the Study:
- To investigate the spatial co-localization of fWMH with deep medullary vessels (DMVs).
- To assess the dynamic changes of fWMH over time to understand their nature.
- To explore the relationship between fWMH, DMVs, and potential vasogenic edema in AD and aging.
Main Methods:
- 107 AD patients and 30 controls underwent baseline and follow-up MRI scans.
- fWMH were identified on T2/FLAIR images; DMVs were visualized on T1, invert-T2, or SWI sequences.
- Spatial relationships were classified as 'perivascular positive' or 'perivascular negative', and fWMH changes were tracked over 1.5 years.
Main Results:
- 91.6% of baseline fWMH were perivascular positive, predominantly in frontal and occipitoparietal regions along lateral ventricles.
- Follow-up revealed dynamic changes in 92.8% of fWMH, with most remaining perivascular positive.
- AD patients showed a higher rate of fWMH increase compared to controls, who had more unchanged fWMH.
Conclusions:
- The majority of fWMH are located along DMVs and exhibit fluid-like dynamic changes.
- fWMH progression suggests a role beyond ischemia, potentially linked to venous insufficiency in deep medullary venules.
- Venous insufficiency may be a significant underlying pathology for fWMH in AD and aging populations.


Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...