Related Experiment Video
Updated: Jan 7, 2026
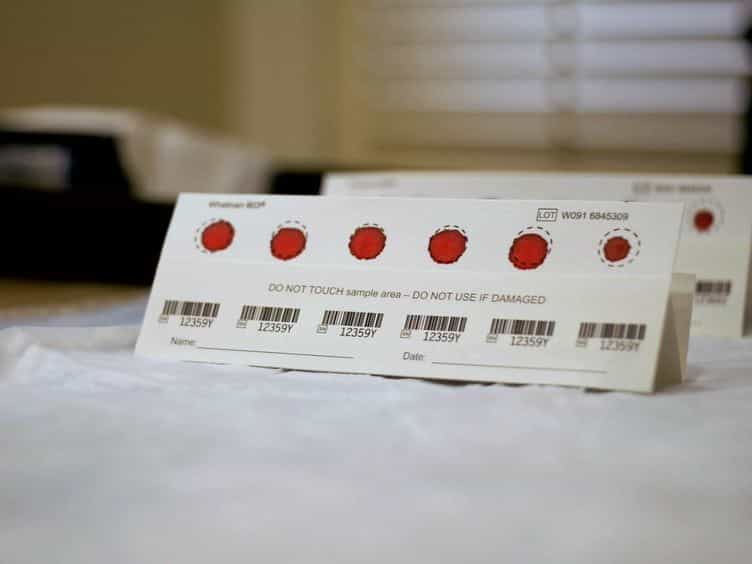

Dried Blood Spot Collection of Health Biomarkers to Maximize Participation in Population Studies
Published on: January 28, 2014
Biomarkers
Fuqiang Gao1, Joel Ramirez2,3, Melissa F Holmes1
1Dr. Sandra Black Centre for Brain Resilience and Recovery, Sunnybrook Research Institute, Toronto, ON, Canada.

Background:
Periventricular white matter hyperintensities (pWMH), commonly thought to be ischemic and demyelinating in origin, are prevalent in Alzheimer's disease (AD). However, occlusive collagenosis of deep medullary veins (DMVs), a venulopathy has been implicated in pWMH. Not only leakage, but also perivascular lymphatic system stasis may lead to chronic excessive extracellular fluid accumulation. In vivo, we investigated collocation of confluent pWMH with DMVs and radiological evidence of pWMH edema in AD, in conjunction with pathological correlation.
Method:
88 AD and 33 controls (age=76) with confluent pWMH on T2/FLAIR were included. DMVs were defined as linear streaks on T1/inverted-T2 radiating from the subependymal region of the lateral ventricle. Spatial relationships of confluent pWMH was measured by counting the number of DMVs in each confluent pWMH. Radiological signs of edema were determined by whether compact white matter tracts (including optic radiation, fronto-occipital fasciculus, thalamofrontal tract and u-fibers) were spared within or around pWMH. Also pWMH changes over time were analyzed, assuming WMH would exhibit dynamic changes if they are edema related. Perivascular spaces and lacunes were also quantified. Thirteen imaging-pathological correlations were available to validate imaging findings.
Result:
DMVs were identified in 283 discrete confluent pWMH across all participants. Significant associations were demonstrated between pWMH volume and total number of DMVs depicted within pWMH. Co-location of pWMH with DMVs appeared to be unique by comparing them to regions without pWM. Compact fiber tracts were spared by confluent pWMH in 95% overall, and 24% of pWMH volumes decreased over time. Pathologically, using trichrome staining, venous collagenosis (wall thickening, stenosis or occlusion) of large (p = 0.012) and smaller venules (p = 0.036) were significant predictors of pWMH. Demyelination using luxol blue contributed but did not survive multiple regression.
Conclusion:
Confluent pWMH clearly mapped to visualizable DMVs, suggesting venous insufficiency due to collagenosis. Compact fiber tract sparing and reversible progression of pWMH provided in vivo evidence of chronic edema. Our findings support the notion that venous insufficiency of DMVs is the main substrate of pWMH, reflecting vasogenic edema induced from increased venous pressure and extracellular fluid accumulation from reduced interstitial fluid circulation along the glymphatic perivenous spaces.
Insights
Periventricular white matter hyperintensities (pWMH) in Alzheimer's disease (AD) are linked to deep medullary vein (DMV) issues. This study shows DMV venulopathy causes pWMH, indicating chronic edema from venous insufficiency.
Area of Science:
- Neurology
- Neuroimaging
- Pathology
Background:
- Periventricular white matter hyperintensities (pWMH) are common in Alzheimer's disease (AD), often attributed to ischemia or demyelination.
- Deep medullary veins (DMVs) venulopathy, specifically occlusive collagenosis, is increasingly implicated in pWMH development.
- Venous stasis and lymphatic system dysfunction may contribute to excessive extracellular fluid accumulation, leading to chronic edema.
Purpose of the Study:
- To investigate the in vivo association between confluent pWMH and DMVs in AD patients.
- To identify radiological and pathological evidence supporting DMV venulopathy as a cause of pWMH and associated edema.
- To correlate imaging findings with pathological data for validation.
Main Methods:
- Included 88 AD patients and 33 controls with confluent pWMH on T2/FLAIR MRI.
- Defined DMVs and measured their spatial relationship with pWMH.
- Assessed radiological signs of edema, including sparing of compact white matter tracts and dynamic pWMH changes over time.
- Quantified perivascular spaces and lacunes, with 13 imaging-pathological correlations for validation.
Main Results:
- Confluent pWMH significantly co-located with identified DMVs.
- A strong association was found between pWMH volume and the number of DMVs.
- Pathological analysis revealed venous collagenosis in large and small venules as significant predictors of pWMH.
Conclusions:
- Confluent pWMH in AD patients are strongly associated with visualizable DMVs, suggesting venous insufficiency due to collagenosis.
- In vivo evidence supports chronic edema, indicated by compact fiber tract sparing and reversible pWMH progression.
- Findings suggest DMV venous insufficiency is a primary cause of pWMH, leading to vasogenic edema and extracellular fluid accumulation.


Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...