Related Experiment Video
Updated: Jan 7, 2026


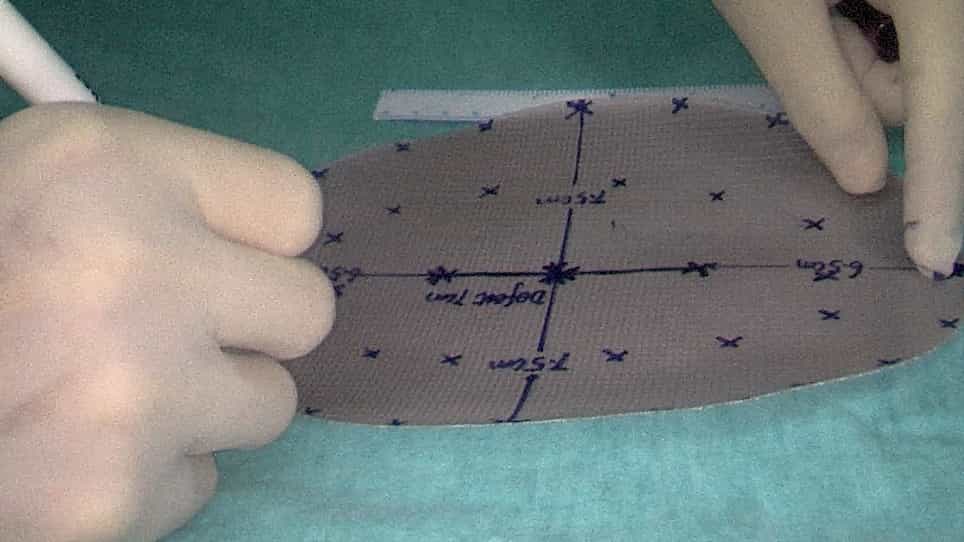
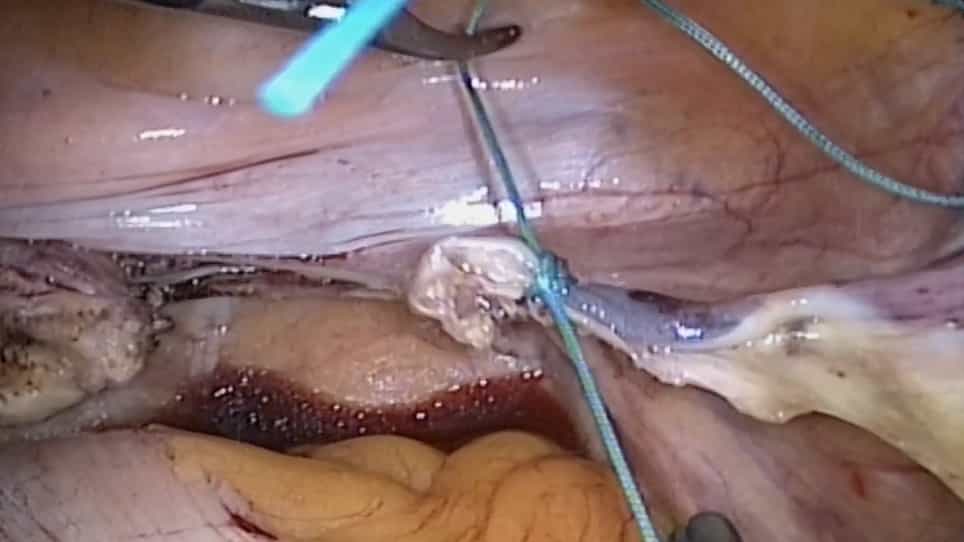
Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
Retromuscular prophylactic mesh reinforcement after midline laparotomy: a systematic review and meta-analysis
Melissa Lagger1,2, Sguinzi Raffaella3, Buhler Leo3,4
1Department of Surgery, Cantonal Hospital of Fribourg, Chemin Des Pensionnats 2/6, 1752, Villars-Sur-Glâne, Fribourg, Switzerland. melissa.lagger@h-fr.ch.

Purpose:
Incisional hernias (IH) are a frequent complication after laparotomy, contributing to patient morbidity and increased healthcare costs. While guidelines recommend prophylactic mesh reinforcement (PMR) in high-risk elective surgeries, there are no specific recommendations for contaminated/emergency settings. The retromuscular plane is considered optimal for mesh placement due to its favourable outcomes. This systematic review and meta-analysis aimed to evaluate the effectiveness and safety of retromuscular PMR in reducing IH rates following elective and contaminated/emergency midline laparotomies.
Methods:
Following the PICO framework, we included studies assessing patients undergoing elective or contaminated/emergency midline laparotomies. The intervention was retromuscular PMR compared to primary suture closure (PSC). The primary outcome was IH incidence, with surgical site infection (SSI), seroma, and hematoma as secondary outcomes. A systematic literature search was conducted in Medline, Embase, Web of Science and Cochrane Library, the last search was completed on March 7th, 2025. Risk of bias was assessed using the RoB 2 tool. A random-effects meta-analysis was performed, with subgroup analyses by mesh type and surgical setting.
Results:
Eight randomized controlled trials totalizing 1167 patients were included. PMR significantly reduced the risk of incisional hernia at the longest available follow-up compared to primary suture closure (OR 0.37, 95% CI 0.17-0.80), but heterogeneity was high (I2 = 74%). Subgroup analysis showed benefit with synthetic mesh (OR 0.18, 95% CI 0.06-0.52) but not with biologic mesh. No significant differences were observed in surgical site infection, while non-significant trends toward increased seroma (OR 1.97) and hematoma (OR 3.05) were noted. Evidence in contaminated/emergency settings was limited and exploratory.
Conclusion:
Retromuscular prophylactic mesh reinforcement reduces incisional hernia incidence in elective laparotomy, particularly with synthetic mesh, without increasing major infectious complications. However, substantial heterogeneity across studies limits the certainty of effect estimates, and evidence in contaminated or emergency surgery remains insufficient.
Systematic Review Registration:
PROSPERO CRD42025632413.
Insights
Retromuscular prophylactic mesh reinforcement (PMR) significantly lowers incisional hernia rates after elective laparotomy, especially with synthetic mesh. More research is needed for contaminated or emergency settings.
Area of Science:
- Abdominal Surgery
- Surgical Innovation
- Hernia Repair
Background:
- Incisional hernias (IH) are common after laparotomy, causing morbidity and costs.
- Guidelines suggest prophylactic mesh reinforcement (PMR) for high-risk elective cases.
- Optimal mesh placement is in the retromuscular plane for better outcomes.
Purpose of the Study:
- To assess retromuscular PMR's effectiveness and safety in reducing IH after midline laparotomies.
- To compare PMR against primary suture closure (PSC) in elective and contaminated/emergency settings.
Main Methods:
- Systematic review and meta-analysis of 8 RCTs (1167 patients).
- Included elective or contaminated/emergency midline laparotomies comparing retromuscular PMR vs. PSC.
- Primary outcome: IH incidence. Secondary outcomes: surgical site infection (SSI), seroma, hematoma.
Main Results:
- PMR significantly reduced IH risk versus PSC (OR 0.37), with high heterogeneity (I²=74%).
- Synthetic mesh showed a significant benefit (OR 0.18), but biologic mesh did not.
- No significant SSI difference; trends toward increased seroma and hematoma.
Conclusions:
- Retromuscular PMR effectively reduces IH in elective laparotomy, particularly with synthetic mesh.
- No increase in major infectious complications was observed.
- Evidence for contaminated/emergency settings is limited; substantial heterogeneity impacts certainty.