Related Experiment Video
Updated: Jan 7, 2026

Author Spotlight: Minimally Invasive Relief for Occipital Neuralgia at the Nuchal Line
Published on: September 13, 2024
Orocervical Actinomycosis in a Patient With Neck Swelling and Occipital Headache: A Case Report
Mehran Frouzanian1, Ahmad Alikhani2, Amirsaleh Abdollahi1
1Department of Infectious Diseases, School of Medicine, Mazandaran University of Medical Sciences, Sari, Iran, mazums.ac.ir.

Abstract:
Actinomycosis is a rare bacterial infection caused by Actinomyces species, most commonly affecting the cervicofacial region. Posterior skull base involvement is extremely uncommon. We report a case of actinomycosis in a 44-year-old male with a 10-year history of chronic hepatitis B on tenofovir therapy, who presented with a 3-month history of progressive right-sided neck swelling, pain, occipital headaches, and a 10 kg weight loss. The patient initially experienced a sore throat and neck discomfort, partially relieved by medication, but gradually developed a foreign body sensation in the retropharynx and painful swelling in the lateral neck and behind the right ear, accompanied by fever and chills. Physical examination revealed swelling, erythema, warmth over the right lateral neck, and neck stiffness. MRI showed an ill-defined infiltrative lesion at the posterior skull base, involving the right occipital bone and upper cervical vertebrae, extending into adjacent soft tissues. Biopsy of the lesion demonstrated filamentous organisms with sulfur granules amid a mixed inflammatory response, confirming actinomycosis. The patient was treated with intravenous ceftriaxone followed by oral amoxicillin, along with surgical drainage from the right posterior cervical region. At the 11 week follow-up, he showed significant clinical improvement, with continued long-term antibiotics due to bone involvement. This case highlights the diagnostic challenges posed by atypical presentations of actinomycosis, particularly in patients with predisposing conditions such as chronic infections. Unlike typical cervicofacial actinomycosis, this patient lacked classical features such as discharging sinuses or lymphadenopathy. Recognition of sulfur granules in biopsy specimens was pivotal for diagnosis. Early diagnosis, prolonged high-dose antibiotic therapy, and surgical intervention when needed are crucial to achieving favorable outcomes. Clinicians should maintain a high index of suspicion for actinomycosis in patients presenting with unexplained neck masses and skull base lesions.

Related Concept Videos
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:26
Tonsillitis II: Management
 01:19
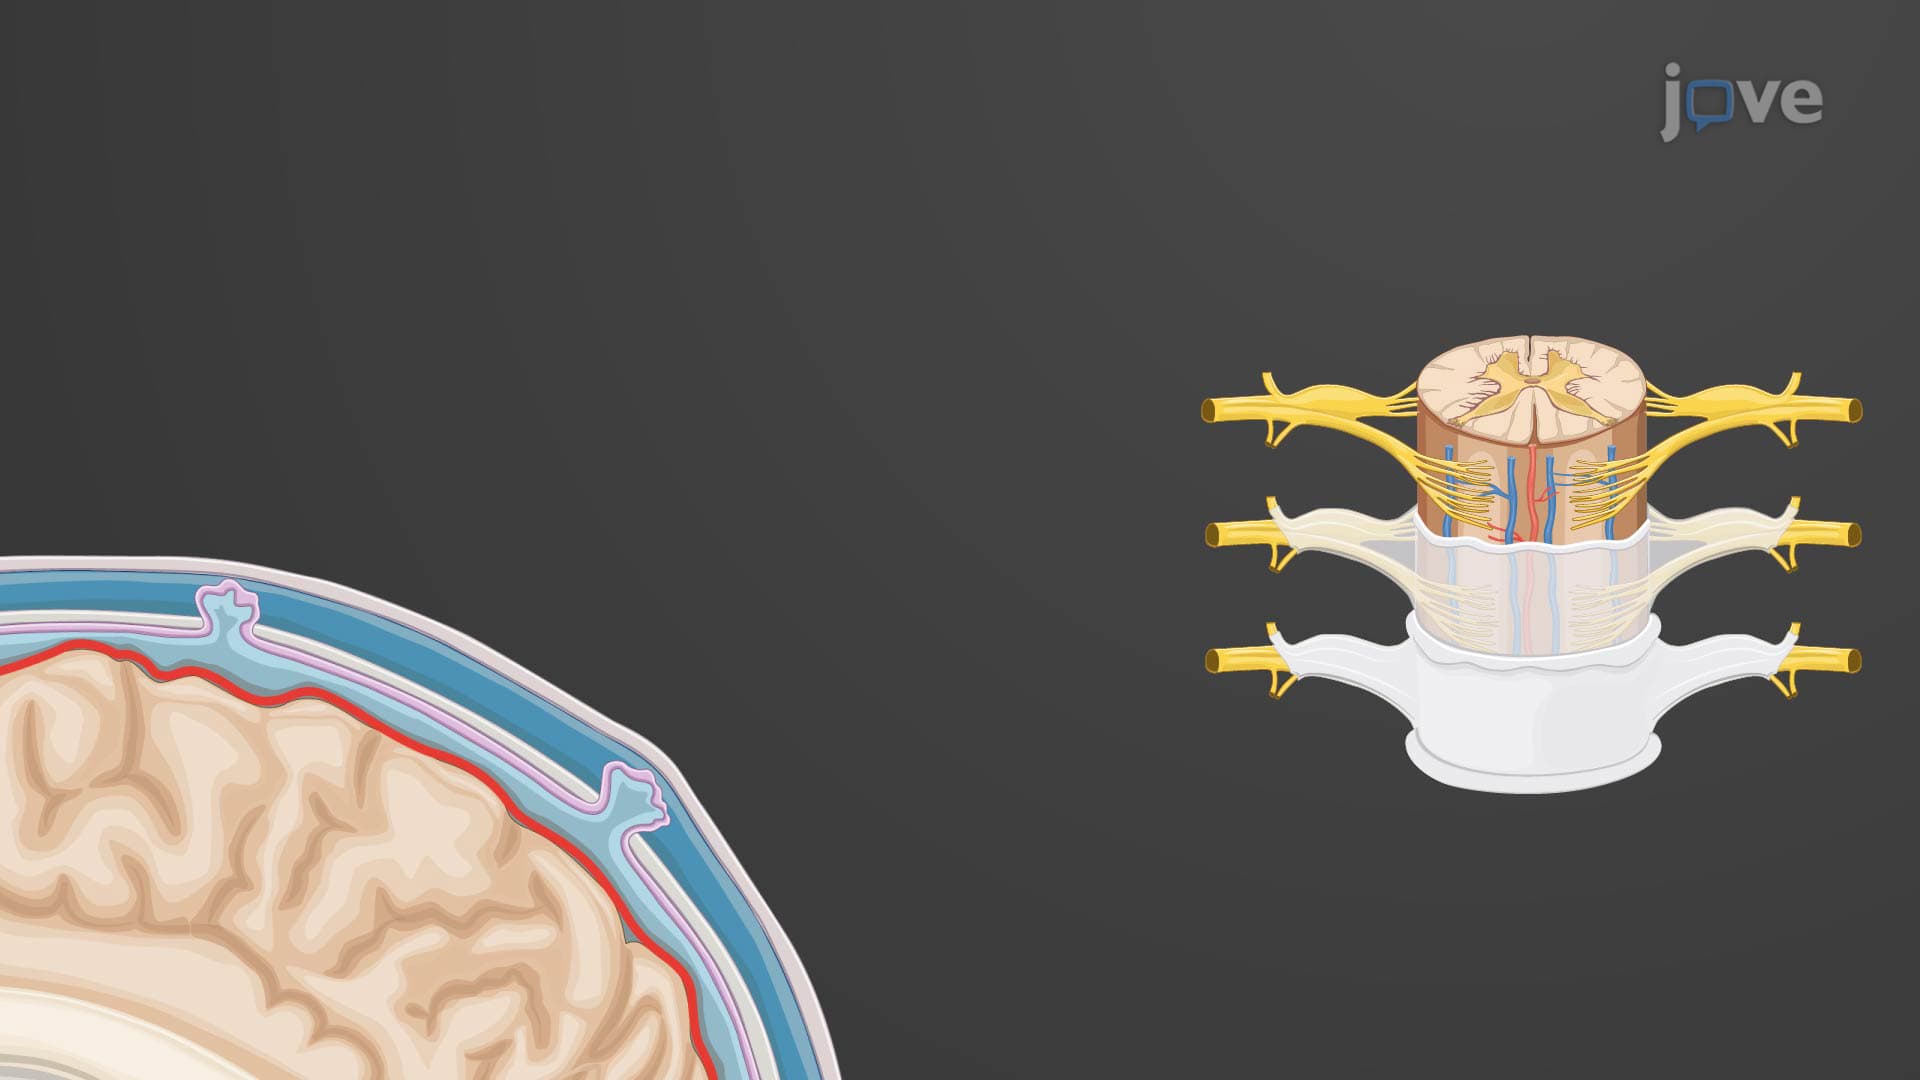
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.