Related Experiment Video
Updated: Jun 25, 2026
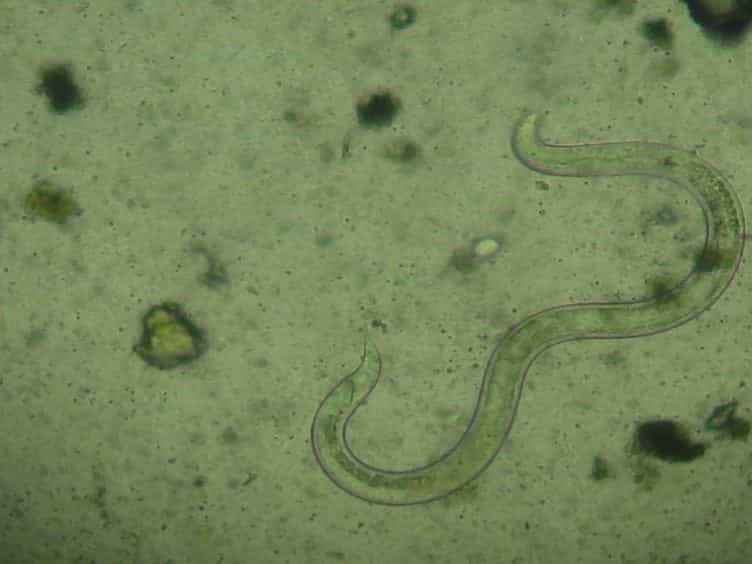

Determining Soil-transmitted Helminth Infection Status and Physical Fitness of School-aged Children
Published on: August 22, 2012
Real-World Use of GLP-1 Receptor Agonist Liraglutide in Adolescents with Obesity: A First Longitudinal Single-Center
Cees Noordam1, Urs Eiholzer1, Claudia Katschnig1
1Center for Paediatric Endocrinology Zurich (PEZZ), Moehrlistrasse 69, 8006 Zurich, Switzerland.

Abstract:
Background: Adolescent obesity remains a challenge with limited treatment options. GLP-1 receptor agonists such as liraglutide (Saxenda®) have shown efficacy in trials, but real-world data in youth are scarce. Methods: This retrospective longitudinal, non-interventional study analyzed 22 adolescents treated with liraglutide in a Swiss pediatric endocrinology center. All received non-structured nutritional/lifestyle counseling with three-monthly follow-up. BMI standard deviation scores (BMI-SDS) and adverse effects were recorded. Results: The mean age at initiation was 14.9 years (range 12.5-17.5); 15 patients had Southern European immigrant background. Mean treatment duration was 8.2 months (range 1-18). BMI-SDS decreased significantly from +2.63 (IQR +2.4/+2.8) to +2.40 (IQR +2.2/+2.6). Median intra-individual reduction was -0.20 (IQR -0.28/-0.10), p = 0.0003 with large effect size (rb = -0.77). Thirteen patients discontinued treatment, mainly due to insufficient weight loss or mild nausea. In the patients continuing therapy BMI-SDS decreased from +2.59 (IQR +2.4/+2.8) to +2.08 (IQR +1.9/+2.4). No serious adverse events occurred. Conclusions: Liraglutide showed a comparable efficacy to the pivotal clinical trial in reducing BMI-SDS in adolescents, while the side-effect profile was similarly mild and consistent with previously reported data. Discontinuation rates remained high, highlighting the need for thorough pre-treatment counseling on expected mild, transient symptoms and strategies to mitigate nausea. Future prospective studies are needed to assess long-term outcomes and identify patient characteristics associated with greater treatment success, to better individualize GLP-1-based therapy in adolescent obesity.
More Related Videos
 08:21
Non-invasive Assessments of Subjective and Objective Recovery Characteristics Following an Exhaustive Jump Protocol
Published on: June 8, 2017
 08:33
Targeting Alpha Synuclein Aggregates in Cutaneous Peripheral Nerve Fibers by Free-floating Immunofluorescence Assay
Published on: June 25, 2019
Related Concept Videos
 01:24
Obesity
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
 01:06
Oral Hypoglycemic Agents: Glinides
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...