Related Experiment Video
Updated: Jan 7, 2026

Tail Vein Transection Bleeding Model in Fully Anesthetized Hemophilia A Mice
Published on: September 30, 2021
Optimization of hemophilia B treatment via population PK modeling of rIX-FP, including a 3-week regimen
Naoki Terasaka1, William Mckeand2
1Medical Affairs Department, CSL Behring K.K., Kita-Aoyama Minato-ku, Tokyo, Japan.

Background:
Recombinant factor IX-albumin fusion protein (rIX-FP) enables extended-interval prophylaxis for hemophilia B. While higher trough levels with reduced dosing frequency have been shown vs. standard FIX products, age-related differences in pharmacokinetics (PK) may constrain extended intervals in children. We aimed to refine a population PK (popPK) model of rIX-FP to inform clinically practical dosing across pediatric, adolescent, and adult patients.
Methods:
Pooled FIX activity data from 113 previously treated patients (1-63 years) in five clinical studies were analyzed with a two-compartment popPK model. Covariates included body weight, age, weight-adjusted dose, and ethnicity (Japanese vs. non-Japanese). Model performance was evaluated by standard diagnostics and prediction-corrected visual predictive checks. Simulations estimated single-dose duration above 5% FIX activity and steady-state troughs for common prophylactic regimens stratified by age (<6, 6-<12, 12-<18, ≥12, ≥18 years).
Results:
Body weight significantly influenced clearance (CL) and volumes; weight-normalized CL was faster in children, especially <6 years. No meaningful ethnic effect was detected; PK parameters and simulated profiles were comparable between Japanese and non-Japanese patients. Simulations showed that in patients ≥12 years, median steady-state troughs were maintained around ∼5% with 25-50 IU/kg weekly, 50 IU/kg every 10 days, 75 IU/kg every 14 days, and 100 IU/kg every 21 days-supporting a 3-week option in well-controlled patients. In contrast, children <6 years generally required weekly dosing (≥40-50 IU/kg) to achieve ∼5% troughs; extending intervals substantially reduced the proportion meeting target levels.
Conclusion:
rIX-FP supports individualized prophylaxis with extended intervals up to 3 weeks in patients ≥12 years while younger children typically require more frequent dosing due to higher weight-normalized clearance. These PK-based insights can guide shared decision-making to balance protection, treatment burden, and patient preference across pediatric and adolescent age groups.


Related Concept Videos
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:12
Analysis of Population Pharmacokinetic Data
 01:09
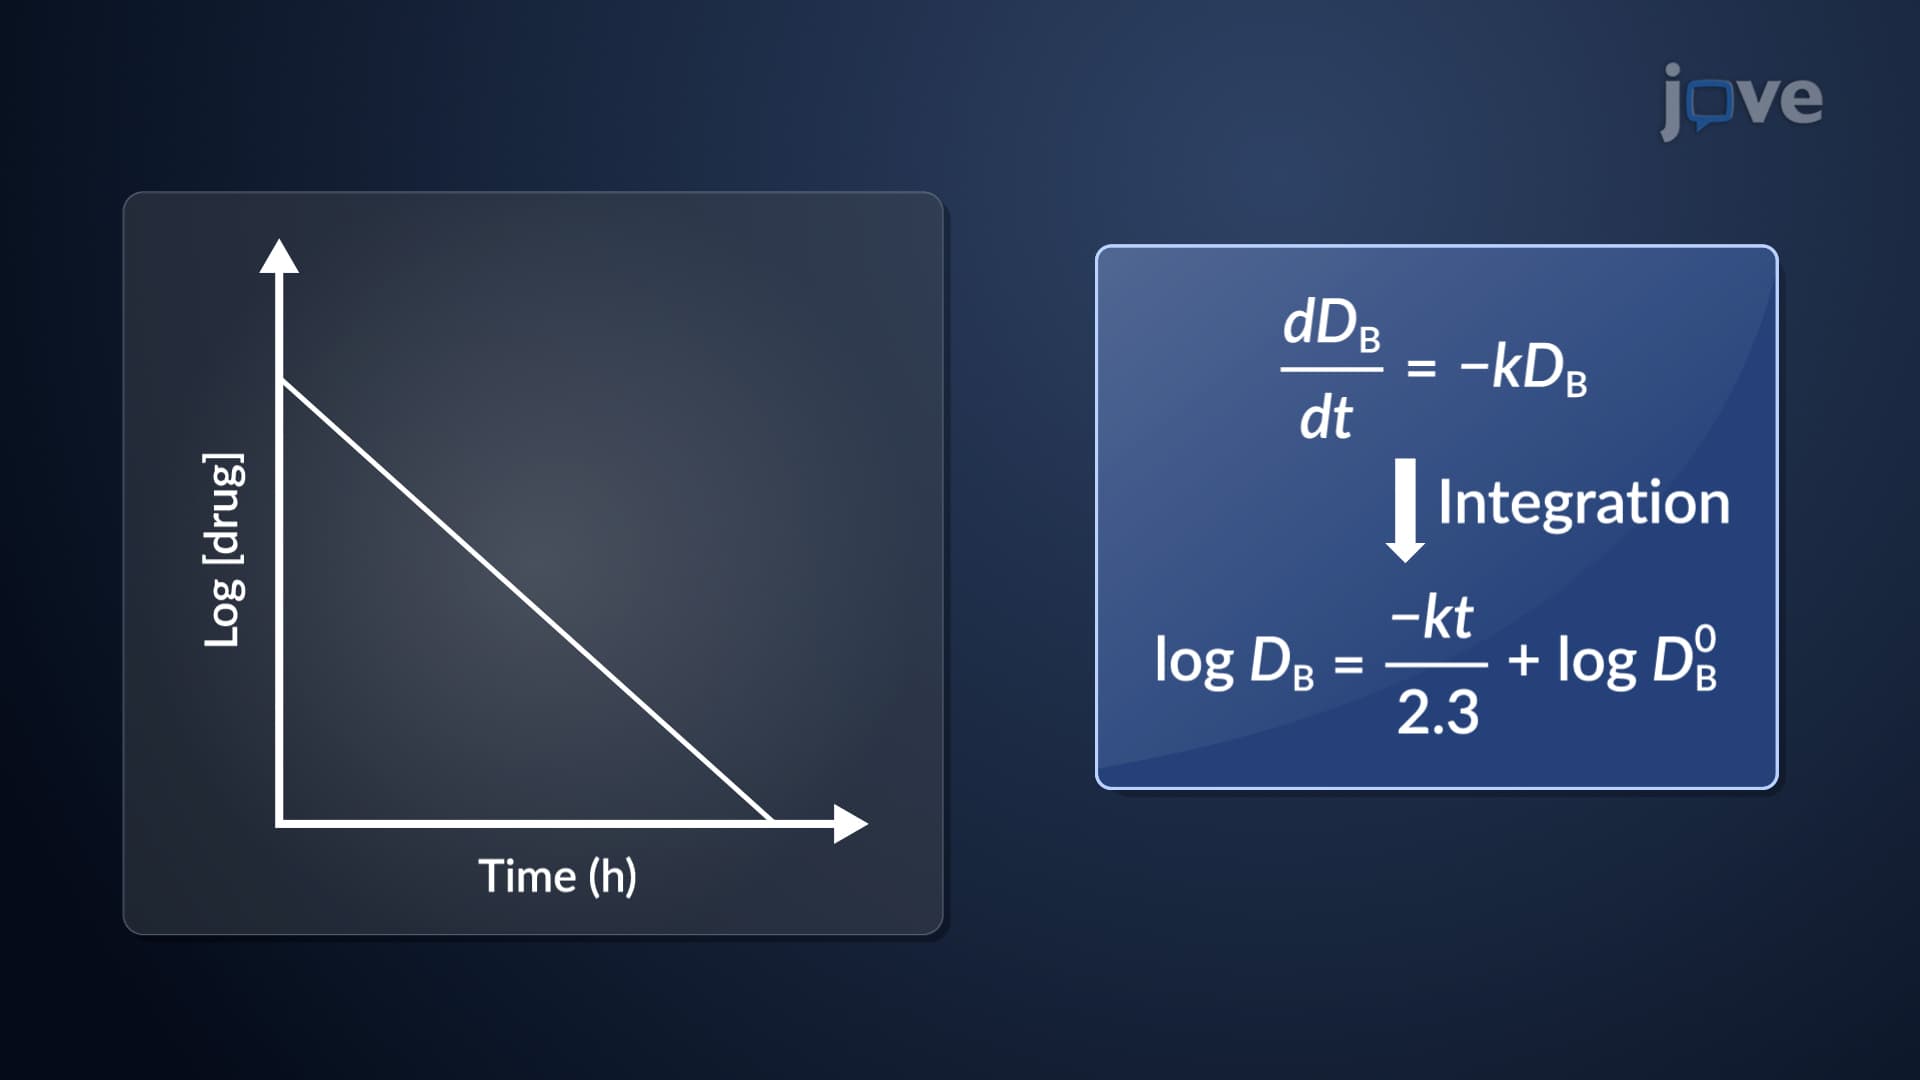
One-Compartment Open Model for IV Bolus Administration: Estimation of Elimination Rate Constant, Half-Life and Volume of Distribution
 01:29
Venous Thrombosis III: Interprofessional Care
 01:06
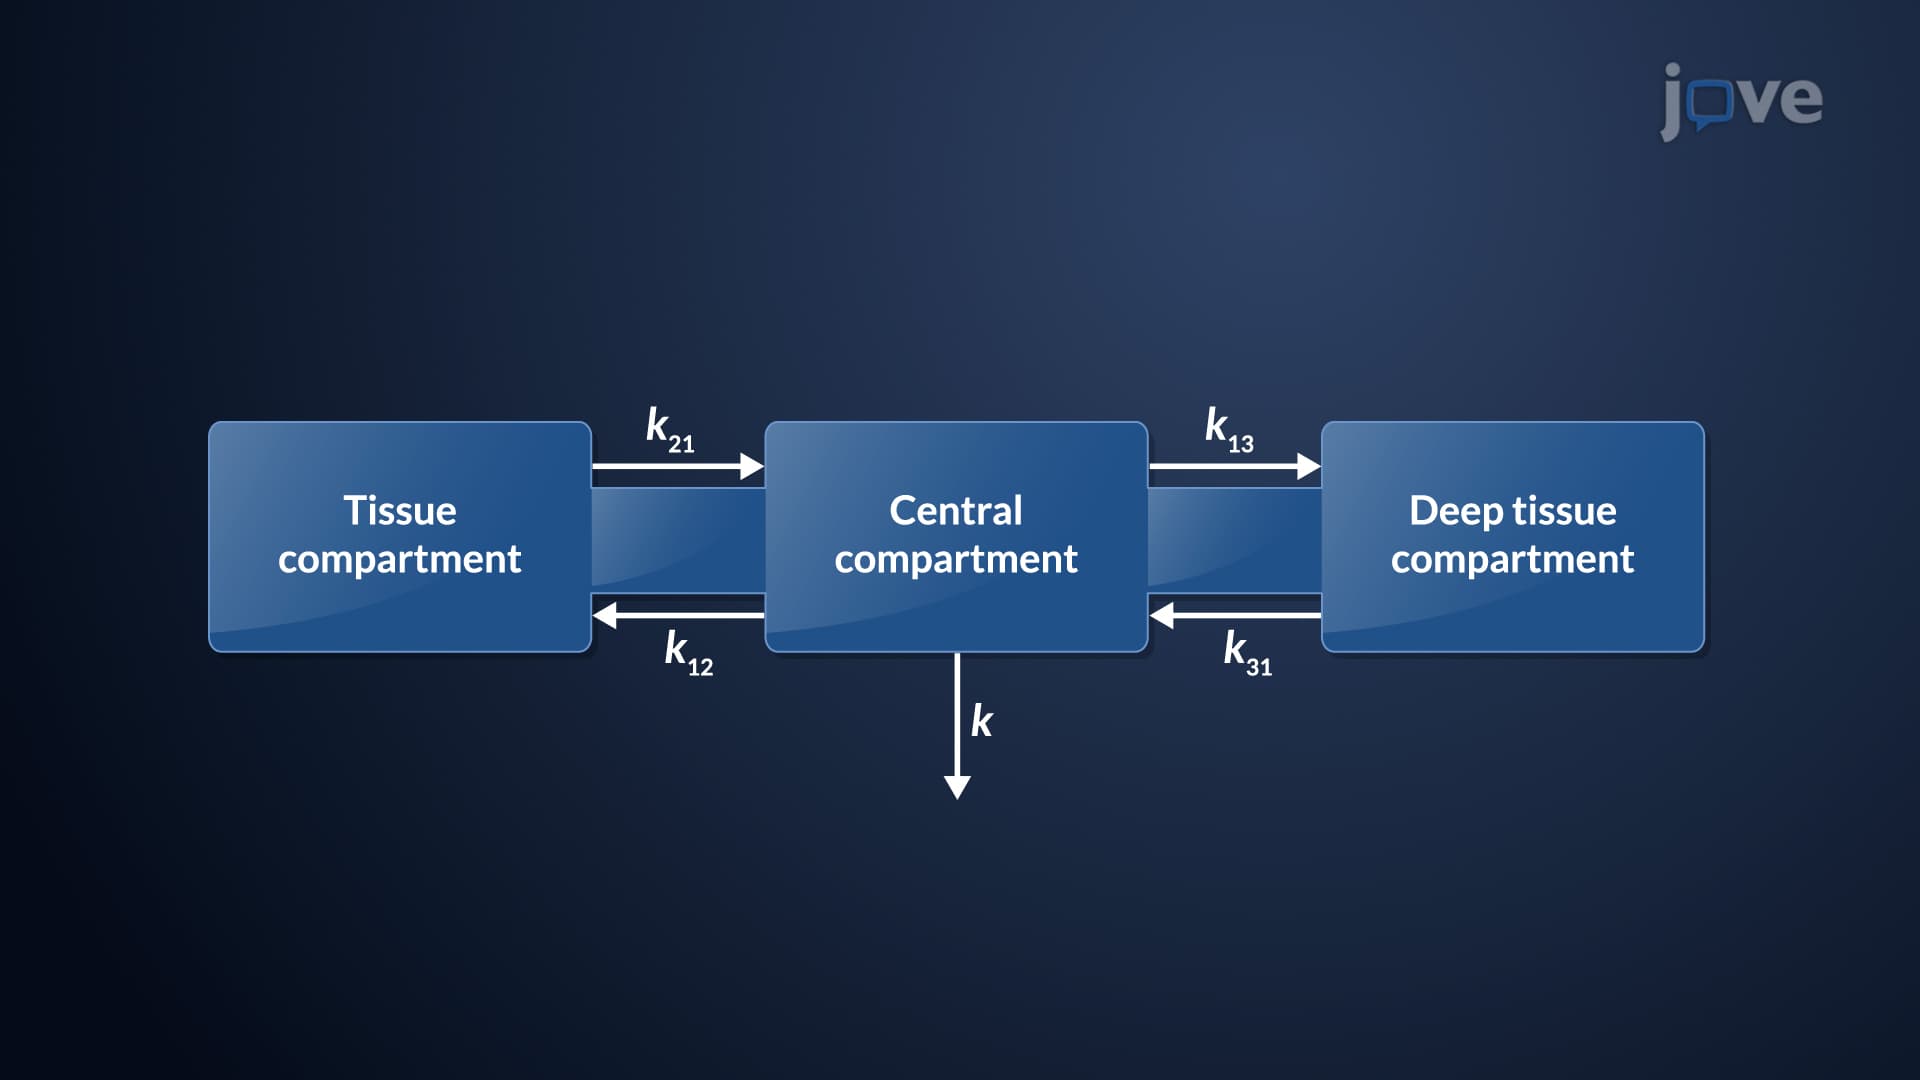
Three-Compartment Open Model
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections