Related Experiment Video
Updated: Jan 7, 2026
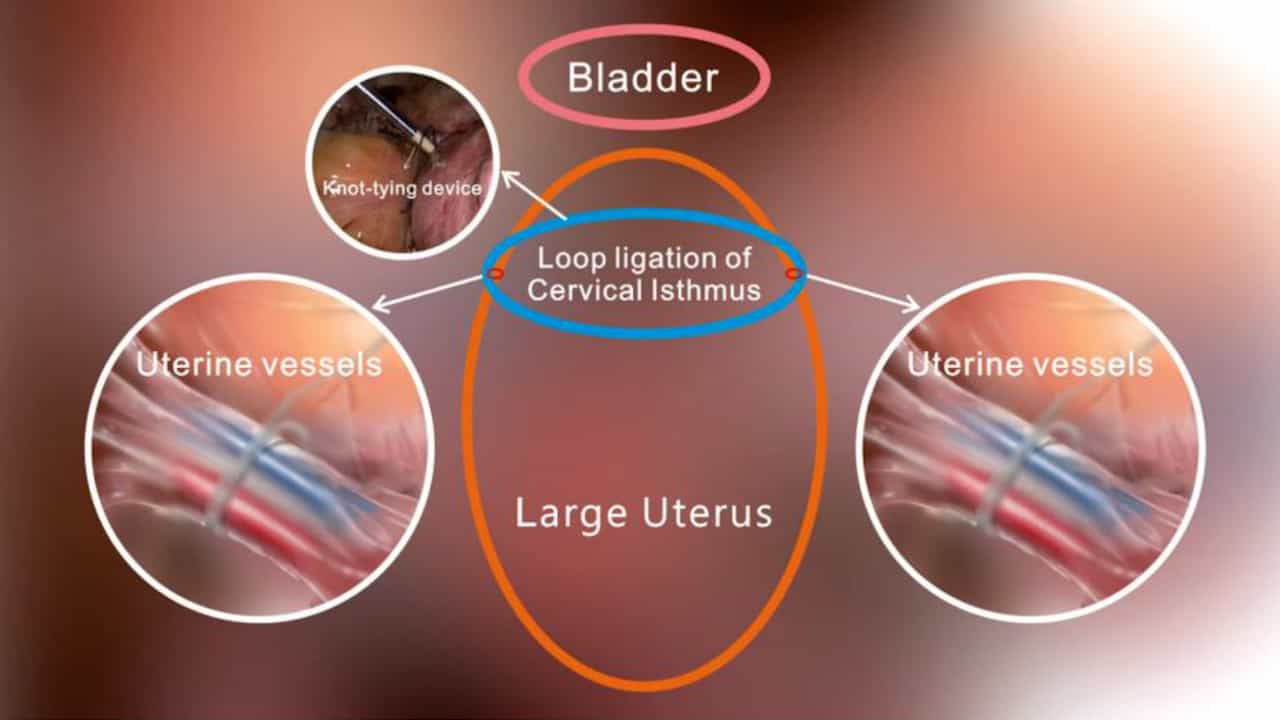
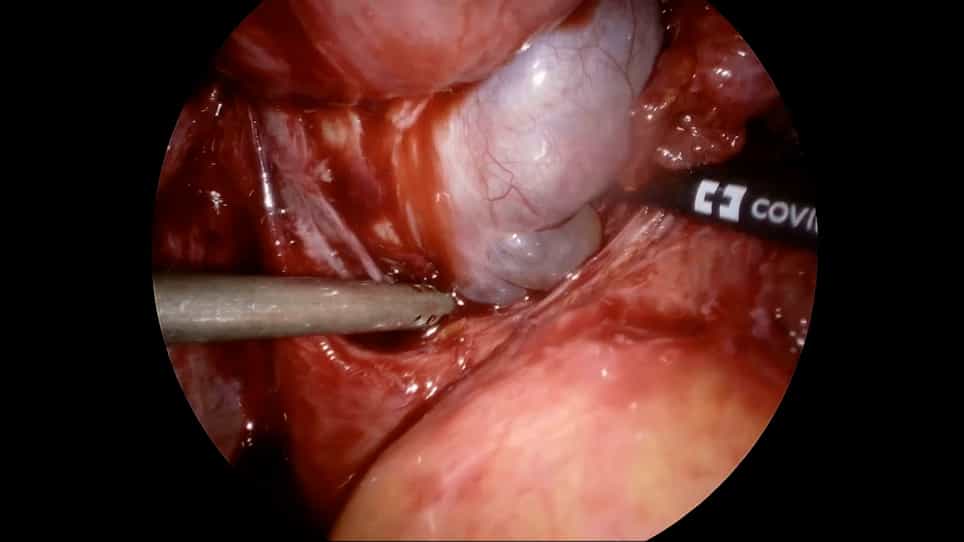
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Surgical management of complex cesarean delivery
Karin A Fox1, Albaro J Nieto-Calvache2, Rozi A Aryananda3
1Department of Obstetrics and Gynecology, University of Texas Medical Branch at Galveston, Galveston, TX.

Cesarean delivery is the most commonly performed surgery worldwide. Most obstetricians and gynecologists have become facile in performing cesarean delivery. However, the sequelae of multiple previous cesarean deliveries, such as postoperative uterine scar remodeling, and uterine dehiscence or rupture increase the complexity of cesarean delivery substantially. Adhesions, uterine dehiscence, uterine rupture, hysterotomy extensions, fibroids, and bleeding are common causes of increased surgical complexity, which varies depending on the degree of abnormal anatomy encountered and clinical acuity. Adhesions alter the texture, elasticity, and tensile strength of tissues. Adhesions distort anatomic planes and relationships and require careful dissection to avoid injuring other organs, such as the bladder or bowel, and to ensure hemostasis. Fibroids not only distort anatomic relationships but also may obscure the operative field, obstruct myometrial closure, or require removal for successful fetal delivery. Uterine dehiscence and rupture distort the bladder reflection, lower the uterine segment, and lead to fetal and maternal compromise, bleeding, and risk of hysterotomy extensions. Extensions commonly occur laterally, affecting uterine artery branches, or deeply toward the cervix and vagina. Rare cases of anatomic distortion include uterine sacculation secondary to an incarcerated retroverted uterus, whereby what appears to be the uterine fundus is actually the stretched lower uterine segment and bladder. Finally, cesarean delivery during cardiopulmonary resuscitation is arguably the most technically and psychologically challenging surgical scenario, with an estimated occurrence of 1 in 9000 deliveries in 2017 according to United States National Inpatient Sample estimates. Complex cesarean delivery requires technical expertise and advanced surgical skills. Recognition of normal anatomy and pathologic anatomic changes, continued surgical education, and a strategic approach to complex obstetrical surgery are key. This review aimed to illustrate the surgical approaches for selected complex scenarios using descriptions, images, and videos to help frontline surgeons who will face increasingly challenging cases over time.
Cesarean delivery is the most commonly performed surgery worldwide. Most obstetricians and gynecologists have become facile in performing cesarean delivery. However, the sequelae of multiple previous cesarean deliveries, such as postoperative uterine scar remodeling, and uterine dehiscence or rupture increase the complexity of cesarean delivery substantially. Adhesions, uterine dehiscence, uterine rupture, hysterotomy extensions, fibroids, and bleeding are common causes of increased surgical complexity, which varies depending on the degree of abnormal anatomy encountered and clinical acuity. Adhesions alter the texture, elasticity, and tensile strength of tissues. Adhesions distort anatomic planes and relationships and require careful dissection to avoid injuring other organs, such as the bladder or bowel, and to ensure hemostasis. Fibroids not only distort anatomic relationships but also may obscure the operative field, obstruct myometrial closure, or require removal for successful fetal delivery. Uterine dehiscence and rupture distort the bladder reflection, lower the uterine segment, and lead to fetal and maternal compromise, bleeding, and risk of hysterotomy extensions. Extensions commonly occur laterally, affecting uterine artery branches, or deeply toward the cervix and vagina. Rare cases of anatomic distortion include uterine sacculation secondary to an incarcerated retroverted uterus, whereby what appears to be the uterine fundus is actually the stretched lower uterine segment and bladder. Finally, cesarean delivery during cardiopulmonary resuscitation is arguably the most technically and psychologically challenging surgical scenario, with an estimated occurrence of 1 in 9000 deliveries in 2017 according to United States National Inpatient Sample estimates. Complex cesarean delivery requires technical expertise and advanced surgical skills. Recognition of normal anatomy and pathologic anatomic changes, continued surgical education, and a strategic approach to complex obstetrical surgery are key. This review aimed to illustrate the surgical approaches for selected complex scenarios using descriptions, images, and videos to help frontline surgeons who will face increasingly challenging cases over time.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:22
Aneurysm IV: Nursing Management
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...