Related Experiment Video
Updated: Apr 30, 2026


Ex Vivo Perfusion of the Rodent Placenta
Published on: May 30, 2019
Cesarean delivery for placenta previa
Ottavio Cassardo1, Michele Orsi1, Manuela Wally Ossola1
1Division of Obstetrics, Fondazione IRCCS Ca' Granda Ospedale Maggiore Policlinico, Milan, Italy.

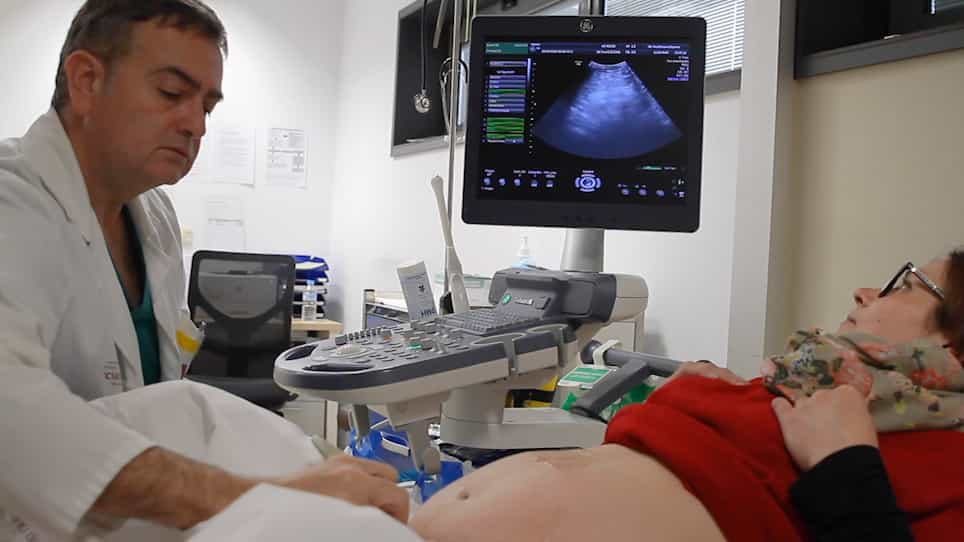
Placenta previa is an absolute indication for cesarean delivery and is associated with serious risks for maternal and neonatal health. At delivery, its prevalence is 0.5% to 1%, after being observed in up to 10% at the mid-trimester scan. Risk is highest with prior cesarean delivery and recurrence after a prior placenta previa is 4% to 8%. Twin gestations have a higher absolute prevalence (3.9 vs 2.8 per 1000 live births), and assisted reproduction carries a 6-fold risk compared to spontaneous conception. Maternal morbidity is dominated by hemorrhage: antepartum bleeding occurs in 40% to 60% and postpartum hemorrhage in 20% to 35%. Preterm birth drives neonatal risk: more than 40% of patients with placenta previa deliver before 37 weeks, and placenta previa accounts for 6% to 7% of indications for delivery before 35 weeks. Transvaginal ultrasound is the diagnostic gold standard and should be used to confirm transabdominal findings, measure the internal os distance, and exclude associated conditions (placenta accreta spectrum and vasa previa). Antenatal management and timing of delivery are based on the delicate equilibrium between the risk of maternal hemorrhage and the consequences of iatrogenic prematurity. For asymptomatic placenta previa, planned cesarean is generally recommended at 360 to 376 weeks (often earlier within this window for anterior previa). For low-lying placenta, internal-os distance guides delivery planning and current evidence supports a trial of labor in women with a distance of 11 to 20 mm. Operative care should be standardized within a multidisciplinary "placenta team" (obstetrics, anesthesia, interventional radiology, and urology as needed), with preparedness for major hemorrhage. Given the psychological burden-especially in complicated cases-structured debriefing and postpartum support are recommended.
Placenta previa is an absolute indication for cesarean delivery and is associated with serious risks for maternal and neonatal health. At delivery, its prevalence is 0.5% to 1%, after being observed in up to 10% at the mid-trimester scan. Risk is highest with prior cesarean delivery and recurrence after a prior placenta previa is 4% to 8%. Twin gestations have a higher absolute prevalence (3.9 vs 2.8 per 1000 live births), and assisted reproduction carries a 6-fold risk compared to spontaneous conception. Maternal morbidity is dominated by hemorrhage: antepartum bleeding occurs in 40% to 60% and postpartum hemorrhage in 20% to 35%. Preterm birth drives neonatal risk: more than 40% of patients with placenta previa deliver before 37 weeks, and placenta previa accounts for 6% to 7% of indications for delivery before 35 weeks. Transvaginal ultrasound is the diagnostic gold standard and should be used to confirm transabdominal findings, measure the internal os distance, and exclude associated conditions (placenta accreta spectrum and vasa previa). Antenatal management and timing of delivery are based on the delicate equilibrium between the risk of maternal hemorrhage and the consequences of iatrogenic prematurity. For asymptomatic placenta previa, planned cesarean is generally recommended at 360 to 376 weeks (often earlier within this window for anterior previa). For low-lying placenta, internal-os distance guides delivery planning and current evidence supports a trial of labor in women with a distance of 11 to 20 mm. Operative care should be standardized within a multidisciplinary "placenta team" (obstetrics, anesthesia, interventional radiology, and urology as needed), with preparedness for major hemorrhage. Given the psychological burden-especially in complicated cases-structured debriefing and postpartum support are recommended.

Related Concept Videos
 01:07
Teratogenicity
 01:19
Mitral Valve Prolapse III: Nursing Management