Related Experiment Video
Updated: May 5, 2026
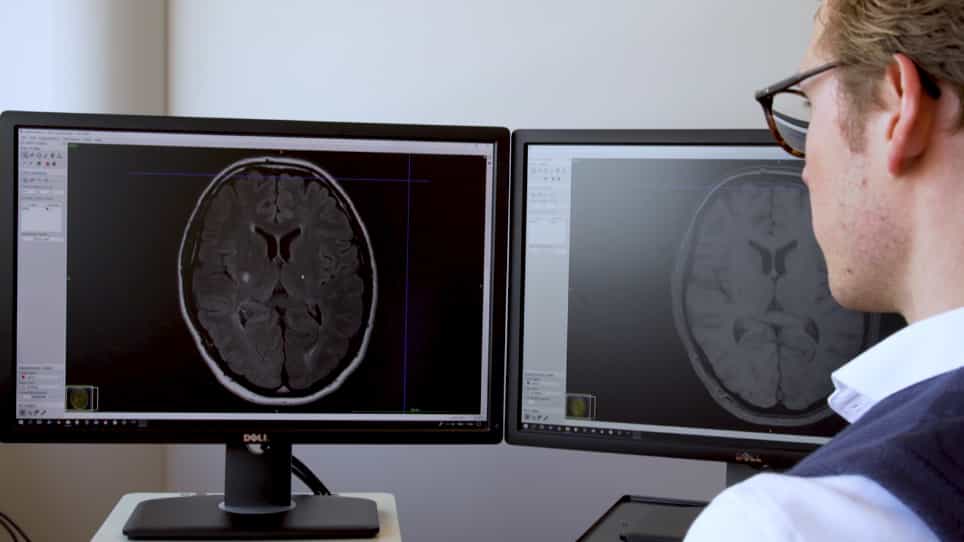

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Network-Level Brain Dysfunction Beyond the Lesion: A Rare Case of Monakow Syndrome Presenting With Fluctuating
Godai Yawata1, Asato Tsuji1, Mariko Takata1
1Department of Neurology, Kitaharima Medical Center, Ono, JPN.

Abstract:
Anterior choroidal artery (AChA) infarction typically manifests as the classical triad of contralateral hemiparesis, hemisensory loss, and homonymous hemianopia (Monakow syndrome). We report a rare case of right AChA infarction presenting with fluctuating consciousness and left hemispatial neglect, accompanied by widespread functional suppression of the right cerebral hemisphere. A 65-year-old right-handed man initially exhibited mild dysarthria and left-sided sensory impairment, with no acute lesions on diffusion-weighted MRI. He subsequently developed impaired consciousness and hemispatial neglect. Follow-up MRI demonstrated acute infarcts in the posterior limb of the internal capsule (PLIC) and lateral geniculate nucleus (LGN). Arterial spin labeling (ASL) and N-isopropyl-p-[123I]iodoamphetamine single-photon emission computed tomography (IMP-SPECT) revealed extensive right-hemispheric hypoperfusion, disproportionate to the structural lesion. Recent evidence indicates that the PLIC and LGN function as major network hubs rather than simple relay pathways. Local injury to these hubs may disrupt global network efficiency, producing functional diaschisis. This case highlights the need to consider network-level dysfunction in AChA infarction.

Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:26
Transient Ischemic Attack l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:22
Dementia l: Introduction
 01:29
Hepatic Encephalopathy