
Automated brain atrophy quantification from clinical MRI predicts early neurological deterioration in anterior
Weiwei Gao1,2, Shouyue Jin1,2, Zhimin Xiao1,2
1Department of Neurology, Zhongshan Hospital of Xiamen University, School of Medicine, Xiamen University, Xiamen, China.

Background:
Early neurological deterioration (END) occurs in 43%-60% of patients with anterior choroidal artery (AChA) territory infarction. While brain atrophy serves as an imaging biomarker of diminished brain reserve capacity and may influence stroke outcomes, its predictive value for END in AChA infarction remains unclear.
Methods:
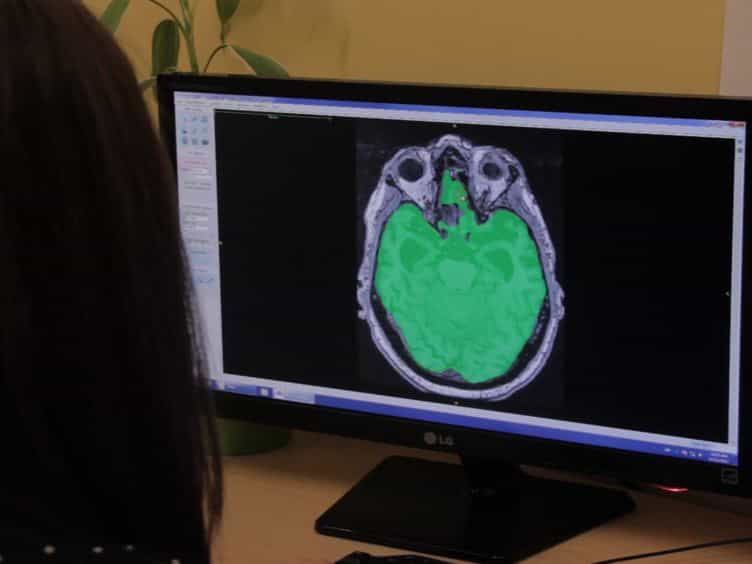
This dual-center retrospective cohort study consecutively enrolled patients with acute AChA territory infarction admitted to two Chinese stroke centers between September 2018 and September 2024. Clinical T1-weighted images were reconstructed into standardized high-resolution images using the SynthSR deep learning algorithm, followed by fully automated brain tissue segmentation via AssemblyNet. We calculated gray matter fraction (GMF), white matter fraction (WMF), brain parenchymal fraction (BPF), and cerebrospinal fluid fraction (CSFF) to quantify brain atrophy severity. Multivariable logistic regression and restricted cubic spline (RCS) analyses were employed to assess associations between brain atrophy metrics and END.
Results:
Among 206 enrolled patients, 78 (37.86%) developed END. Patients with END demonstrated significantly greater brain atrophy: GMF (P < 0.001), WMF (P < 0.001), and BPF (P < 0.001) were all significantly reduced, while CSFF was correspondingly elevated (P < 0.001). In fully adjusted models, each 0.01-unit increase in WMF was associated with a 58% reduction in END risk (P < 0.001); each 0.01-unit increase in BPF corresponded to a 32% risk reduction (P = 0.002); and each 0.01-unit increase in CSFF was associated with a 52% increase in risk (P < 0.001). Quartile analysis confirmed dose-response relationships: the highest quartiles of WMF and BPF were associated with 91% and 74% reductions in END risk, respectively, while the highest CSFF quartile conferred a 6.2-fold increased risk. RCS analysis confirmed significant linear dose-response relationships between both BPF and CSFF with END (both P-non-linear > 0.05).
Conclusion:
Automated brain atrophy quantification based on routine clinical MRI can independently predict END risk in patients with AChA infarction, providing a feasible imaging biomarker for this high-risk stroke population and facilitating early risk stratification and treatment optimization.
More Related Videos

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies