Related Experiment Video
Updated: Jan 13, 2026

Surgical Correction for Pediatric Epiblepharon and Trichiasis
Published on: July 8, 2025
Paediatric frontoethmoidal mucoceles causing epiphora: SALDO update study (SUP) - paper VI
Nandini Bothra1, Mohammad Javed Ali1
1Govindram Seksaria Institute of Dacryology, L.V. Prasad Eye Institute, Hyderabad, India.

Insights
Paediatric frontoethmoidal mucoceles can cause epiphora and subtle signs, often first seen by ophthalmologists. Endoscopic endonasal marsupialization effectively resolves epiphora in most cases.
Area of Science:
- Ophthalmology
- Otorhinolaryngology
- Pediatric Surgery
Background:
- Frontoethmoidal mucoceles are rare in children.
- These mucoceles can present with subtle signs, including epiphora, and may be initially evaluated by ophthalmologists.
Purpose of the Study:
- To describe the clinical presentation, management, and outcomes of pediatric frontoethmoidal mucoceles causing epiphora.
- To highlight the importance of early identification and management of these rare conditions.
Main Methods:
- A retrospective, interventional study of six pediatric patients with paranasal sinus mucoceles presenting with epiphora.
- Data collected included demographics, ophthalmic evaluations, lacrimal irrigation, endoscopic assessment, and CT scans.
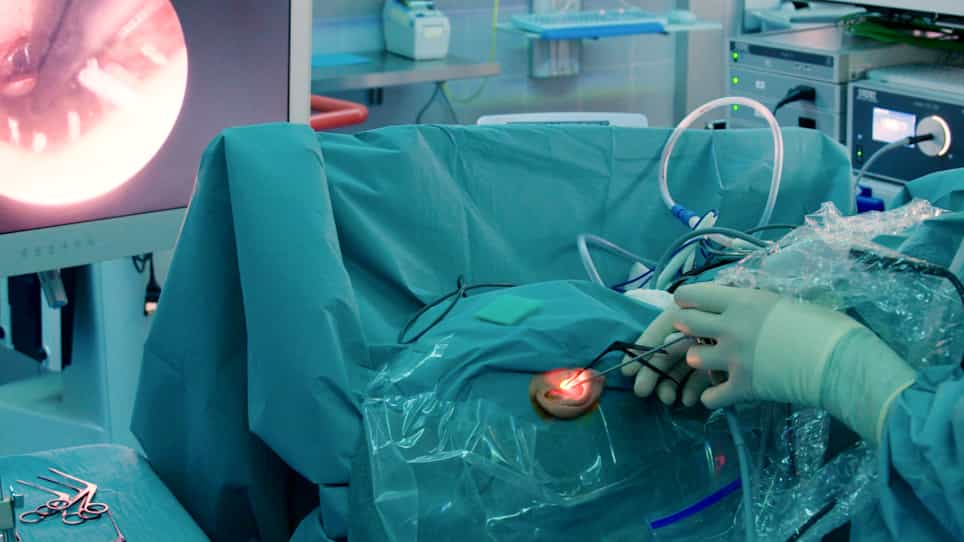
- All patients underwent endoscopic endonasal marsupialization.
Main Results:
- Six pediatric patients (mean age 12.83 years) with frontoethmoidal mucoceles causing epiphora were treated.
- Five patients experienced relief from epiphora and reduction in associated signs after marsupialization.
- One patient with traumatic secondary acquired nasolacrimal duct obstruction required additional dacryocystorhinostomy.
Conclusions:
- Pediatric sinus mucoceles are rare and can present subtly, often to ophthalmologists.
- Vigilance and prompt diagnosis are crucial for effective early management.
- Endoscopic endonasal marsupialization is an effective treatment for pediatric frontoethmoidal mucoceles causing epiphora.
Purpose:
To report the presentation, management, and outcomes of paediatric frontoethmoidal mucoceles causing epiphora.
Methods:
Retrospective, interventional study involving six paediatric patients with paranasal sinus mucoceles presenting with epiphora over 13 years at a tertiary dacryology centre. Demographics, meticulous history, visual acuity, ophthalmic evaluation, lacrimal irrigation, and endoscopic evaluation of the nostril were documented. Computed tomography scans were performed in all patients. All patients underwent an endoscopic endonasal marsupialization of the mucocele. Functional improvements in epiphora and external signs were analysed.
Results:
Six paediatric patients with a mean age of 12.83 years and equal sex distribution were included. The main presenting complaint was epiphora in all children and proptosis in one over an average period of 2.4 years. One child had history of trauma. External examination showed a telecanthus in all children and proptosis or dystopia in four. One child with prior trauma had a secondary acquired nasolacrimal duct obstruction (SALDO), while the others had freely patent irrigation. Four patients had ethmoidal and two had fronto-ethmoidal mucoceles, compressing the lacrimal drainage passage. After the endoscopic endonasal marsupialization of the mucocele, five children had relief from the epiphora with reduction in the proptosis and telecanthus. The patient with traumatic SALDO underwent additional endoscopic dacryocystorhinostomy and did well.
Conclusions:
Paediatric sinus mucoceles are rare cases with very subtle signs, often presenting first to an ophthalmologist. Thus, vigilance and knowledge about the entity is necessary to identify and manage it in early stages.