Related Experiment Video
Updated: Jan 13, 2026
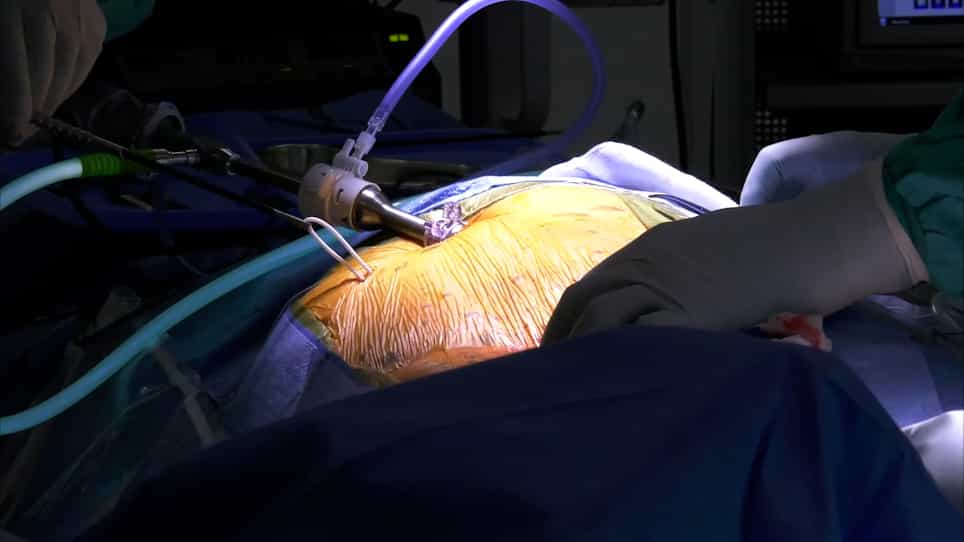
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
A Systematic Review of Ventriculoperitoneal Shunt Valve Types and Failure Rates in Paediatric Hydrocephalus
1Surgery, Mater Dei Hospital, Msida, MLT.

Insights
Paediatric hydrocephalus shunt valves frequently fail, necessitating frequent revisions. This review found no single valve type superior, emphasizing individualized selection based on patient factors for better outcomes in children with hydrocephalus.
Area of Science:
- Neurosurgery
- Paediatric Neurology
- Biomedical Engineering
Background:
- Paediatric hydrocephalus is a major cause of childhood morbidity.
- Ventriculoperitoneal (VP) shunts are the primary treatment, but valve failure leads to high revision rates.
- Comparing different VP shunt valve types is crucial for improving patient outcomes.
Purpose of the Study:
- To systematically review and compare the survival rates and complication profiles of various VP shunt valve types in paediatric hydrocephalus.
- To assess revision requirements and identify factors influencing shunt failure.
- To provide evidence-based guidance for optimal shunt valve selection in children.
Main Methods:
- Systematic literature search across major databases (PubMed, Google Scholar, Scopus, Cochrane Library).
- Inclusion of RCTs, cohort studies, systematic reviews, and meta-analyses comparing at least two VP shunt valve types in patients ≤18 years.
- Data synthesis through narrative review and random-effects meta-analysis, focusing on shunt survival and complication rates.
Main Results:
- No specific shunt valve design demonstrated consistent superiority in overall survival.
- Adjustable valves showed potential in reducing early revisions, especially in young children.
- Gravitational and flow-regulated valves mitigated overdrainage but increased underdrainage risks; obstruction was the most common failure.
- Infants and patients with post-haemorrhagic hydrocephalus exhibited higher shunt failure rates.
Conclusions:
- Current VP shunt valve technology does not offer a universally superior option for paediatric hydrocephalus.
- Individualized valve selection considering patient age, hydrocephalus aetiology, and clinical context is recommended.
- Further multicentre trials with standardized outcomes are needed to refine optimal valve choice strategies.
Abstract:
Paediatric hydrocephalus remains a significant cause of morbidity, primarily managed by ventriculoperitoneal (VP) shunts. Despite technological advances, shunt valves frequently fail, resulting in high revision rates. This systematic review aims to evaluate and compare shunt valve types in paediatric hydrocephalus, assessing survival rates, complication profiles, and revision requirements. A systematic search was conducted using PubMed, Google Scholar, Scopus, and Cochrane Library databases. Eligible studies included randomised controlled trials (RCTs), cohort studies, systematic reviews, and meta-analyses comparing at least two valve types (adjustable, fixed-pressure, gravitational, anti-siphon, or flow-regulating) in patients aged ≤18 undergoing initial VP shunt insertion. Data were synthesised narratively and, where appropriate, via random-effects meta-analysis, using shunt survival as the primary outcome. Secondary outcomes included types of shunt failure, revision rates, time to first revision, and the influence of patient-related factors. Fourteen studies met the inclusion criteria, comprising one meta-analysis, three systematic reviews, two RCTs, and eight observational studies. No valve design consistently demonstrated superior overall shunt survival (RR 1.12, 95% CI: 0.91-1.36, I² = 69%). Adjustable valves reduced early revisions, particularly in young patients with dynamic cerebrospinal fluid (CSF) physiology. Gravitational and flow-regulated valves lowered overdrainage complications but increased underdrainage risks. Obstruction was the predominant failure type across valve types. Higher failure rates occurred in infants and those with post-haemorrhagic hydrocephalus. No single shunt valve type emerged as universally superior. Valve selection should be individualised based on patient age, aetiology, and clinical context. Future multicentre trials using standardised outcomes are needed to guide optimal valve choice.

