Related Experiment Video
Updated: Jan 13, 2026
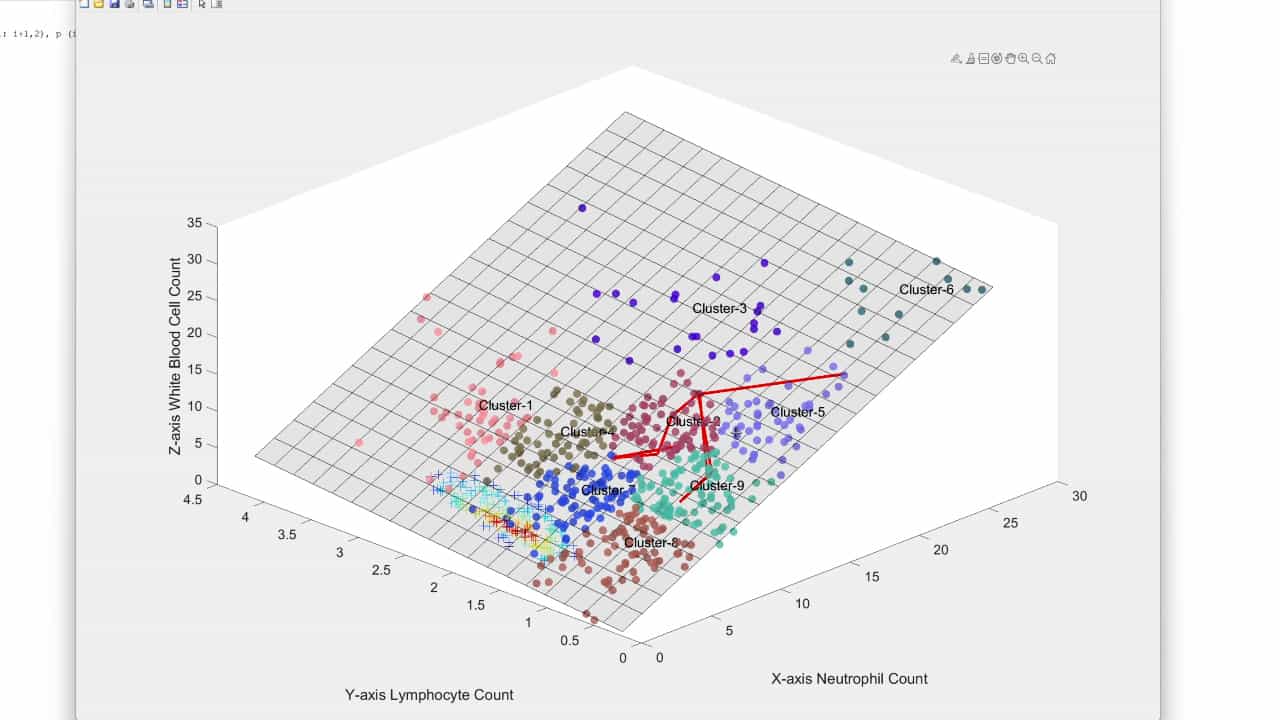

A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Therapeutic Plasma Exchange in COVID-19-Associated Sepsis: IL-6 Dynamics, Inflammatory Phenotypes, and Short-Term
Nicoleta Sgavardea1, Dorel Sandesc2, Tamara Mirela Porosnicu2
1Doctoral School, "Victor Babes" University of Medicine and Pharmacy, Eftimie Murgu Square 2, 300041 Timisoara, Romania.

Abstract:
Background and Objectives: In severe COVID-19-associated sepsis, therapeutic plasma exchange (TPE) is used as a rescue strategy to modulate cytokine and coagulation derangements, but its biomarker and organ-failure effects remain incompletely characterised. We evaluated peri-procedural changes in interleukin-6 (IL-6), other inflammatory markers, and Sequential Organ Failure Assessment (SOFA) scores according to TPE intensity, timing, and inflammatory phenotypes. Methods: We conducted a single-centre retrospective cohort study including 102 mechanically ventilated adults with COVID-19-associated sepsis who received ≥1 TPE session. Patients were grouped by number of sessions (1, 2, ≥3), timing (≤14 vs. >14 days from symptom onset), IL-6 responder status (≥50% reduction), and two unsupervised inflammatory-thrombotic clusters. Peri-procedural changes (Δ) in biomarkers and SOFA were compared using non-parametric tests, with multivariable logistic and linear regression exploring predictors of IL-6 response and ΔSOFA. Results: Baseline severity was similar across TPE-intensity groups, with median APACHE II scores of 11-12 and SOFA scores around 7 in all strata. Median IL-6 concentrations declined after TPE in each group (e.g., Δ -59.4 pg/mL after 1 session and Δ -65.1 pg/mL after ≥3 sessions), but between-group differences in ΔIL-6 were not statistically significant (p = 0.276). By contrast, D-dimer exhibited a marked decline only in the 1-session group (median Δ -1.7 mg/L vs. ~0.0 mg/L in the 2- and ≥3-session groups; p < 0.001). Timing (early vs. late TPE) did not materially affect ΔIL-6, ΔCRP, ΔSOFA (median 0.0 in both), or ΔD-dimer. Overall, 50% of patients were IL-6 responders; baseline IL-6 was the only independent predictor (adjusted OR 1.9 per doubling, 95% CI 1.3-2.8). A hyperinflammatory-thrombotic cluster (n = 44) exhibited higher baseline IL-6 (612.3 vs. 92.4 pg/mL), more ≥3-session TPE (65.9% vs. 29.3%), and higher IL-6 responder rates (75.0% vs. 31.0%), but similar 28-day mortality (40.9% vs. 29.3%). Conclusions: In this real-world TPE programme, biochemical improvements-particularly IL-6 and D-dimer reductions in hyperinflammatory-thrombotic patients-were not consistently accompanied by short-term SOFA or survival benefits, underscoring the need for phenotype-guided and trial-based use.


Related Concept Videos
 01:29
Acute Kidney Injury II: Pathophysiology
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury I: Introduction