Related Experiment Video
Updated: Jan 13, 2026
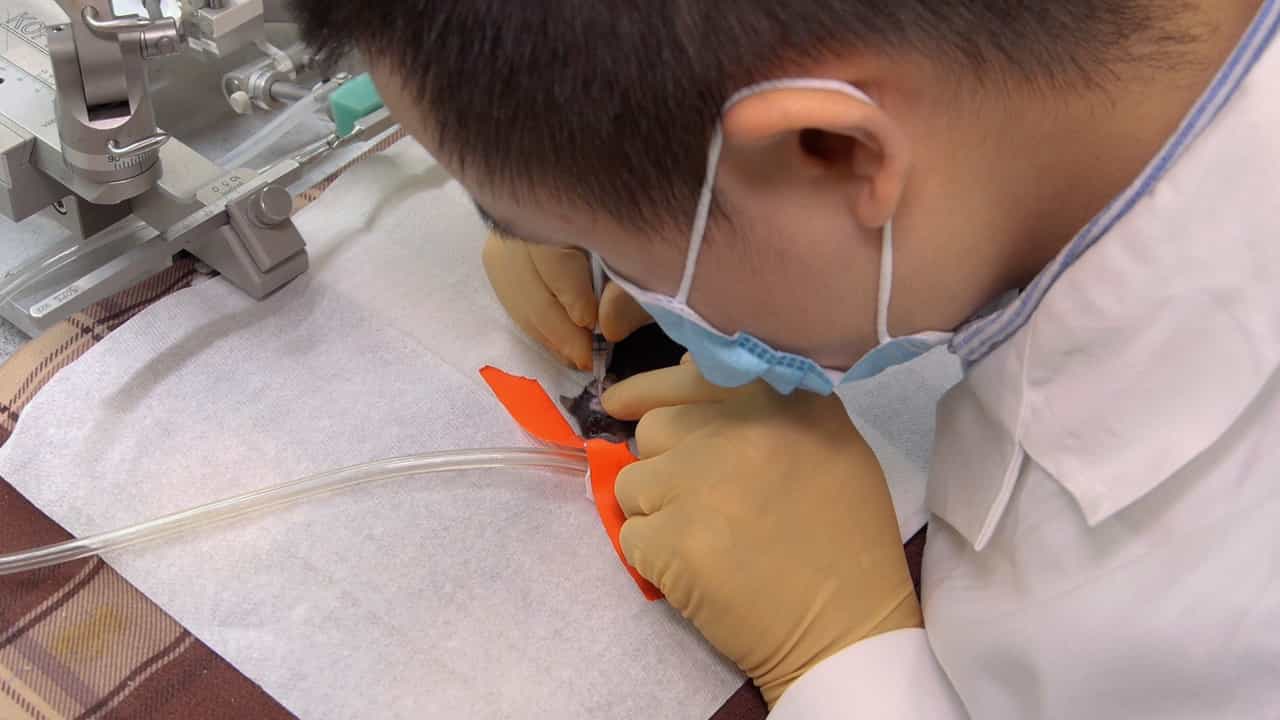

Temporomandibular Joint Pain Measurement by Bite Force and Von Frey Filament Assays in Mice
Published on: September 13, 2024
Temporomandibular Disorders and Orofacial Outcomes in Subjects with Neck Pain and/or Cervicogenic Headache: A
Paolo Bizzarri1,2, Andrea Giusti2, Marco Pernici2
1Experimental Anatomy Research Group (EXAN), Vrije Universiteit Brussel (VUB), B-1090 Brussels, Belgium.

Abstract:
Introduction: Temporomandibular disorders (TMDs), neck pain (NP), and cervicogenic headache (CGH) frequently co-occur. We aimed to assess TMD prevalence and orofacial clinical features in adults with NP or CGH versus asymptomatic controls. Methods: We searched PubMed, CINAHL, Web of Science, and Scopus from inception to 31 July 2025. Eligible designs were analytical cross-sectional studies comparing TMD prevalence, signs, or symptoms between NP/CGH patients and controls. Outcomes included TMD prevalence, jaw mobility, masticatory muscle pressure pain thresholds (PPT), and palpation findings. Risk of bias was appraised with the JBI analytical cross-sectional checklist. Random-effects meta-analyses synthesized odds ratios (ORs) for dichotomous and mean/standardized mean differences (MDs/SMDs) for continuous outcomes; heterogeneity was quantified with I2 (and τ2 where available). Small-study effects were inspected visually (k < 10). Certainty of evidence was assessed with GRADE. Results: From 4130 records, nine studies met the criteria (eight NP, 400 subjects; one CGH, 44 subjects). NP was associated with higher TMD prevalence versus controls (OR 3.64, 95% CI 1.35-9.84; I2 = 13%). Jaw mobility was reduced in either pain-free opening (one study), unassisted opening (one study), or maximum assisted opening (three studies; MD -6.16 mm, 95% CI -10.05; -2.28; I2 = 83%). PPTs were lower in symptomatic groups for masseter (SMD -1.11, 95% CI -1.89 to -0.32; three studies; I2 = 92.6%) and temporalis (SMD -0.77, 95% CI -1.04 to -0.50; five studies; I2 = 69%). Myofascial trigger points and pain on palpation of masticatory muscles or TMJ were more frequent in experimental groups. Discussion: The findings suggest consistent associations between NP/CGH and TMD prevalence with signs of orofacial dysfunctions. Certainty of evidence was very low due to the cross-sectional design, incomplete confounding control, and moderate heterogeneity for several outcomes. Conclusions: Adults with NP/CGH show higher TMD prevalence and reduced jaw mobility with lower masticatory PPTs. The results support integrated assessment, and prospective longitudinal studies are needed.


