Related Experiment Video
Updated: Jan 13, 2026
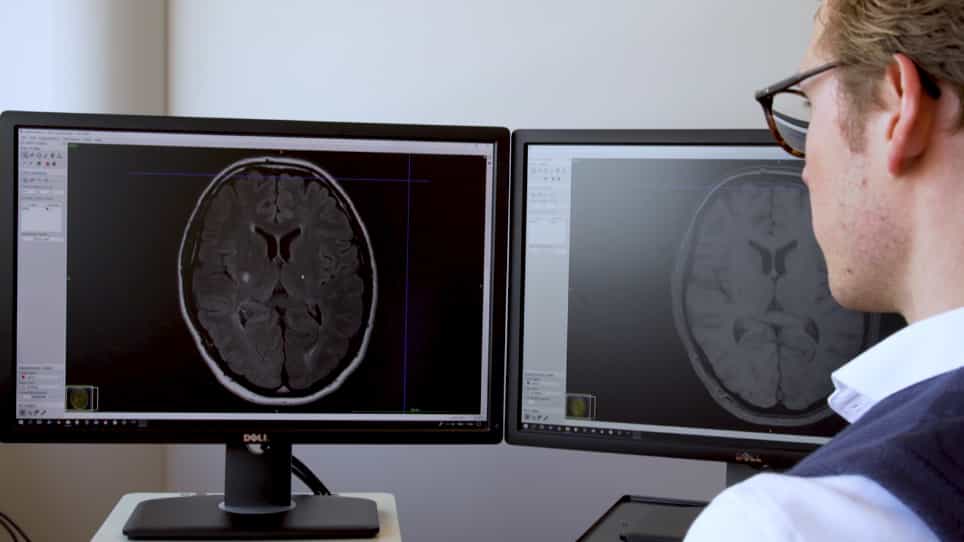

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Development and internal validation of a multimodal nomogram integrating clinical, imaging, and laboratory data to
Wenhao Gong1, Haotian Xia2, Shuguang Chu2
1Department of Radiology, Shanghai Seventh People's Hospital Affiliated to Shanghai University of Traditional Chinese Medicine, Shanghai, China.

Background:
Malignant brain edema (MBE) is a life-threatening complication of acute ischemic stroke (AIS) after reperfusion therapy, often leading to fatal herniation or severe disability. Early identification of patients at high risk for MBE is critical but remains challenging due to limited predictive tools. In this study, we aimed to develop and internally validate a multimodal nomogram integrating clinical, imaging, and laboratory variables to predict MBE after reperfusion in anterior-circulation large vessel occlusion (LVO) stroke.
Methods:
We retrospectively enrolled 214 consecutive AIS patients who underwent mechanical thrombectomy between 2018 and 2023. After standardizing candidate variables, we performed least absolute shrinkage and selection operator (LASSO)-logistic regression with the one-standard-error rule and stratified five-fold cross-validation for variable selection and collinearity handling. Selected variables were entered into a multivariable logistic model to construct the nomogram. Model discrimination [area under the curve (AUC)] and Brier score were evaluated using stratified five-fold out-of-fold predictions. Calibration was assessed by bootstrap resampling (B=1,000) with reporting of calibration slope, intercept, and the Hosmer-Lemeshow test P value. Clinical utility was examined using decision curve analysis (DCA) and a clinical impact curve (CIC).
Results:
MBE occurred in 62 patients (29%). The final model included seven predictors: relative cerebral blood flow (rCBF) <40% volume, delay time (DT) >6.0 s volume, infarct growth rate (IGR), diastolic blood pressure (DBP), neutrophil count (N), collateral circulation score (CCS), and lactate dehydrogenase (LDH). Apparent AUC in the modeling cohort was 0.87 [95% confidence interval (CI): 0.82-0.93]; five-fold out-of-fold AUC was 0.860. After 1,000-bootstrap optimism correction, AUC was 0.85 (95% CI: 0.80-0.91) with a Brier score of 0.13. The calibration slope was ~0.86, the intercept was near 0, and Hosmer-Lemeshow P=0.173. DCA showed net benefit across probability thresholds of 0.10-0.70, and the CIC indicated good identification of high-risk individuals.
Conclusions:
A LASSO-selected, internally validated nomogram enables early risk stratification and decision support for MBE after reperfusion in AIS. Prospective external validation in independent cohorts is required before clinical adoption to confirm reliability and generalizability.
More Related Videos
 04:32
Measuring Post-Stroke Cerebral Edema, Infarct Zone and Blood-Brain Barrier Breakdown in a Single Set of Rodent Brain Samples
Published on: October 23, 2020
 09:48
Quantification of Neurovascular Protection Following Repetitive Hypoxic Preconditioning and Transient Middle Cerebral Artery Occlusion in Mice
Published on: May 4, 2015