Related Experiment Video
Updated: Jan 13, 2026
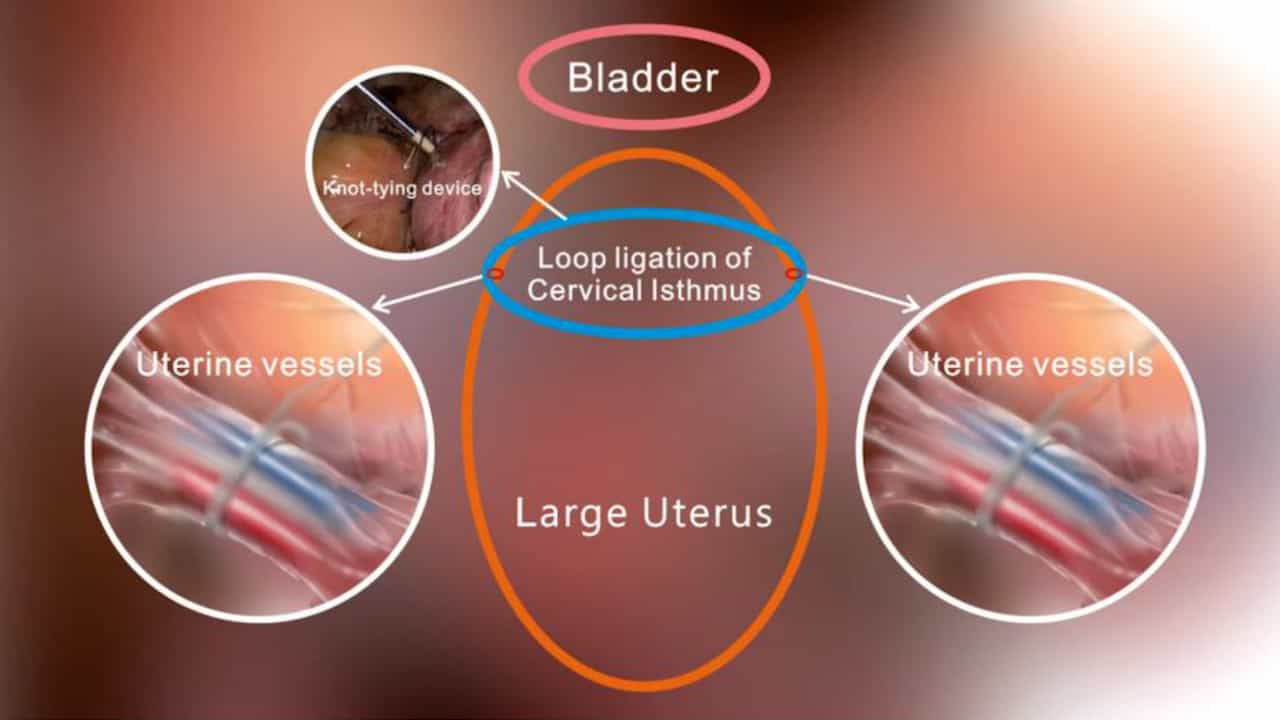

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Massive Hemoperitoneum Caused by Rupture of a Superficial Vessel on a Large Pedunculated Uterine Leiomyoma: A Case
Riho Seki1, Takeshi Fukuda1, Reiko Tasaka1
1Department of Obstetrics and Gynecology, Osaka Metropolitan University Graduate School of Medicine, Osaka, JPN.

Spontaneous hemoperitoneum caused by a uterine leiomyoma is an exceptionally rare but potentially life-threatening condition. We report the case of a 40-year-old woman who presented with sudden-onset severe abdominal pain and hemorrhagic shock. Focused sonography revealed massive hemoperitoneum, and contrast-enhanced computed tomography demonstrated intra-abdominal bleeding associated with a large uterine mass. Emergency laparotomy revealed a large pedunculated leiomyoma with rupture of a superficial vessel on its surface, without evidence of torsion. Approximately 2,250 mL of blood was lost, and myomectomy was performed because the fibroid could be rapidly and safely excised by transecting the stalk, and the patient wished to preserve fertility. The postoperative course was uneventful, and histopathology confirmed a benign leiomyoma. Rupture of superficial vessels overlying uterine fibroids is extremely uncommon but should be considered in women presenting with hemoperitoneum of unknown origin, especially those with large leiomyomas. Early recognition and prompt surgical intervention are essential to prevent severe morbidity or mortality. This case underscores the importance of including the vascular rupture of a leiomyoma in the differential diagnosis of an acute abdomen.
Spontaneous hemoperitoneum caused by a uterine leiomyoma is an exceptionally rare but potentially life-threatening condition. We report the case of a 40-year-old woman who presented with sudden-onset severe abdominal pain and hemorrhagic shock. Focused sonography revealed massive hemoperitoneum, and contrast-enhanced computed tomography demonstrated intra-abdominal bleeding associated with a large uterine mass. Emergency laparotomy revealed a large pedunculated leiomyoma with rupture of a superficial vessel on its surface, without evidence of torsion. Approximately 2,250 mL of blood was lost, and myomectomy was performed because the fibroid could be rapidly and safely excised by transecting the stalk, and the patient wished to preserve fertility. The postoperative course was uneventful, and histopathology confirmed a benign leiomyoma. Rupture of superficial vessels overlying uterine fibroids is extremely uncommon but should be considered in women presenting with hemoperitoneum of unknown origin, especially those with large leiomyomas. Early recognition and prompt surgical intervention are essential to prevent severe morbidity or mortality. This case underscores the importance of including the vascular rupture of a leiomyoma in the differential diagnosis of an acute abdomen.