Related Experiment Video
Updated: Jan 14, 2026
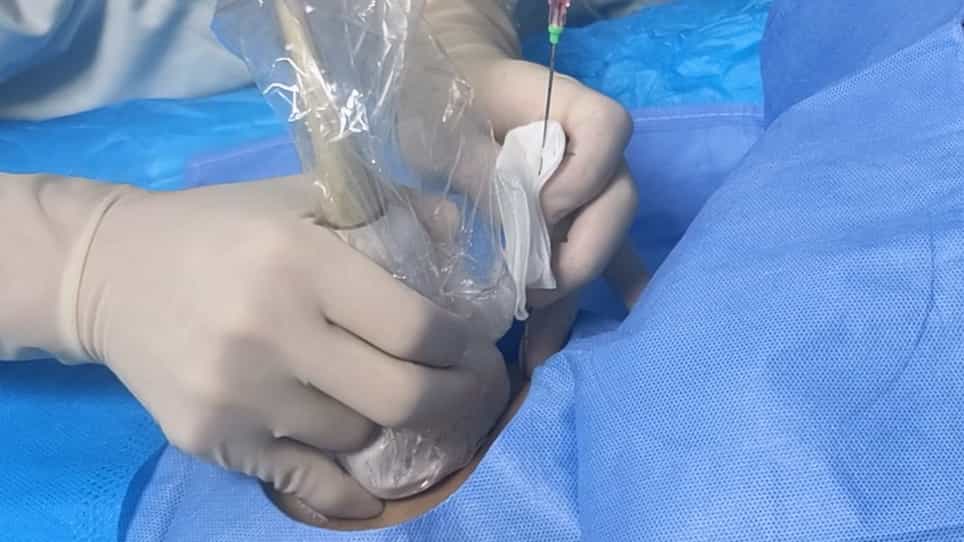
A Two-Step Method for Percutaneous Transhepatic Choledochoscopic Lithotomy
Published on: September 13, 2022
Management of Thoracic Complications After Supracostal Mini-Percutaneous Nephrolithotomy in Pediatric Patients: An
1Urology, Institute of Kidney Diseases, Peshawar, PAK.

Abstract:
Objective The main objective of this study is to assess the frequency and management of thoracic complications following supracostal mini-percutaneous nephrolithotomy (mini-PCNL) in pediatric patients. Methods This retrospective cross-sectional study was conducted in the Department of Urology, Institute of Kidney Diseases, Peshawar, Pakistan, from June 2017 to December 2019. A total of 80 pediatric patients (52 males, 65%, and 28 females, 35%) who underwent supracostal mini-PCNL were included. Patients were categorized according to the level of puncture: Group 1 (between the 11th and 12th ribs; n = 62, 77.5%), Group 2 (between the 10th and 11th ribs; n = 15, 18.75%), and Group 3 (between the 9th and 10th ribs; n = 3, 3.75%). Postoperative thoracic complications, including hydrothorax and hemothorax, were documented and managed either conservatively, by needle aspiration, or by intercostal chest tube insertion. Results Among the 80 patients, 12 (15%) developed hydrothorax. Although thoracic complications were observed in 6/62 (9.6%) in Group 1, 3/15 (20%) in Group 2, and 3/3 (100%) in Group 3, the interpretation of the 100% complication rate in Group 3 should be made with caution, because this group contained only three patients, limiting the statistical power despite the anatomical plausibility of higher complications at higher intercostal levels. Of the affected patients, six (50%) were managed conservatively, four (33.3%) required needle aspiration, and two (16.6%) underwent intercostal chest tube insertion. The mean hospital stay among patients with thoracic complications was 2.3 days. Conclusion The likelihood of thoracic complications following supracostal mini-PCNL in pediatric patients increases with higher intercostal access. While punctures above the 10th rib carry a 100% risk of hydrothorax, most cases can be managed conservatively through timely recognition and multidisciplinary collaboration among urologists, anesthetists, and pulmonologists. A meticulous surgical approach and careful perioperative monitoring significantly reduce morbidity.
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Urinary Tract Calculi V: Nursing Management
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:30
Urinary Tract Calculi III: Medical Management