Related Experiment Video
Updated: Jan 15, 2026


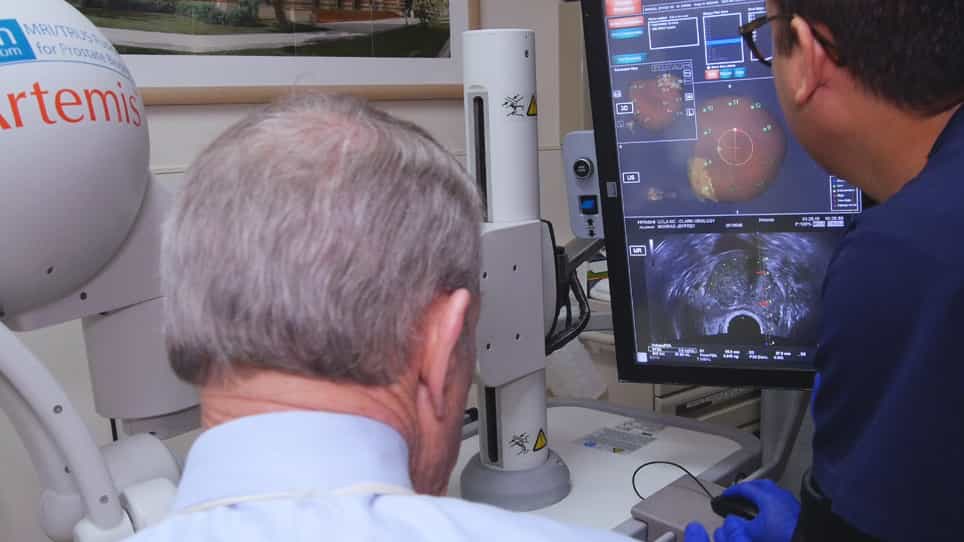
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Development and Validation of a Clinical-Quantitative MRI Model for Predicting Clinically Significant Prostate Cancer
Dongwei Wang1, Lijun Tang1, Ying Duan1
1Department of Nuclear Medicine, The First Affiliated Hospital of Nanjing Medical University, 300 Guangzhou Road, Nanjing 210029, China.

Aim:
This study aimed to develop and validate a clinical-MRI quantitative parameter model to predict clinically significant prostate cancer (csPCa) in PI-RADS score 3 lesions.
Methods:
A retrospective analysis was performed on 151 patients with PI-RADS score 3 lesions, divided into csPCa and non-csPCa groups according to pathological results. Patients were randomly assigned into training and validation cohorts in a 7:3 ratio. Quantitative values of T1, T2, and proton density (PD) were obtained from the synthetic magnetic resonance imaging (syMRI) quantitative maps, while apparent diffusion coefficient (ADC) values were derived from ADC maps. Independent predictors were identified using univariate and multivariate logistic regression analyses, based on which a quantitative parameter model was established. Clinical risk factors were used to construct a clinical model, and a combined model integrating both clinical and imaging predictors was developed. The predictive performance of the models was evaluated using the area under the curve (AUC), calibration curves, and decision curve analysis (DCA). The DeLong test was applied to compare the diagnostic efficiency between models.
Results:
Multivariate logistic regression analysis revealed that prostate volume (PV) and prostate-specific antigen density (PSAD) were independent clinical predictors for csPCa, while T2 and ADC values were independent imaging predictors. In the training cohort, the combined model achieved an AUC of 0.91 (95% CI: 0.86-0.97), outperforming the clinical model (AUC = 0.76, 95% CI: 0.66-0.85, P = 0.001) and the quantitative parameter model (AUC = 0.84, 95% CI: 0.76-0.93, P = 0.017). DCA demonstrated that the combined model provided greater net clinical benefit compared to either model alone.
Conclusion:
The clinical-quantitative parameter combined model can effectively identify csPCa within PI-RADS score 3 lesions based on syMRI, thereby guiding biopsy decisions, reducing unnecessary invasive procedures, and improving patients' quality of life.