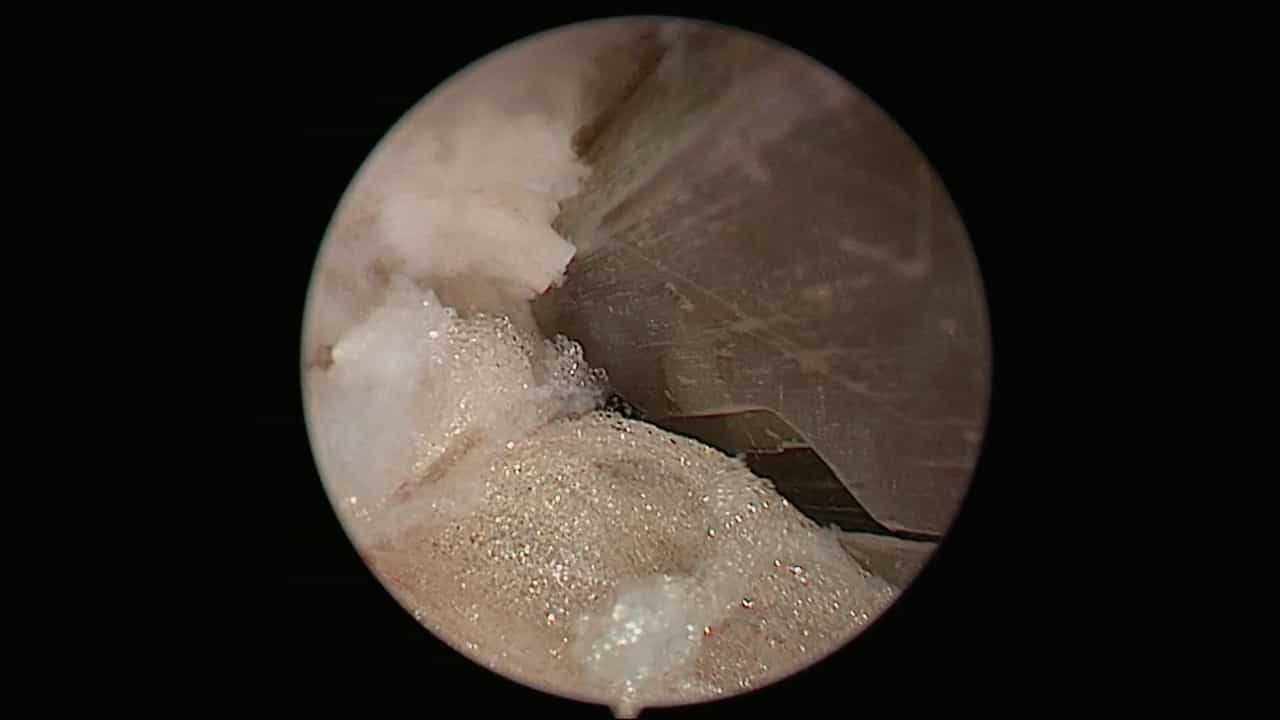
Related Experiment Video
Updated: May 5, 2026
Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Delta large-channel endoscopy versus unilateral biportal endoscopy for cervicothoracic junction disc herniation: a
Huaibin Wang1,2, Hui Li3, Rushuo Wei1,2
1Department of Spinal Surgery, Weifang People's Hospital, Shandong Second Medical University, 151 Guangwen Street, Kuiwen District, Weifang, 261000, Shandong, China.

Insights
The Delta large-channel endoscopic approach for cervicothoracic junction disc herniation (CTJDH) showed less blood loss and quicker recovery than unilateral biportal endoscopy (UBE). However, UBE may be better for patients with osteophytes.
Area of Science:
- Minimally Invasive Spine Surgery
- Cervicothoracic Junction Disorders
- Endoscopic Spinal Decompression
Background:
- Anterior surgical approaches for cervicothoracic junction disc herniation (CTJDH) are challenging due to anatomical obscuration.
- Posterior decompression techniques, including Delta large-channel endoscopy and unilateral biportal endoscopy (UBE), offer promising alternatives.
- This study prospectively compares the clinical outcomes of Delta and UBE endoscopic surgeries for CTJDH.
Purpose of the Study:
- To compare the clinical efficacy and safety of Delta large-channel endoscopy versus unilateral biportal endoscopy (UBE) for treating CTJDH.
- To evaluate differences in patient outcomes, including functional recovery, pain reduction, and surgical parameters.
Main Methods:
- A prospective randomized controlled study involving 63 patients with CTJDH, assigned to either the Delta (n=32) or UBE (n=31) group.
- Primary outcome measures included the Neck Disability Index (NDI) and intraoperative blood loss (IBL).
- Secondary outcomes assessed included VAS pain scores, JOA scores, operative time, hospital stay, complications, and radiographic parameters.
Main Results:
- The Delta group demonstrated significantly lower NDI scores at postoperative day 14 and one month compared to the UBE group.
- Intraoperative blood loss was significantly lower in the Delta group (p < 0.001), and postoperative VAS scores were also lower at multiple time points.
- The UBE group had a shorter operative time (p < 0.001), while both techniques improved radiographic parameters (Cobb angle, cSVA). Delta group patients with osteophytes showed poorer NDI scores.
Conclusions:
- Both Delta and UBE endoscopic approaches are safe and effective for CTJDH treatment.
- The Delta technique offers advantages in reduced blood loss and faster initial recovery but has a longer operative time.
- UBE may provide comparable outcomes for CTJDH with osteophytes, suggesting individualized treatment selection based on patient anatomy.
Background:
Due to the obscuration by the sternum, trachea, and major blood vessels, the anterior surgical approach for cervicothoracic junction disc herniation (CTJDH) is extremely challenging. Delta large-channel endoscopy and unilateral biportal endoscopy (UBE) provide posterior decompression and have demonstrated promising clinical potential. This prospective randomized controlled study aims to compare the clinical outcomes of Delta and UBE endoscopic surgeries.
Methods:
A total of 63 patients were randomly assigned to either the Delta group (n = 32) or the UBE group (n = 31). The primary outcomes were the Neck Disability Index (NDI) and intraoperative blood loss (IBL). Secondary outcomes included VAS, JOA scores, modified MacNab criteria, operative time, hospital stay duration, perioperative complications, and radiographic parameters.
Results:
During the follow-up period, 62 patients (98.4%) completed the 6-month assessment. The Delta group consistently demonstrated lower NDI scores than the UBE group. Significant differences were observed at postoperative day 14 (p = 0.040) and one month (p = 0.035), favoring the Delta technique. Intraoperative blood loss was significantly lower in the Delta group than in the UBE group (p < 0.001). At postoperative day 3 (p = 0.037), day 7 (p = 0.034), day 14 (p = 0.041), and 1 month (p = 0.027), neck VAS scores were lower in the Delta group. Operative time was shorter in the UBE group (p < 0.001). Both groups showed significant postoperative increases in the C2-C7 Cobb angle (p < 0.001) and reductions in cervical sagittal vertical axis (cSVA) (p < 0.05). Delta group patients with osteophytes had consistently higher NDI scores than those without osteophytes.
Conclusion:
Both surgical techniques demonstrated favorable safety profiles and clinical efficacy in the treatment of CTJDH. Compared with UBE, the Delta large-channel endoscopic approach resulted in less intraoperative blood loss and faster postoperative recovery, although it required a longer operative time. For patients with CTJDH accompanied by osteophytes or bony overgrowth, UBE provided equally satisfactory outcomes, whereas the Delta technique showed relatively poorer results in such cases. Therefore, the choice of surgical approach should be individualized based on each patient's anatomical characteristics and clinical presentation. Trial registration Name of the registry: Chinese Clinical Trial Registry chictr.org.cn. Unique Identifying number or registration ID: ChiCTR2500097522.