Related Experiment Video
Updated: Jan 20, 2026
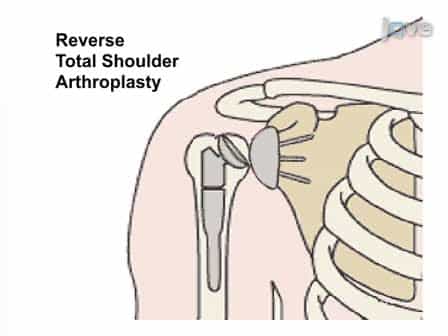

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
An Anatomic Study of the Human Glenoid Fossa: Implications for Preoperative Evaluation of Bone Loss in Patients With
Aaron J Bois1,2, Alexander C Rothy3, Anish Ghodadra4
1Section of Orthopaedic Surgery, Department of Surgery, Cumming School of Medicine, University of Calgary, Calgary, Alberta, Canada.

Background:
Current methods to quantify glenoid bone loss after anterior shoulder instability assume that the inferior glenoid fossa represents a perfect circle with minimal side-to-side variability.
Purposes/Hypotheses:
The purpose of this study was to (1) determine normal glenoid parameters-including height, width, surface area (SA), and shape of the glenoid fossa as a function of glenoid notch type-and (2) characterize whether side-to-side, sex- and race-based differences exist in these parameters. It was hypothesized that the inferior glenoid would be better represented as an ellipse rather than a perfect circle, that side-to-side differences in glenoid SA would exist as a function of notch type, and that there would be sex and race-based differences for all other measured variables.
Study Design:
Descriptive laboratory study.
Methods:
A total of 58 pairs of human scapulae from individuals between 18 and 35 years of age at the time of death were randomly selected and stratified according to human race and sex. All specimens were digitized using a 3-dimensional laser scanner, and all parameters were calculated using MATLAB software. Descriptive statistics were computed on all dependent variables and were stratified by sex, race, and side. Generalized estimating equations models were used to compare group means. Intra- and interrater reliability of the notch classification was assessed.
Results:
Of the 58 matched left and right pairs (116 glenoid specimens), there were 30 Black women, 30 Black men, 26 White women, and 30 White men. Small but statistically significant side-to-side differences were found for nearly all linear and SA measurements. The left glenoid parameters, on average, have larger glenoid height (0.37 mm [95% CI, 0.15 to 0.59]; P = .001), larger width (0.27 mm [95% CI, 0.05 to 0.49 mm]; P = .017), larger total glenoid SA (22.3 mm2 [95% CI, 15.2 to 29.5 mm2]; P≤ .001), and larger inferior glenoid SA (11.9 mm2 [range, 3.11 to 20.6mm2]; P = .008) compared with the right side. Women, on average, have smaller linear parameters-including glenoid height (-3.06 mm [95% CI, -4.08 to -2.04 mm]; P < .001), glenoid width (-2.93 mm [95% CI, -3.71 to -2.14 mm]; P < .001), glenoid width-to-height ratio (-0.02 [95% CI, -0.04 to 0 mm]; P = .034), anterior glenoid width (-0.82 mm [95% CI, -1.36 to -0.27]; P = .003), and posterior glenoid width (-2.11 mm [95% CI, -2.71 to -1.50 mm]; P < .001), and smaller SA measurements-including total glenoid SA (-139.9 mm2 [95% CI, -178.1 to -101.6 mm2]; P < .001) and inferior glenoid SA (-23.2 mm2 [95% CI, -158.6 to -87.8 mm2]; P < .001). There were no differences in linear or SA measurements as a function of human race. The inferior aspect of the glenoid articular surface was elliptical in shape. Intraobserver reliability of the notch classification revealed an overall consistency of 0.56 (95% CI, 0.26 to 0.77), while the interobserver reliability kappa coefficient was 0.43 (95% CI, 0.4 to 0.45).
Conclusion:
In this anatomic study, the inferior glenoid fossa was better represented by an ellipse than a circle, and small side-to-side differences were found between linear and SA measurements. The latter 2 findings contradict assumptions made by current techniques for calculating bone loss and therefore raise concern about their validity, especially those that depend on the placement of a circle on the glenoid fossa. Using the contralateral normal total glenoid width or other linear measurements may be considered to calculate the magnitude of glenoid bone loss. However, we do not recommend using contralateral SA measurements for this purpose.
Clinical Relevance:
To our knowledge, this is the first study to define the normal shape and SA of the inferior glenoid fossa in dry specimens and the first to attempt to stratify these data according to the anterior glenoid notch. The data from this study can be used to create validated methods to measure glenoid bone loss preoperatively to help determine when a glenoid bone augmentation procedure is indicated.

Related Concept Videos
 08:30
Intra-articular Shoulder Injection for Reduction Following Shoulder Dislocation
The anterior shoulder dislocation is one of the most common joint dislocations seen in emergency settings. In anterior shoulder dislocation, the humeral head is displaced out of the glenohumeral joint in front of the scapular glenoid, resulting in a loss of the articulation between the arm and the rest of the shoulder. This can be caused by a fall onto an abducted, extended, and externally...
 10:10
Reverse Total Shoulder Arthroplasty
 08:57
Shoulder Exam I
Examination of the shoulder can be complex, because it actually consists of four separate joints: are the glenohumeral (GH) joint, the acromioclavicular (AC) joint, the sternoclavicular joint, and the scapulothoracic joint. The GH joint is primarily responsible for shoulder motion and is the most mobile joint in the body. It has been likened to a golf ball sitting on a tee and is prone to instability. It is held in place...
 04:42
A Personalized 3D-Printed Model for Preoperative Evaluation in Thyroid Surgery
 10:39
Longitudinal Evaluation of Mouse Hind Limb Bone Loss After Spinal Cord Injury using Novel, in vivo, Methodology
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling