Related Experiment Video
Updated: Jan 21, 2026
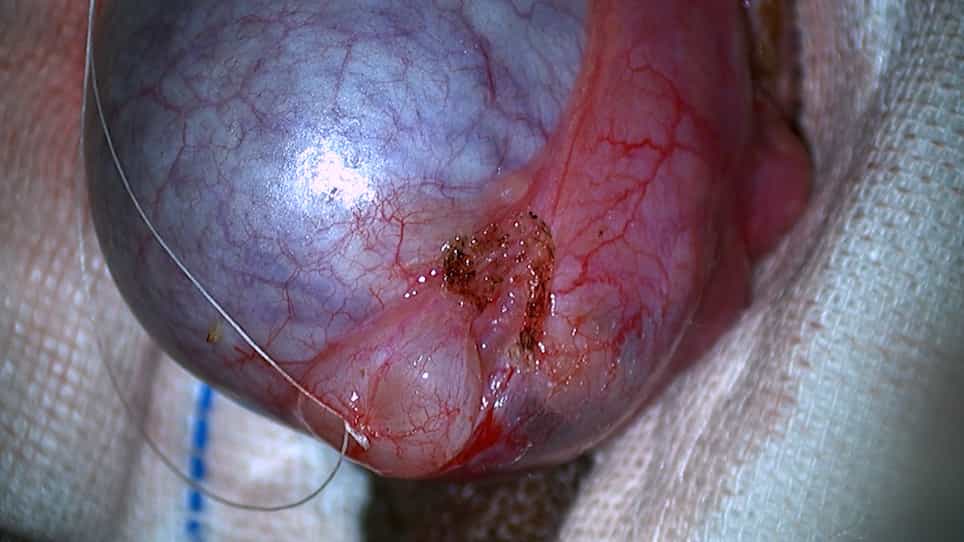

Microscopic Cyst Resection for the Treatment of Patients Diagnosed with Epididymal Cyst
Published on: March 31, 2023
Sinus Lift With Simultaneous Mucous Retention Cyst Drainage for Implant Rehabilitation: Clinical, Tomographic, and
Erick R Silva1, Thales Bianchi1, Letícia G Artioli1
1Department of Oral and Maxillofacial Surgery and Periodontology, Faculty of Dentistry of Ribeirão Preto, University of São Paulo, Ribeirão Preto, BRA.

Abstract:
We aim to report the long-term clinical, tomographic, and histologic outcomes of simultaneous drainage of a maxillary mucous retention cyst (MRC) and lateral sinus floor elevation (SFE), followed by delayed guided implant placement, with a six-year follow-up. A 47-year-old male with an atrophic posterior maxilla (residual bone height (RBH): 1.0 mm) presented with a dome-shaped MRC measuring 22.13 × 15.86 × 27.94 mm (3,266.83 mm³). A lateral window SFE was performed with cyst drainage, careful elevation of the Schneiderian membrane, and grafting using particulate xenograft, covered by a collagen membrane. Cone-beam computed tomography (CBCT) was obtained at one month (T1), eight months (T2), and six years (T3) to assess graft volume and density. At eight months, a guided Ø4.3 × 8.5 mm implant was placed, and a trephine core biopsy was collected for histologic and histomorphometric evaluation. Postoperative healing was uneventful, and the patient remained asymptomatic throughout follow-up. At T1, graft volume was 1,978.61 mm³ (297.24 HU), and the cyst regressed by 6.10% compared with baseline. At T2, graft volume decreased to 1,737.67 mm³ (-12.18% vs. T1), with increased density (690.74 HU), and the MRC was radiographically resolved. Histomorphometric analysis revealed 25.76% new bone, 47.20% residual graft, and 27.04% connective tissue. At T3, graft volume remained 1,508.57 mm³ (-23.76% vs. T1), with a density of 785.91 HU, indicating long-term bone maturation and consolidation. The maxillary sinus remained functional and asymptomatic, with stable peri-implant tissues and no recurrence of the MRC. Simultaneous management of an MRC during lateral SFE allowed safe cyst drainage, predictable graft consolidation, histologic confirmation of new bone formation, and long-term implant success. This single-stage approach represents a pragmatic and effective treatment option in carefully selected cases of atrophic maxilla with cystic sinus lesions.
More Related Videos
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
 07:50
A Metadata Extraction Approach for Clinical Case Reports to Enable Advanced Understanding of Biomedical Concepts
Published on: September 20, 2018
Related Concept Videos
 01:23
Lift
 01:29
Angina III: Clinical Manifestations and Assessment
 01:24
Data Reporting and Recording
 01:20
Cavity Drainage and Flashings in Masonry walls
Weep holes, strategically placed at the base of the cavity, are critical for draining accumulated water. These openings are created by leaving head...
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:26
Stomach Histology