Related Experiment Video
Updated: Jan 22, 2026


Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Conversion From Venovenous to Venoarterial or Hybrid Extracorporeal Membrane Oxygenation: Analysis From the
Maria Elena De Piero1,2, Francesco Alessandri3, Silvia Mariani1,2,4
1Cardio-Thoracic Surgery Department, Cardiovascular Research Institute Maastricht (CARIM), Maastricht University Medical Centre (MUMC+), Maastricht, The Netherlands.

Objectives:
Venovenous extracorporeal membrane oxygenation (ECMO) represents a standard and well-accepted modality of treating patients with refractory respiratory failure. Nevertheless, some patients might develop refractory hypoxemia, hemodynamic compromise or end-organ perfusion requiring a change. This study analyzed characteristics and outcomes of patients requiring a change from venovenous to a different ECMO configuration.
Design:
Multicenter, retrospective, observational analysis of the Extracorporeal Life Support Organization Registry (2010-2020) in adult patients (≥ 18 yr old) underwent venovenous ECMO as initial cannulation strategy.
Setting And Patients:
Comparison of patients who remained on venovenous ECMO vs. those who underwent configuration conversion and multivariable analysis to assess variables associated with configuration change.
Interventions:
None.
Measurements And Main Results:
Among 28,888 eligible venovenous ECMO runs, 702 (2.4%) received a change from the original configuration, including 399 (56.8%) conversions to venoarterial and 303 (43.2%) to hybrid ECMO configurations. Variables associated with conversion included: pre-ECMO cardiac conditions, bridge to lung transplant as indication, use of milrinone, epinephrine, sildenafil, bicarbonate, and 24-hour Pa o2 value. Conversion occurred at a median of 56 hours (interquartile range, 11.5-210 hr) after ECMO initiation, with earlier conversion to hybrid configuration. Increased rates of cardiovascular, hemorrhagic, vascular, renal, metabolic, infective, and circuit-related complications were reported in converted patients. In-hospital mortality was higher in converted patients (60.8%) overall, and highest for venovenous to venoarterial patients (63.2%).
Conclusions:
The venovenous patients converted to other ECMO configurations were 2.4% and experienced higher complication and mortality rates. Variables associated with conversion highlight the importance of initial configuration selection and should be considered as part of the risk stratification framework when evaluating a patient for individualized ECMO support mode/configuration.
More Related Videos
 03:40
Point-of-Care Ultrasound for Peripheral Veno-Arterial Extracorporeal Membrane Oxygenation Without Left Ventricular Venting
Published on: January 17, 2025
 05:21
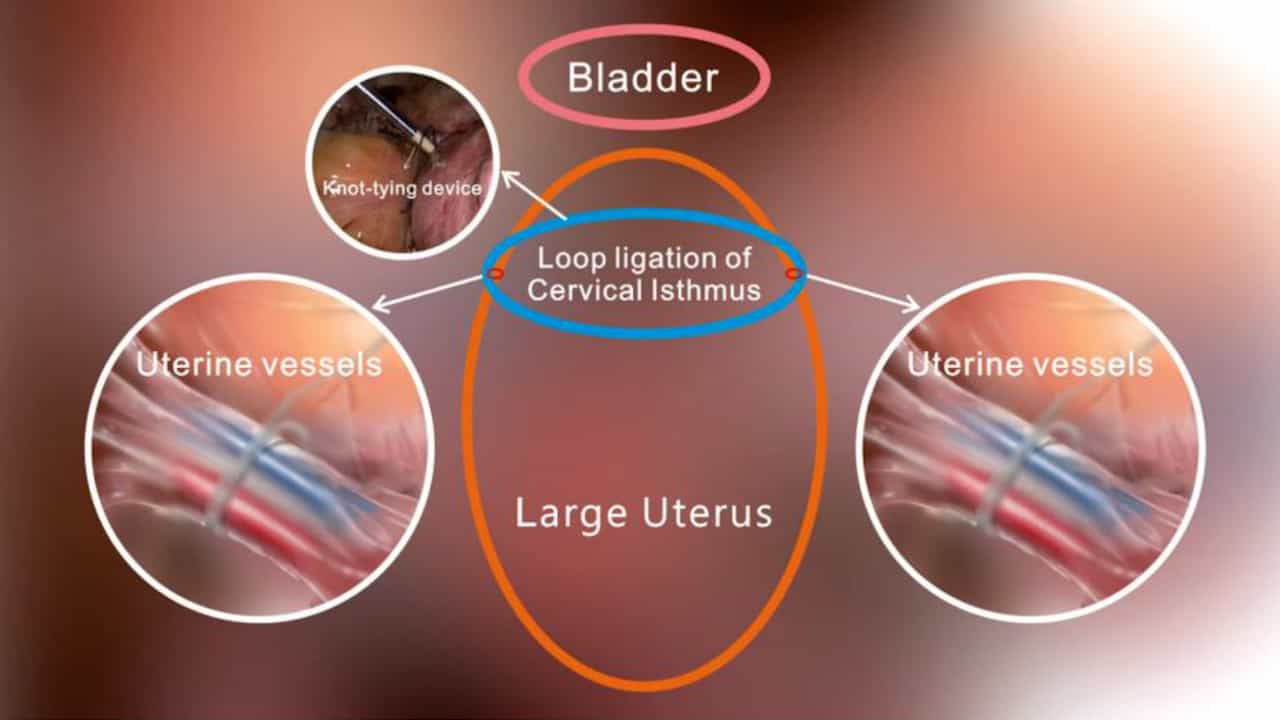
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Related Concept Videos
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration
 01:30
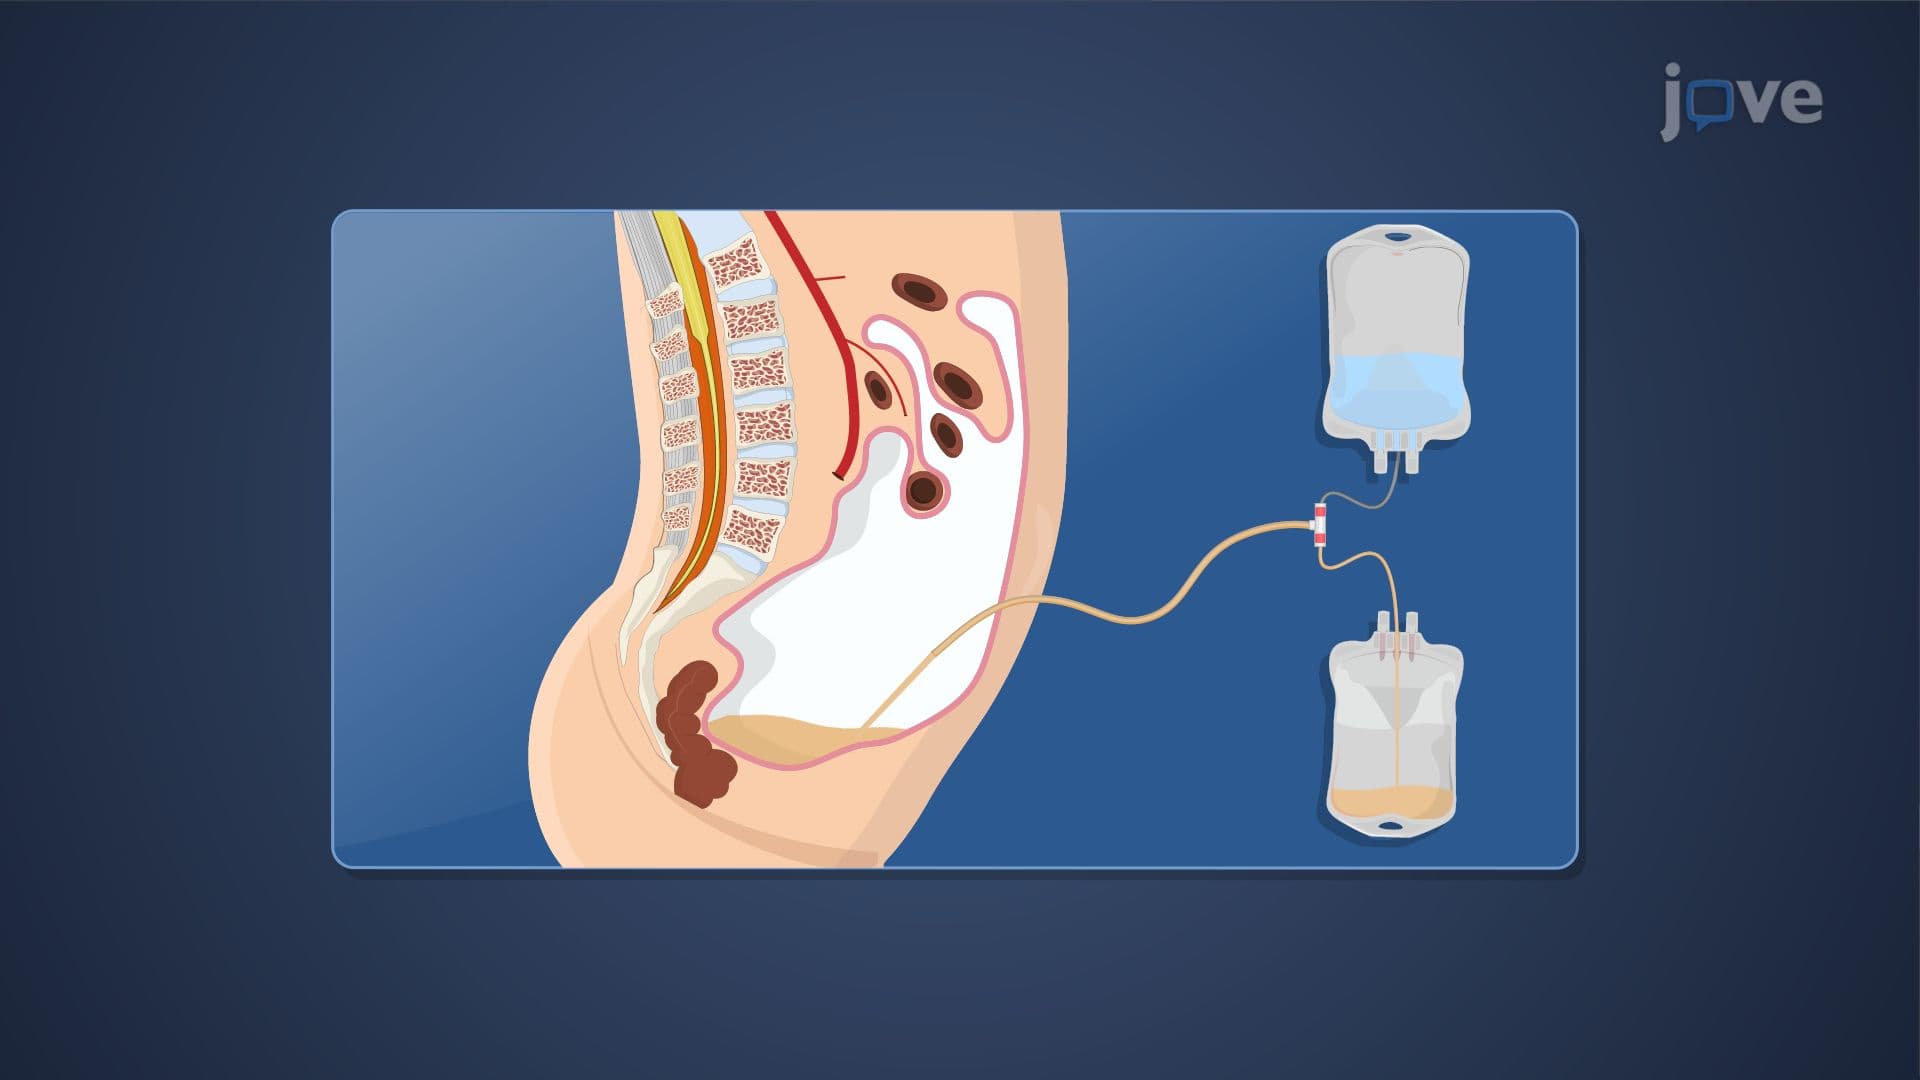
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 02:08
Gene Conversion
02:08Gene Conversion
 02:40
The Tree of Life - Bacteria, Archaea, Eukaryotes