Related Experiment Video
Updated: Jan 22, 2026
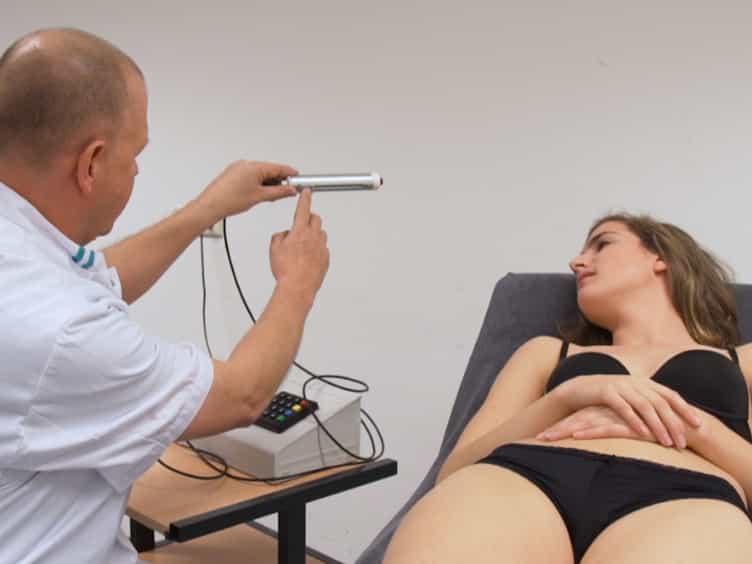
A Quantitative Sensory Testing Paradigm to Obtain Measures of Pain Processing in Patients Undergoing Breast Cancer Surgery
Published on: January 18, 2018
National survey of thromboprophylaxis management and tranexamic acid utilization in patients undergoing non-free flap
Justin Haas1, Ted Zhou2, Kimberley Yuen1
1St. Joseph's Healthcare Hamilton, Hamilton, Ontario, Canada; Division of Plastic Surgery, McMaster University, Hamilton, Ontario, Canada.

Introduction:
Patients undergoing breast surgery are at risk of venous thromboembolism (VTE), but most literature examining thromboprophylaxis management in breast surgery focuses on free flap reconstruction. We evaluated thromboprophylaxis and tranexamic acid (TXA) practices among Canadian plastic surgeons for non-free flap breast surgeries.
Materials/Methods:
An anonymous online survey was distributed to Canadian plastic surgeons in 2025. Data collected included demographics, VTE prophylaxis strategies, and TXA use across nine commonly-performed non-free flap breast procedures. Predictors of thromboprophylaxis and TXA use were identified.
Results:
Sixty-five surgeons nationwide (34% response rate) completed the survey; 43% had completed a breast fellowship. Although 79% reported regular use of VTE risk tools, prophylaxis practices varied widely. The most common threshold for initiating prophylaxis was 2-3 h of operative duration (35%). Mechanical prophylaxis was the least common in breast augmentation (38%), and chemical prophylaxis was the most common in pedicled flap reconstruction (46%). Fellowship-trained surgeons initiated thromboprophylaxis at earlier operative times (OR 5.8, 95% CI 1.8-19.1), whereas those with more than 10 years of experience delayed initiation (OR 8.2, 95% CI 1.8-38.0). Self-reported "guideline-adherent" surgeons were more likely to use mechanical prophylaxis than surgeons who did not report guideline usage. TXA use correlated with chemical thromboprophylaxis usage (OR 8.0, 95% CI 1.8-86.0) and earlier prophylaxis initiation (OR 27.2, 95% CI 2.7-273.1).
Conclusion:
Thromboprophylaxis management is inconsistent in non-free flap breast surgery. Fellowship training, TXA utilization, and guideline usage predicted proactive prophylaxis approaches, whereas more clinical experience predicted conservative behaviors. Prophylaxis consensus is needed to support consistent, evidence-based care.
More Related Videos
Related Concept Videos
 02:16
Surveys
 01:26
National Nursing Organizations I
 01:27
Introduction to Surveying, Plane Surveying and Geodetic Surveys
 01:30
National Nursing Organizations II
The AACN emphasizes a healthy work environment through six standards to achieve an optimal patient outcome. The standards are appropriate staffing, meaningful recognition, collaboration, authentic leadership, effective communication, and decision-making. In addition, AACN provides certification programs, webinars, journals, and...
 01:27
Types of Surveys
 01:28
Survey Safety