Related Experiment Video
Updated: Jan 22, 2026


An Immunohistopathologic Study to Profile the Folate Receptor Beta Macrophage and Vascular Immune Microenvironment in Giant Cell Arteritis
Published on: February 8, 2019
Distinguishing Takayasu Arteritis and Giant Cell Arteritis Based on Large-Vessel Involvement Patterns
Oh Chan Kwon1, Jang Woo Ha2, Min-Chan Park1
1Division of Rheumatology, Department of Internal Medicine, Gangnam Severance Hospital, Yonsei University College of Medicine, Seoul, Korea.

Insights
Takayasu arteritis (TAK) and giant cell arteritis (GCA) large-vessel (LV) involvement patterns can be differentiated. Aortic arch and right subclavian artery involvement are key indicators for distinguishing TAK from GCA.
Area of Science:
- Vascular Inflammation
- Rheumatology
- Diagnostic Imaging
Background:
- Takayasu arteritis (TAK) and extracranial large-vessel (LV) giant cell arteritis (GCA) present overlapping clinical and imaging features.
- Accurate differentiation between TAK and GCA is crucial for appropriate patient management and treatment strategies.
- Identifying distinct LV involvement patterns is essential for improving diagnostic accuracy.
Purpose of the Study:
- To identify specific large-vessel (LV) involvement patterns that can reliably differentiate Takayasu arteritis (TAK) from giant cell arteritis (GCA).
- To evaluate the diagnostic accuracy of identified LV involvement patterns using computed tomography (CT) and positron emission tomography/CT (PET/CT).
Main Methods:
- Retrospective cohort study of 181 patients diagnosed with TAK (n=175) or GCA (n=6).
- Assessment of LV involvement patterns via CT and/or ¹⁸F-fluorodeoxyglucose PET/CT at diagnosis.
- Multivariable logistic regression and receiver operating characteristic (ROC) analysis to determine discriminatory accuracy (Area Under the Curve - AUC).
Main Results:
- Specific arteries like the right subclavian artery, aortic arch, descending aorta, and abdominal aorta were less frequently involved in TAK compared to GCA.
- Hata classification type V and cluster 5 showed lower prevalence in TAK.
- A combination model involving right subclavian artery and aortic arch involvement demonstrated the highest diagnostic accuracy (AUC=0.925).
Conclusions:
- Distinct large-vessel (LV) involvement patterns, particularly involving the aortic arch and right subclavian artery, can accurately differentiate Takayasu arteritis (TAK) from giant cell arteritis (GCA).
- The combined assessment of aortic arch and right subclavian artery involvement offers a highly accurate method for distinguishing between these two vasculitic conditions.
Purpose:
Takayasu arteritis (TAK) and extracranial large-vessel (LV) giant cell arteritis (GCA) share overlapping features, making differential diagnosis between the two diseases challenging. We aimed to identify LV involvement patterns that could accurately differentiate TAK and GCA.
Materials And Methods:
This retrospective cohort study included 181 patients (TAK, n=175; GCA, n=6). LV involvement patterns were assessed using computed tomography (CT) and/or ¹⁸F-fluorodeoxyglucose positron emission tomography/CT performed at diagnosis. A multivariable logistic regression model was used to identify LV involvement patterns that accurately distinguish TAK and GCA. Area under the curve (AUC) was estimated to determine the accuracy.
Results:
The right subclavian artery (30.3% vs. 83.3%, p=0.013), aortic arch (13.7% vs. 83.3%, p<0.001), descending aorta (30.3% vs. 100.0%, p=0.001), and abdominal aorta (30.9% vs. 83.3%, p=0.015) were less commonly involved in TAK than in GCA. When categorized according to Hata's classification and clusters, type V (31.4% vs. 83.3%, p=0.016) and cluster 5 (2.3% vs. 83.3%, p<0.001) were less common in TAK than in GCA. Type V demonstrated an AUC of 0.760, whereas cluster 5 showed higher accuracy (AUC=0.905) in distinguishing TAK and GCA. A combination of right subclavian artery and aortic arch involvement (2.358 × right subclavian artery involvement+3.385 × aortic arch involvement; cut-off=2.872), derived from the multivariable logistic regression model, yielded the highest accuracy (AUC=0.925).
Conclusion:
Distinct patterns of LV involvement, particularly aortic arch involvement, either alone or combined with right subclavian artery involvement, could accurately differentiate TAK and GCA.


Related Concept Videos
 01:26
Antigens Involved in Adaptive Immunity
Complete Antigens
Complete antigens possess both immunogenicity and...
 01:06
Fixed Action Patterns
 01:15
Structure of Blood Vessels
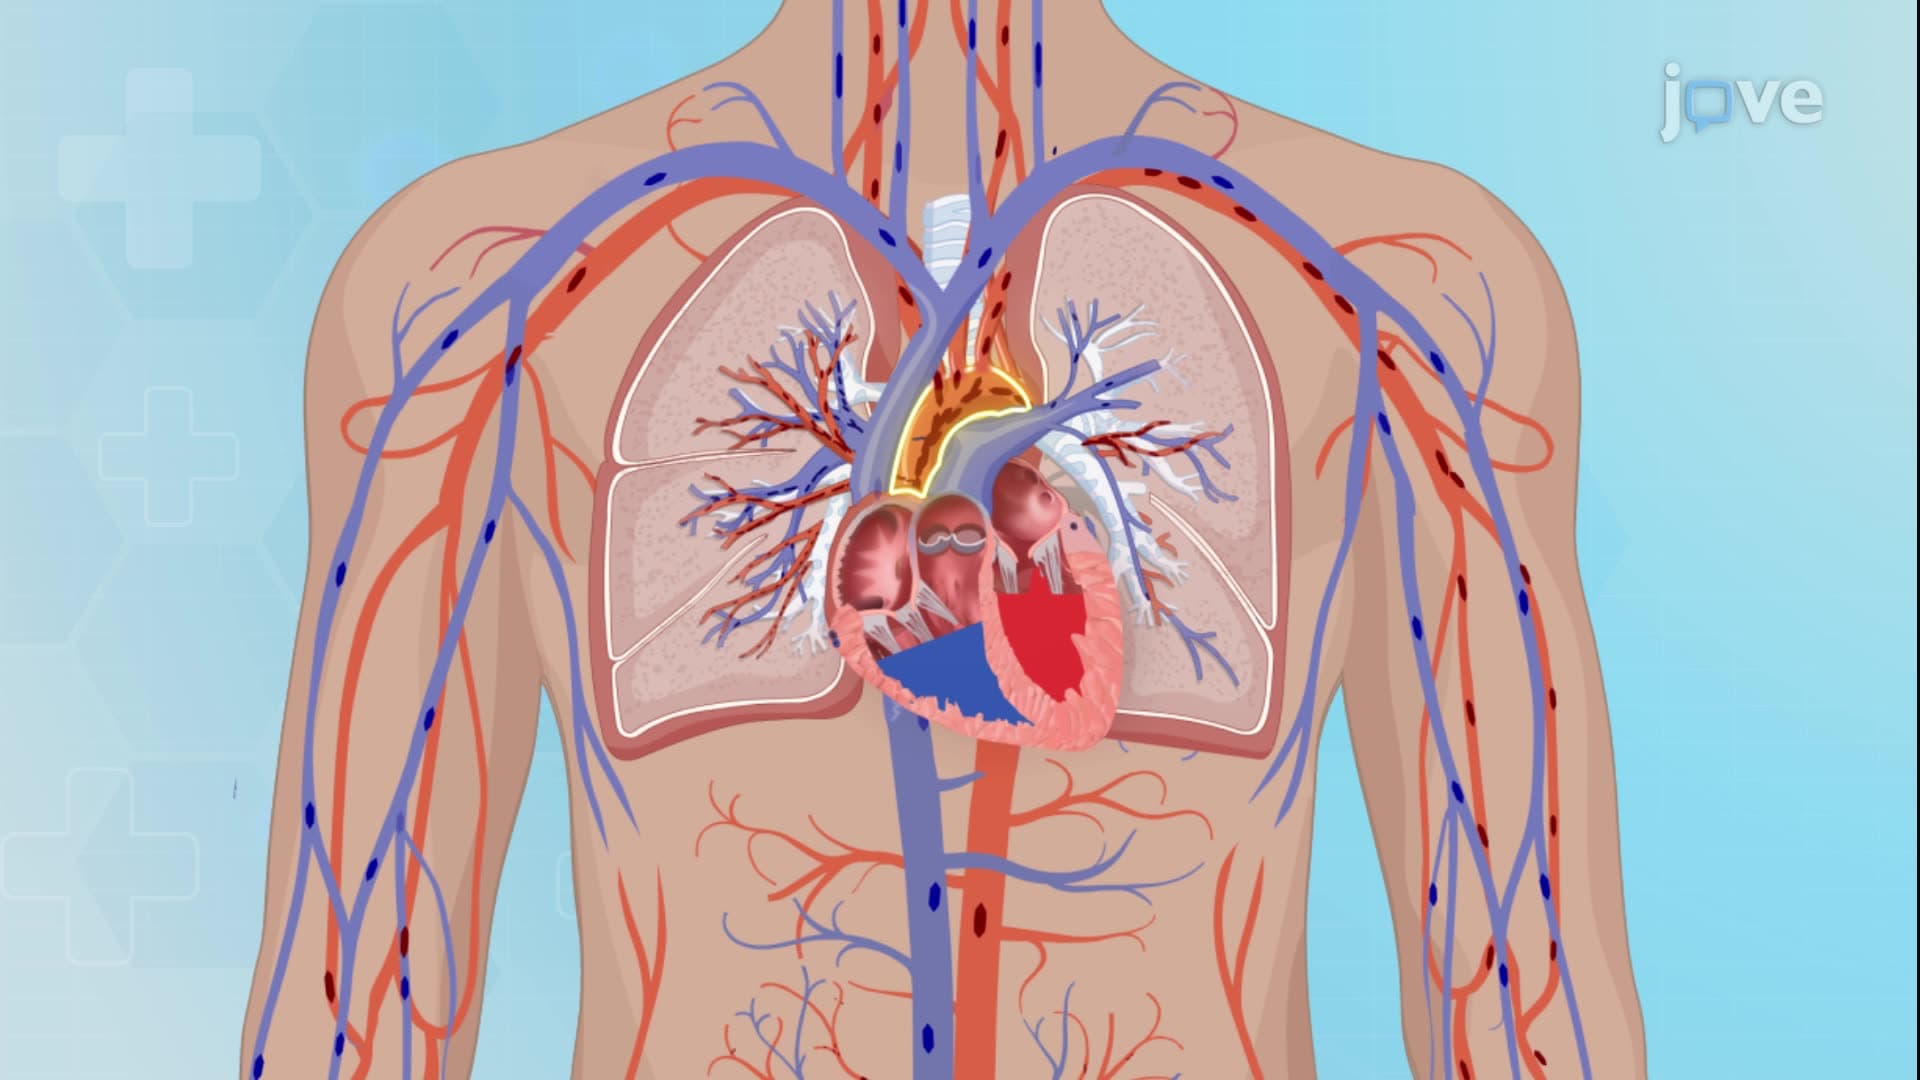 01:20
Anatomy of Blood Vessels
Arteries
Arteries circulate oxygenated blood from the heart, except the pulmonary artery, which transports deoxygenated blood to the lungs. Large arteries, such as the aorta,...
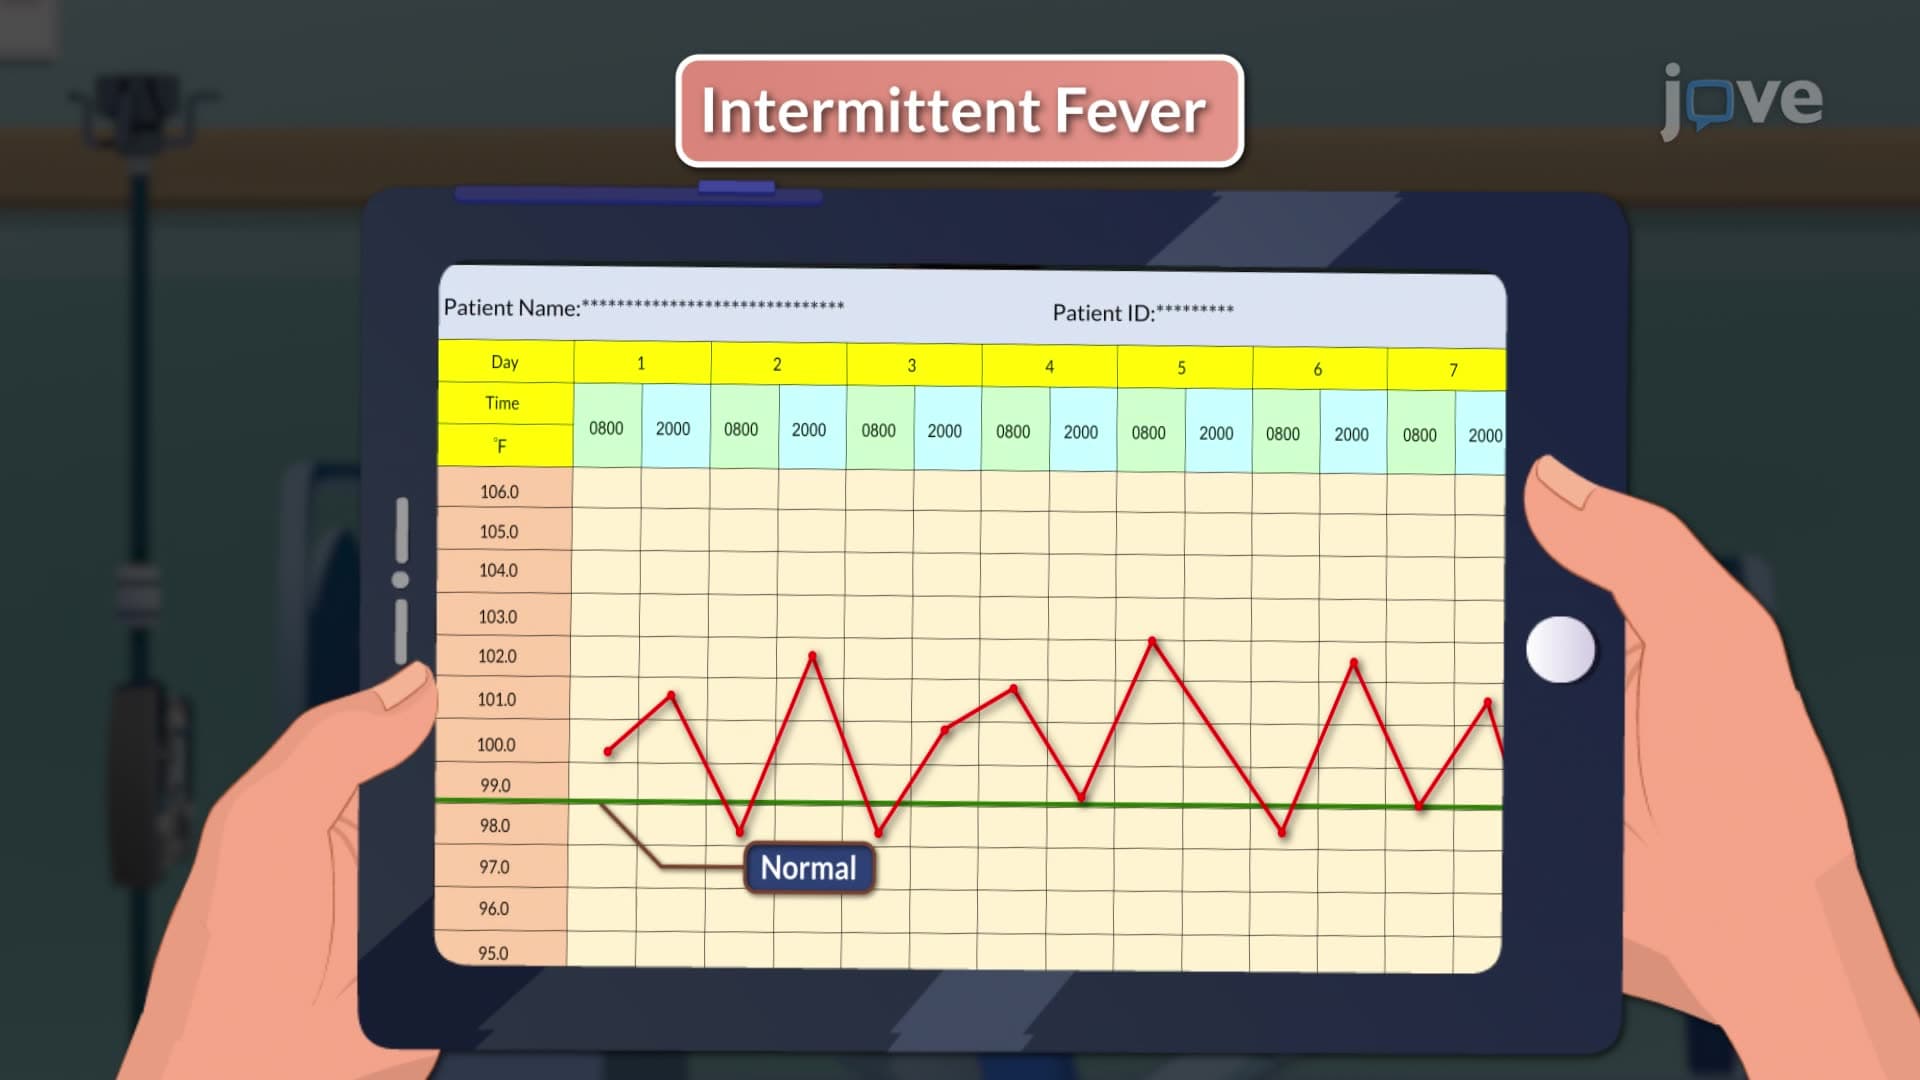 01:26
Patterns of Fever
 01:14
Overview of Blood Vessels
Arteries and Arterioles: Arteries are muscular and elastic vessels that primarily carry oxygenated blood from the heart to body tissues, except for the pulmonary artery, which carries deoxygenated blood. They have thick walls to withstand high pressure and contain a layer of muscle tissue, allowing them to expand or contract as...