Related Experiment Video
Updated: Jan 22, 2026


The Goeckerman Regimen for the Treatment of Moderate to Severe Psoriasis
Published on: July 11, 2013
Triplet regimens for frontline treatment of CLL-Great company or just a crowd?
Sean McKeague1,2, John F Seymour2,3
1Department of Haematology Royal Brisbane & Women's Hospital Herston Queensland Australia.

Abstract:
Standard frontline treatment of chronic lymphocytic leukemia (CLL) is with fixed-duration venetoclax-based doublets or indefinite covalent Bruton tyrosine kinase inhibitor (BTKI). Although these approaches achieve excellent results, venetoclax doublets have diminished efficacy in high-risk biological subgroups, and indefinite covalent Bruton tyrosine kinase inhibitor (cBTKI) is associated with cumulative cardiovascular and infectious toxicity. Triplet regimens for treatment of CLL involve simultaneous use of cBTKI, venetoclax, and anti-CD20 monoclonal antibody. Three major frontline Phase 3 trials (CLL-13/GAIA, AMPLIFY, and A041702) have demonstrated higher rates of undetectable minimal residual disease (uMRD) and longer remissions with triplets than doublets, particularly in patients with IGHV-unmutated (IGHV-U) disease. However, this comes at the cost of increased infectious toxicity, particularly with COVID-19, and thus has translated into a variable impact on progression-free survival (PFS) and, to-date, no overall survival (OS) benefit. Although there are promising Phase 2 data for triplets in patients with TP53 aberrant or relapsed disease, the heterogeneity of treatment duration/MRD definition, lack of control arm, and potential increased toxicity make it premature to use triplets in these groups. We recommend considering triplets in treatment naïve CLL patients with IGHV-U, TP53 wild type, anticipated low incidence/good tolerance of Gr ≥ 3 infection (<70 years old, no major comorbidity and fully immunized) who are well informed and prioritize maximal time off therapy at the expense of increased short-term logistical complexity. Future triplet research should focus on randomized trials in specific genomic subgroups, incorporating novel agents (e.g., non-covalent BTKI, BTK degrader, and next-generation BCL2 inhibitors) and new ways of adapting treatment duration to maximize efficacy and minimize toxicity.
More Related Videos


Related Concept Videos
 01:15
Drug Dosage Regimen: Overview
Typically, the starting dose and dosing interval are guided by the manufacturer's recommendations based on clinical trials conducted during and after drug...
 01:24
Dosage Regimen: Individualization
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:25
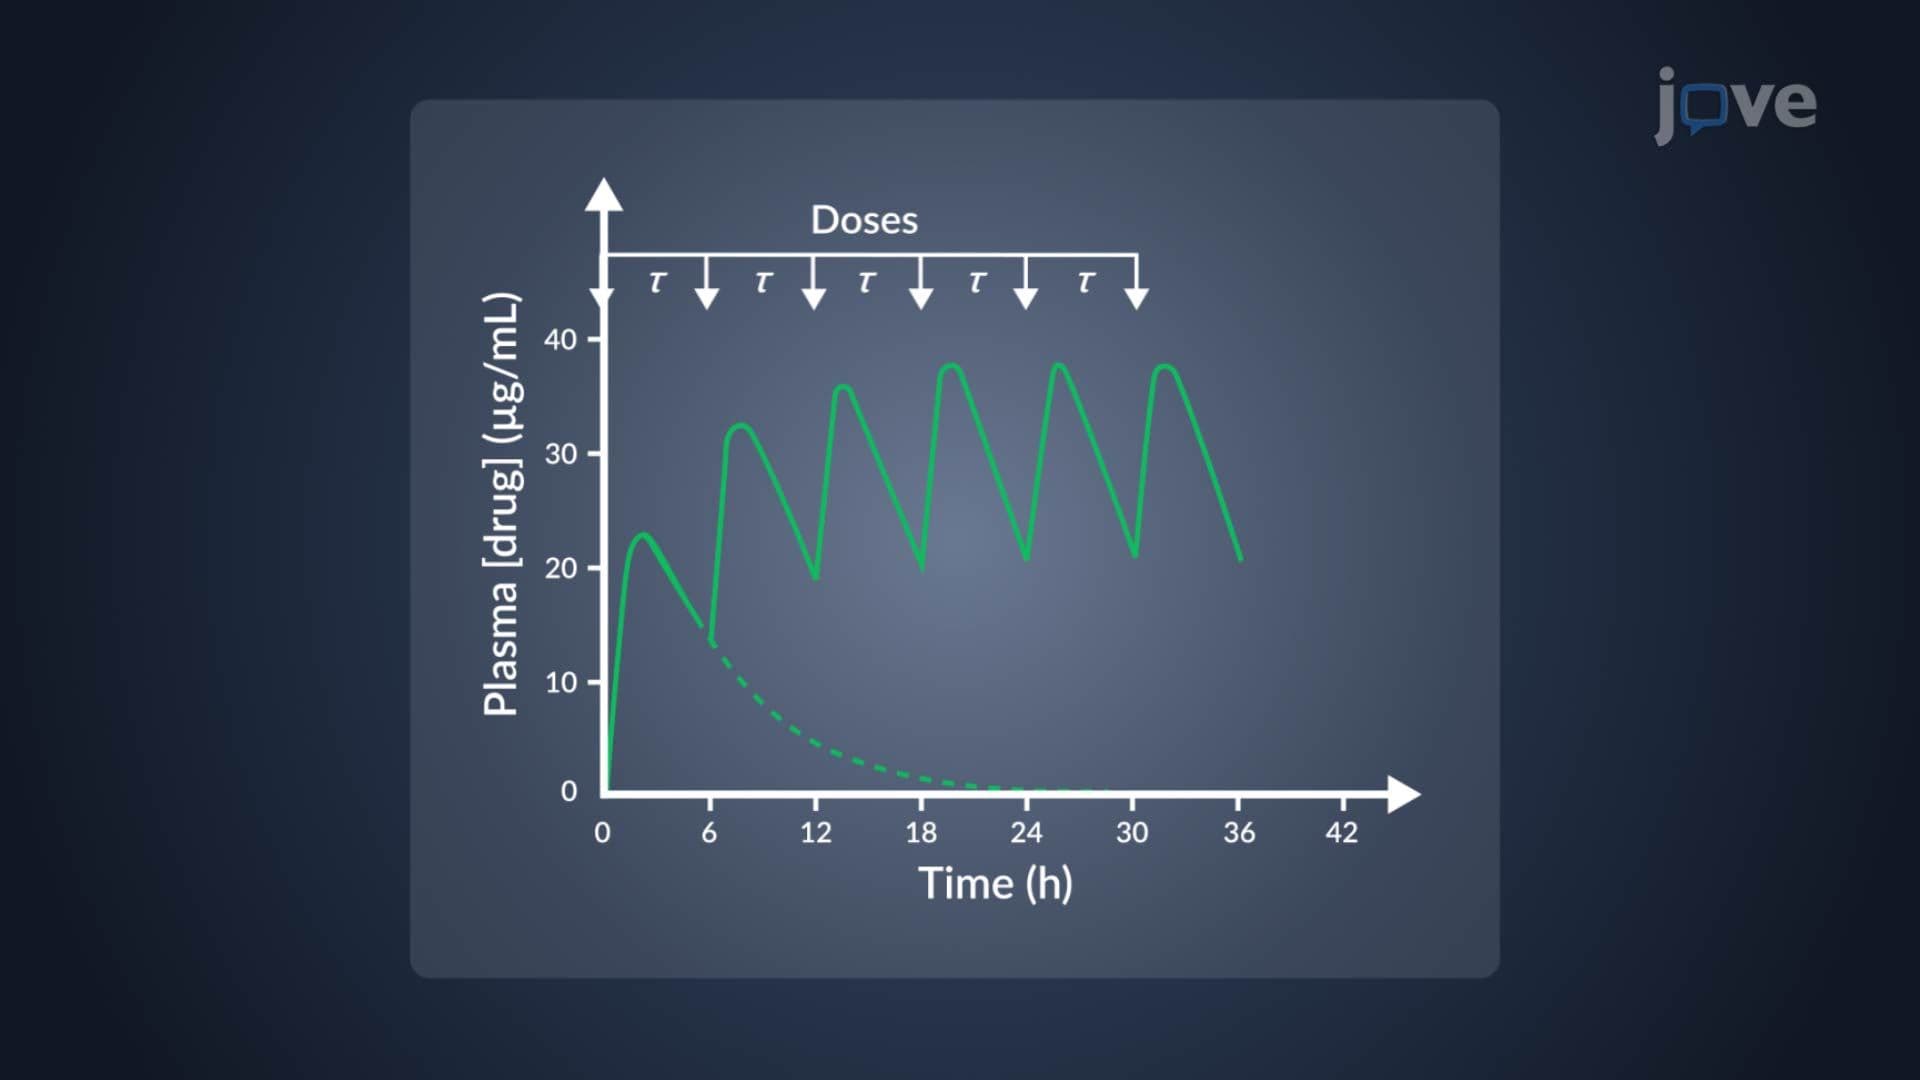
Dosage Regimen: Multiple Oral Dosage
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:28
Dosage Regimens: Designs and Approaches