Related Experiment Video
Updated: Jan 22, 2026


In vitro Assessment of Cardiac Reprogramming by Measuring Cardiac Specific Calcium Flux with a GCaMP3 Reporter
Published on: February 22, 2022
Heart in the crossfire, from epsilon to beyond: cardiac sarcoidosis-a case report
Humaid Ali1,2, Hamat Hamdi Che Hassan1,2, Mohd Shawal Faizal Mohamad1,2
1Faculty of Medicine, Universiti Kebangsaan Malaysia, Jalan Yaacob Latif, Bandar Tun Razak, Cheras, Kuala Lumpur 56000, Malaysia.

Background:
Sarcoidosis is a great mimicker of various medical conditions, which leads to obstacles in early diagnosis and appropriate timely management.
Case Summary:
A 66-year-old Indian female with metabolic syndrome was initially treated for decompensated liver disease. Her baseline electrocardiogram showed right bundle branch block with a first-degree heart block. She presented 3 months later with angina and heart failure (HF) symptoms, complicated with ventricular tachycardia (VT) treated with i.v. amiodarone and anti-failure medication. Her coronary angiogram revealed mild disease, and her echocardiography showed a mildly reduced ejection fraction (EF) of 45% with regional wall motion abnormalities. Cardiac magnetic resonance imaging (CMR) revealed non-specific left ventricular (LV) patchy mid-wall to epicardial late gadolinium enhancement. Endomyocardial biopsy was complicated with cardiac tamponade and required pericardiocentesis followed by dual-chamber implantable cardioverter-defibrillator (ICD) later. Unfortunately, biopsy result was inconclusive, and serum angiotensin-converting enzyme was within the normal range. She had multiple admissions for the past 2 years for recurrent VT and decompensated HF despite the optimization of ICD setting and guideline-directed medical therapy. Repeated echocardiogram revealed similar EF with thinning of the LV basal septal segment. Her positron emission tomography (PET) scan (Tc-99 m) showed diffuse uptake at the LV myocardium and supraclavicular/mediastinal/abdominopelvic lymph nodes with a mismatch of fluorodeoxyglucose uptake at the basal-inferolateral segment (non-specific). Lymph node biopsy revealed chronic non-caseating granulomatous inflammation. Clinical diagnosis of cardiac sarcoidosis was made based on a histologic diagnosis of extracardiac sarcoidosis with cardiomyopathy/ventricular arrhythmia combined with PET/CMR findings.
Discussion:
Cardiac sarcoidosis can have a myriad of symptoms, which may mimic several other disorders leading to a diagnostic challenge.
More Related Videos


Related Concept Videos
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...
 01:19
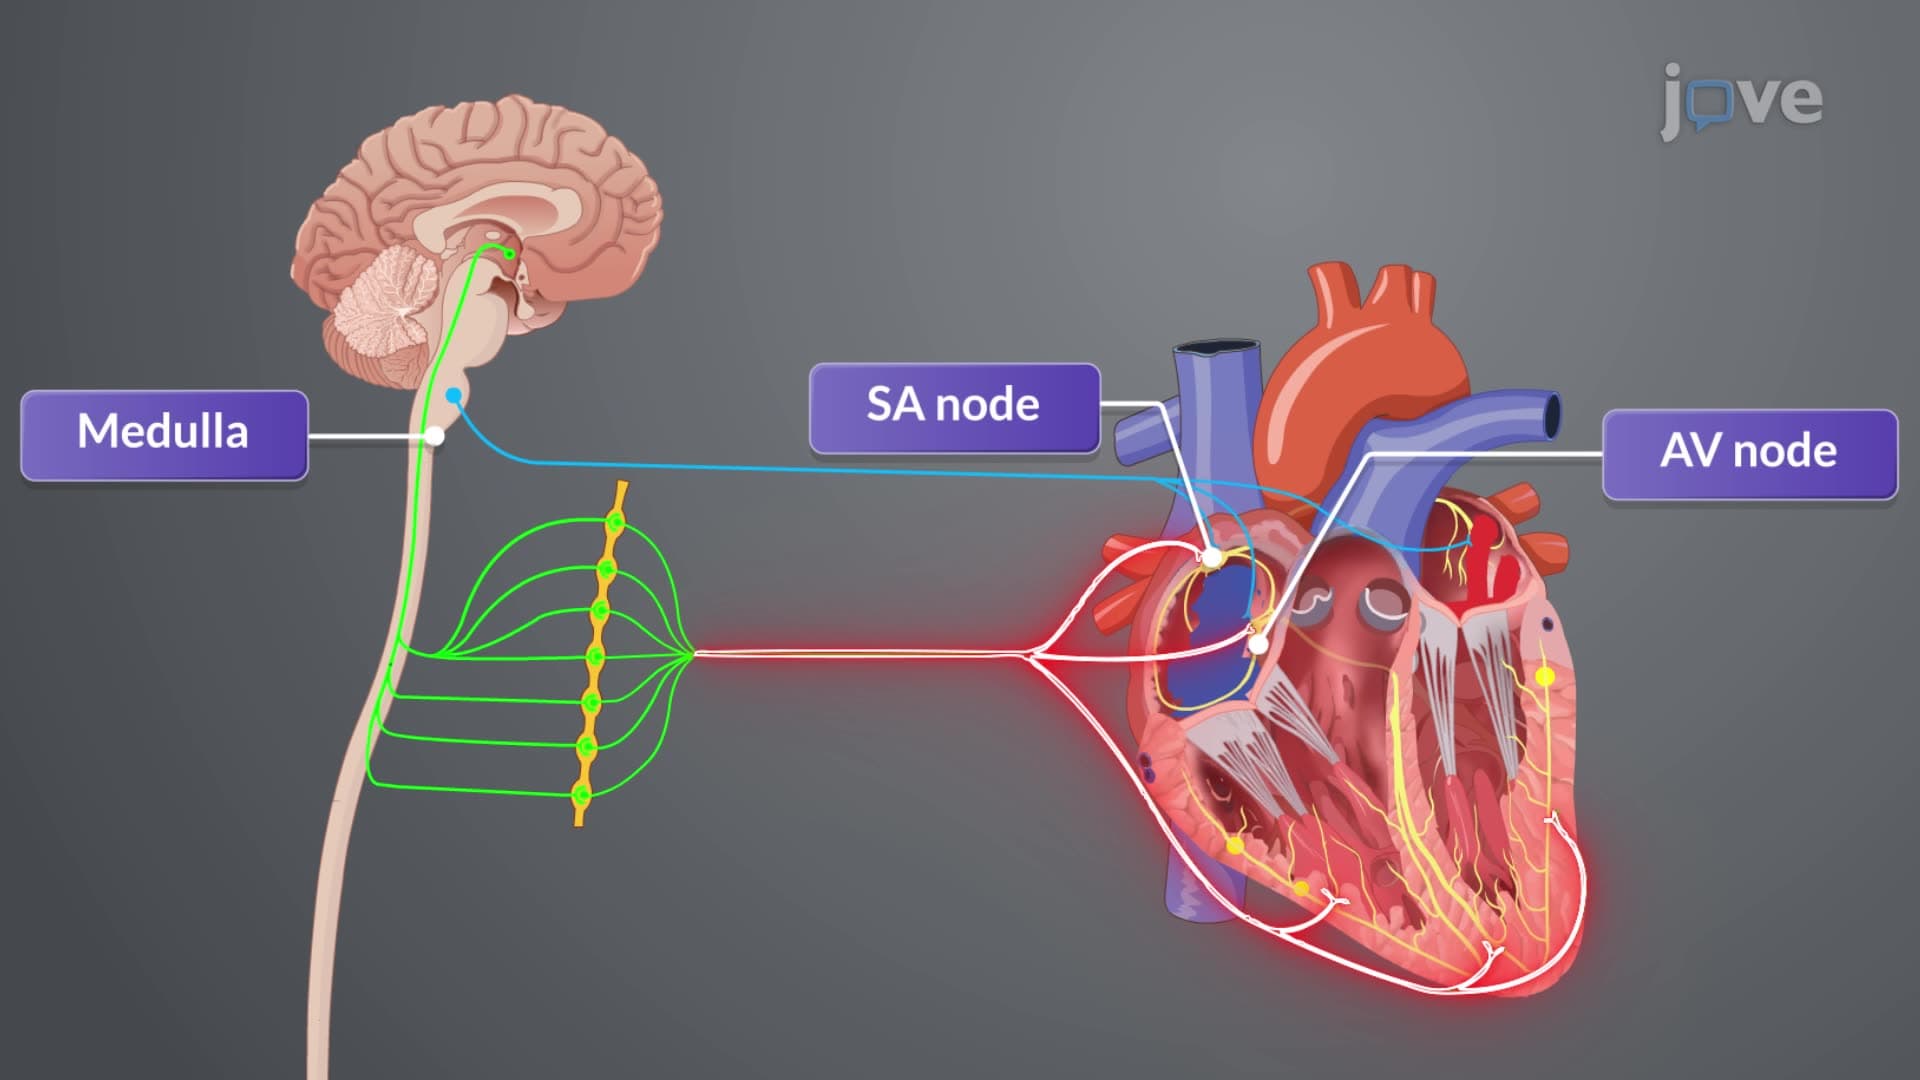
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:27
Anatomy of the Heart
 01:24
Data Reporting and Recording