Related Experiment Video
Updated: Jan 23, 2026
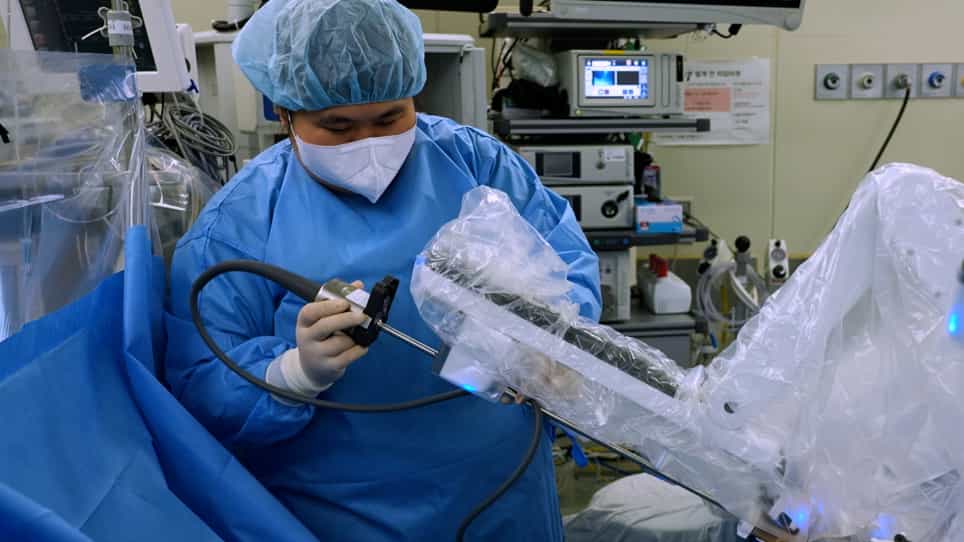

Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Utilization of dd-cfDNA Monitoring to Facilitate Immunosuppression Minimization After Kidney Transplantation in a
Laura Cotiguala1, Anne Przybylski1, Cara Joyce1,2
1Edward Hines Jr. VA Hospital, Hines, Illinois, USA.

Background:
Although donor-derived cell-free DNA (dd-cfDNA) serves as a monitoring tool for rejection, few studies have examined its utility in guiding immunosuppression management. Here, we present the largest kidney transplant population in which immunosuppression minimization and subsequent surveillance were guided by dd-cfDNA.
Methods:
This retrospective case series evaluated our immunosuppression minimization practice to tacrolimus and prednisone in kidney transplant recipients (KTR) from November 20, 2020, to September 26, 2024. Baseline dd-cfDNA ≤ 0.5% was required before minimization. Immune tolerance was defined by the absence of any immune event after minimization: absolute dd-cfDNA > 0.5%, relative change value (RCV) > 60% from baseline, biopsy-proven acute rejection (BPAR), or de novo donor-specific antibody (DSA). All other KTR were labeled intolerant. The primary endpoint was the rate of immune tolerance.
Results:
Immunosuppression was modified to tacrolimus and prednisone in 38 KTR at a median of 223 days post-transplant. Most KTR were older adults at low immunological risk: mean of 69 years and all had a calculated panel reactive antibody of 0%. 21 (55.3%) KTR met the primary end point of tolerance. The remaining 17 KTR were labeled intolerant secondary to dd-cfDNA elevations including absolute > 0.5% or RCV > 60% (n = 16 of 17, 94%), de novo DSA (n = 2 of 17, 11.8%), and/or BPAR (n = 4 of 17, 23.5%). Although not statistically significant, intolerant KTR were numerically more likely to have 5-6 HLA mismatches (82.5% vs. 52.4%, p = 0.31), less likely to have thymoglobulin induction (29.4% vs. 42.9%, p = 0.39), and were minimized earlier after transplant (196 vs. 256 days, p = 0.08) compared with tolerant KTR, respectively. Intervention after dd-cfDNA elevations included immunosuppression increase (50%), additional dd-cfDNA monitoring (81.3%), DSA testing (50%), and allograft biopsy (18.7%).
Conclusion:
Approximately 50% of low immunological risk KTR with a baseline dd-cfDNA < 0.5% tolerated immunosuppression minimization to tacrolimus and prednisone without concerning dd-cfDNA elevations, BPAR, or DSA. Our study highlights the role of dd-cfDNA as part of the armamentarium for identifying minimization candidates and performing subsequent surveillance.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:19
Facilitated Transport
 01:04
Social Facilitation
 02:04
Conservation of Small Populations