Related Experiment Video
Updated: Jan 23, 2026


Coronary Progenitor Cells and Soluble Biomarkers in Cardiovascular Prognosis after Coronary Angioplasty
Published on: January 28, 2020
Risk-weighted apoB: a novel summary metric outperforming traditional lipid biomarkers in predicting coronary heart
Michaela B Rehman1, Elias Björnson2, Martin Adiels2
1Cardiology Department, Ramsay Santé, Médipôle Lyon-Villeurbanne, Villeurbanne, France.

Insights
A new metric, risk-weighted apolipoprotein B (RW-apoB), improves coronary heart disease (CHD) risk prediction by accounting for triglyceride-rich lipoproteins (TRL) and lipoprotein(a) [Lp(a)]. This advanced measure offers better risk stratification than traditional apoB alone.
Area of Science:
- Cardiovascular Medicine
- Lipid Metabolism
- Biomarkers
Background:
- Standard lipid markers like LDL-C and non-HDL-C do not fully assess coronary heart disease (CHD) risk from all atherogenic lipoproteins.
- Apolipoprotein B (apoB) indicates total atherogenic particle number but may underestimate risk when triglyceride-rich lipoproteins (TRL/remnants) and lipoprotein(a) [Lp(a)] are high.
Purpose of the Study:
- To develop a novel metric, risk-weighted apoB (RW-apoB), to integrate risk from LDL, TRL/remnants, and Lp(a) into a single value.
- To enhance the accuracy of cardiovascular risk prediction beyond current apoB measurements.
Main Methods:
- The RW-apoB metric was formulated using UK Biobank data based on established relative atherogenicity estimates.
- The formula is: RW-apoB = 11.65×TG(mmol/L) + 0.215×lipoprotein(a)(nmol/L) + 0.736×apoB(mg/dL).
Main Results:
- RW-apoB significantly reclassified individuals' CHD risk status compared to measured apoB, with 52% changing rank by ≥10 percentiles.
- Individuals in the top RW-apoB quintile with elevated TRL and Lp(a) showed a 5.4% CHD event rate, often misclassified as lower risk by apoB alone.
- RW-apoB demonstrated superior risk prediction, significantly improving Harrell's C-index (P < .0001) and outperforming apoB in Cox models across multiple cohorts.
Conclusions:
- RW-apoB accounts for both atherogenic particle number and the increased atherogenicity of TRL and Lp(a).
- This new metric offers clinically significant improvements in CHD risk stratification, particularly for residual risk in statin-treated patients.
Background And Aims:
LDL-C and non-HDL-C do not fully capture coronary heart disease (CHD) risk attributed to all apoB-containing lipoproteins. Use of apolipoprotein B (apoB) as a marker of total atherogenic particle number improves risk prediction, but risk may still be underestimated when triglyceride-rich lipoproteins (TRL/remnants) and lipoprotein(a) [Lp(a)] are elevated. The aim was to formulate a new metric-risk-weighted apoB (RW-apoB)-designed to capture risk from LDL, TRL/remnants, and Lp(a) in a single number.
Methods:
Based on previously published estimates of the relative atherogenicity of LDL, TRL/remnant, and Lp(a) particles, RW-apoB was developed (using UK Biobank data) as an atherogenicity-weighted apoB-sum calculated as: RW-apoB = 11.65×TG(mmol/L) + 0.215×lipoprotein(a)(nmol/L) + 0.736×apoB(mg/dL).
Results:
Assigning RW-apoB to individuals substantially reclassified their risk status. Compared with ranking by measured apoB, 52% of individuals were up- or down-ranked by ≥10 percentiles. About one-third of those in the top RW-apoB quintile-with elevated TRL and Lp(a) and a CHD event rate of 5.4%-were misclassified as lower risk by apoB. Conversely, individuals in the top measured apoB quintile but with low TRL and Lp(a) had a lower event rate (3.9%) and were correctly down-ranked. RW-apoB improved risk prediction, significantly increasing Harrell's C-index relative to apoB (P < .0001). In statin-treated subjects, RW-apoB was potentially a better index of residual risk. RW-apoB consistently outperformed apoB as a risk predictor in Cox models across the UK Biobank and three other large population cohorts.
Conclusions:
RW-apoB represents not only particle number but also accounts for the higher atherogenicity of TRL and Lp(a). It offers clinically meaningful improvements in CHD risk stratification.
Related Concept Videos
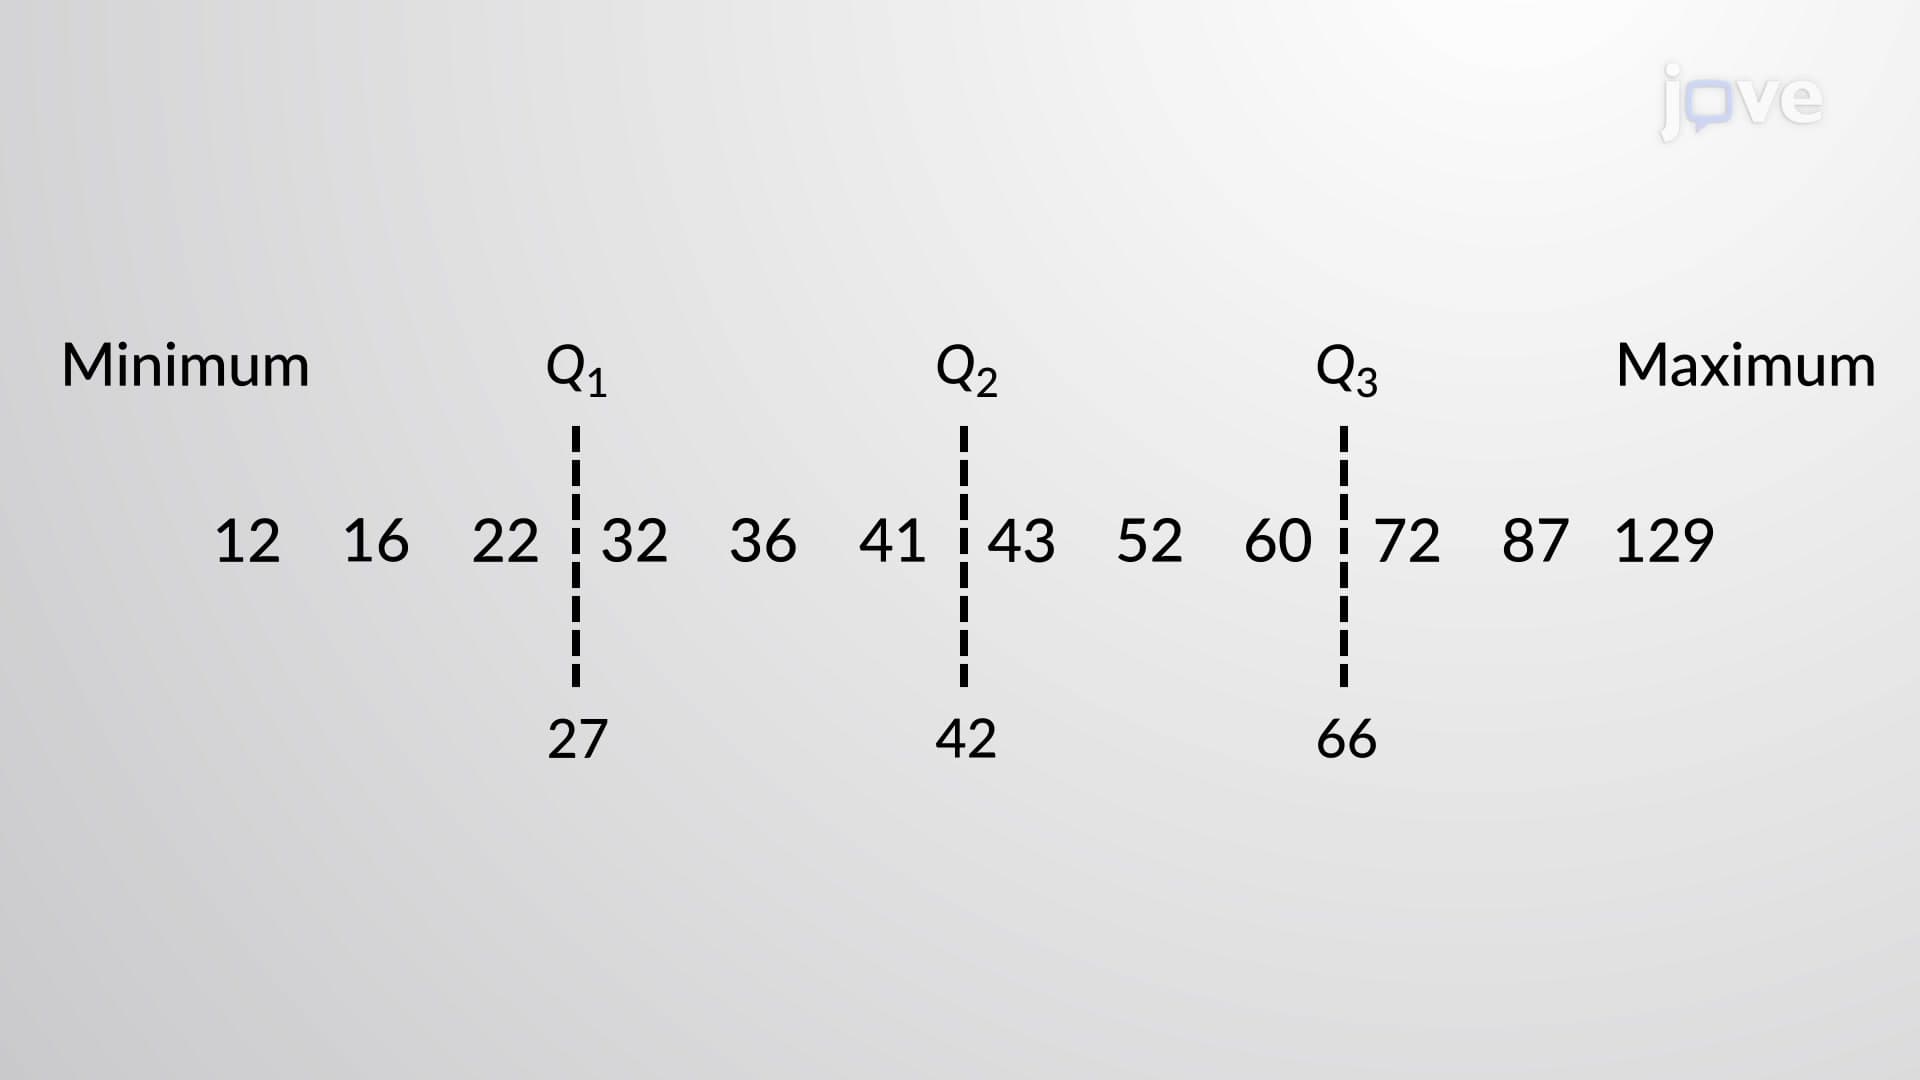 01:04
5-Number Summary
In a box plot, the minimum and maximum data values represent the lower and upper whiskers in the graph, and the median is designated as the center of the box in the chart. The first quartile and third...
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:23
Rheumatic Heart Disease I: Introduction