Related Experiment Video
Updated: Jan 24, 2026


A General Method for Evaluating Deep Brain Stimulation Effects on Intravenous Methamphetamine Self-Administration
Published on: January 22, 2016
Four-lead deep brain stimulation for multifocal drug-resistant epilepsy: surgical safety profile and preliminary
Pierce A Peters1, Roy Zhou2, Raunak Singh3
1Departments of1Neurologic Surgery.

Objective:
Deep brain stimulation (DBS) is emerging as an additional surgical option for refractory, multifocal epilepsy. Four-lead DBS systems can be used when seizure onset is poorly localized, generalized, or involves multiple targetable circuits. The goal of this study was to assess preliminary outcomes and complication rates in 4-lead DBS systems for treating epilepsy.
Methods:
A consecutive series of 32 patients with 4-lead DBS implants who had at least 6 months of follow-up was reviewed, and demographics, outcomes, and complications were abstracted.
Results:
Thirty-two patients implanted with 4 DBS leads (including off-label use) were included. The median age at surgery was 28.5 years, the median age at epilepsy diagnosis was 7.5 years, and 18 patients (56%) were women. The median epilepsy duration prior to implantation was 21 years. The most common seizure localization was frontotemporal (53%), followed by generalized (28%) and parietoccipital (13%). Prior vagus nerve stimulation had been trialed in 20 patients (63%), and an invasive stereotactic EEG recording was performed in 17 patients (59%). Eight patients had prior epilepsy surgery (25%). DBS targets included the anterior thalamic nucleus in combination with the centromedian thalamic nucleus, hippocampus, pulvinar nucleus, cingulate, insula, and globus pallidus. The median surgical duration was 5 hours 22 minutes, with a median operating room time of 8 hours 21 minutes. The median postoperative follow-up was 27 (interquartile range 17-41) months. Three patients experienced transient neurological deficits and 2 patients required intraoperative lead repositioning. There were no infections or hemorrhages. Most patients benefited from stimulation (22% Engel class I, 22% class II, 28% class III, and 28% class IV). The median patient-reported seizure reduction rate was 70%, with a responder rate of 72%. One patient elected to have the system explanted.
Conclusions:
Four-lead DBS is safe and can achieve meaningful improvement in challenging cases of multifocal epilepsy with a low complication rate.
More Related Videos
 09:57
Author Spotlight: Advancing Pediatric Epilepsy Surgery in Children Through Novel Biomarkers and Enhanced Localization
Published on: September 20, 2024
 08:23
A Multimodal Imaging- and Stimulation-based Method of Evaluating Connectivity-related Brain Excitability in Patients with Epilepsy
Published on: November 13, 2016
Related Concept Videos
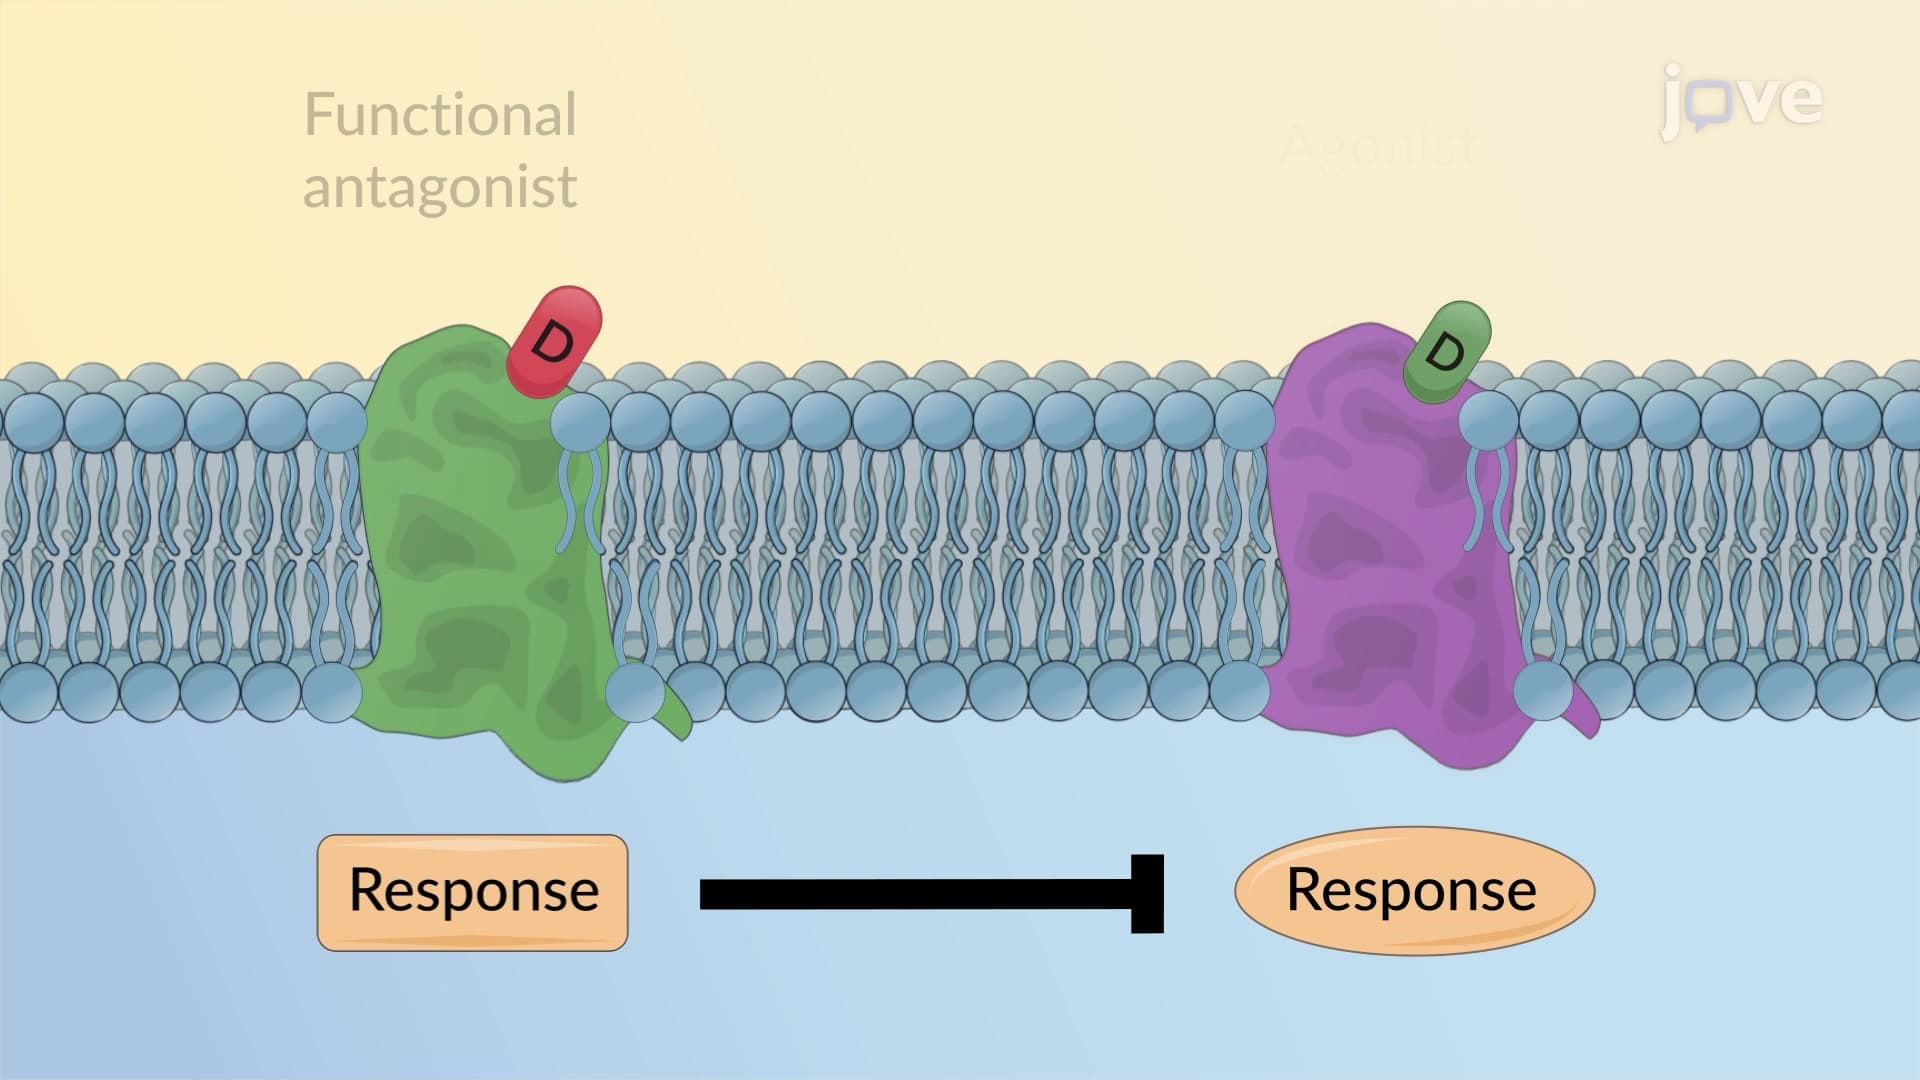 01:30
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...
 01:21
Antipsychotic Drugs: Therapeutic Uses and Side Effects
Despite these side effects, antipsychotics are used therapeutically for various purposes, including managing schizophrenia, preventing nausea and vomiting, curbing...
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:14
Drug Dissolution: Requirements and Profile Comparison
 01:28
Survey Safety
 01:23
Drugs Acting on Autonomic Ganglia: Stimulants
Ganglionic stimulants activate NM nicotinic receptors in autonomic ganglia, falling into two categories: nicotine mimetics [e.g., lobeline, dimethylpiperazine, tetramethylammonium] and muscarinic receptor agonists [e.g., muscarine, methacholine]. The first category's action is rapid and blocked by nicotinic receptor antagonists, while the second category's action is delayed and blocked by atropine-like agents. Nicotine, an alkaloid, affects the heart rate by stimulating...