Related Experiment Video
Updated: Jan 24, 2026
Isolation Method for Long-Term and Short-Term Hematopoietic Stem Cells
Published on: May 19, 2023
Long-Term Survival Gains after Allogeneic Hematopoietic Stem Cell Transplant are Driven by Reductions in Non-Relapse
Alia Cibich1, Gauri Wechalekar1, Naranie Shanmuganathan2
1Haematology Department, Royal Adelaide Hospital, Adelaide, South Australia, Australia; Adelaide Medical School, University of Adelaide, Adelaide, South Australia, Australia.

Allogeneic hematopoietic stem cell transplant (alloHSCT) has evolved substantially in recent decades, expanding patient access via widespread adoption of increased age limits, alternate mismatched donors, reduced intensity conditioning, and novel graft-versus-host disease (GVHD) prophylaxis strategies. However, real-world outcomes reflective of these changes remain underreported. We performed a retrospective population-based analysis of all consecutive adult alloHSCT within South Australia from 1990 to 2023 (N = 864). Patients were grouped by decade to evaluate temporal changes in practice and outcomes. Median age at transplant increased from 41 yr in the 1990s to 54 yr in the 2020s, with patients aged ≥60 yr now comprising >40% of recipients. Donor utilization shifted markedly, with matched related donors declining (90% to 25%) in favor of matched unrelated (10% to 51%) and haploidentical donors (0% to 16%). Conditioning intensity transitioned from predominantly myeloablative (68% to 21%) to reduced intensity regimens (32% to 71%). Despite treating an older and more comorbid population, outcomes improved steadily: 3-yr overall survival increased from 41% in the 1990s to 58% in the 2020s (P = .0005), progression-free survival from 37% to 49% (P = .01), and non-relapse mortality (NRM) declined from 55% to 25% (P < .0001). Relapse rates remained static at approximately 26% to 31% since 2000, with disease status at transplant the strongest predictor of recurrence. GVHD incidence peaked in the 2010s but declined in the 2020s, coinciding with wider adoption of post-transplant cyclophosphamide. In conclusion, alloHSCT outcomes have improved markedly over 35 yr, with survival gains predominantly driven by reductions in NRM. Relapse remains the dominant barrier to cure, underscoring the need for novel strategies to augment disease control.
Allogeneic hematopoietic stem cell transplant (alloHSCT) has evolved substantially in recent decades, expanding patient access via widespread adoption of increased age limits, alternate mismatched donors, reduced intensity conditioning, and novel graft-versus-host disease (GVHD) prophylaxis strategies. However, real-world outcomes reflective of these changes remain underreported. We performed a retrospective population-based analysis of all consecutive adult alloHSCT within South Australia from 1990 to 2023 (N = 864). Patients were grouped by decade to evaluate temporal changes in practice and outcomes. Median age at transplant increased from 41 yr in the 1990s to 54 yr in the 2020s, with patients aged ≥60 yr now comprising >40% of recipients. Donor utilization shifted markedly, with matched related donors declining (90% to 25%) in favor of matched unrelated (10% to 51%) and haploidentical donors (0% to 16%). Conditioning intensity transitioned from predominantly myeloablative (68% to 21%) to reduced intensity regimens (32% to 71%). Despite treating an older and more comorbid population, outcomes improved steadily: 3-yr overall survival increased from 41% in the 1990s to 58% in the 2020s (P = .0005), progression-free survival from 37% to 49% (P = .01), and non-relapse mortality (NRM) declined from 55% to 25% (P < .0001). Relapse rates remained static at approximately 26% to 31% since 2000, with disease status at transplant the strongest predictor of recurrence. GVHD incidence peaked in the 2010s but declined in the 2020s, coinciding with wider adoption of post-transplant cyclophosphamide. In conclusion, alloHSCT outcomes have improved markedly over 35 yr, with survival gains predominantly driven by reductions in NRM. Relapse remains the dominant barrier to cure, underscoring the need for novel strategies to augment disease control.
Related Concept Videos
 01:19
Multipotency of Hematopoietic Stem Cells
 01:01
Regulation of Hematopoietic Stem Cells
 03:11
Oxidation-Reduction Reactions
 01:15
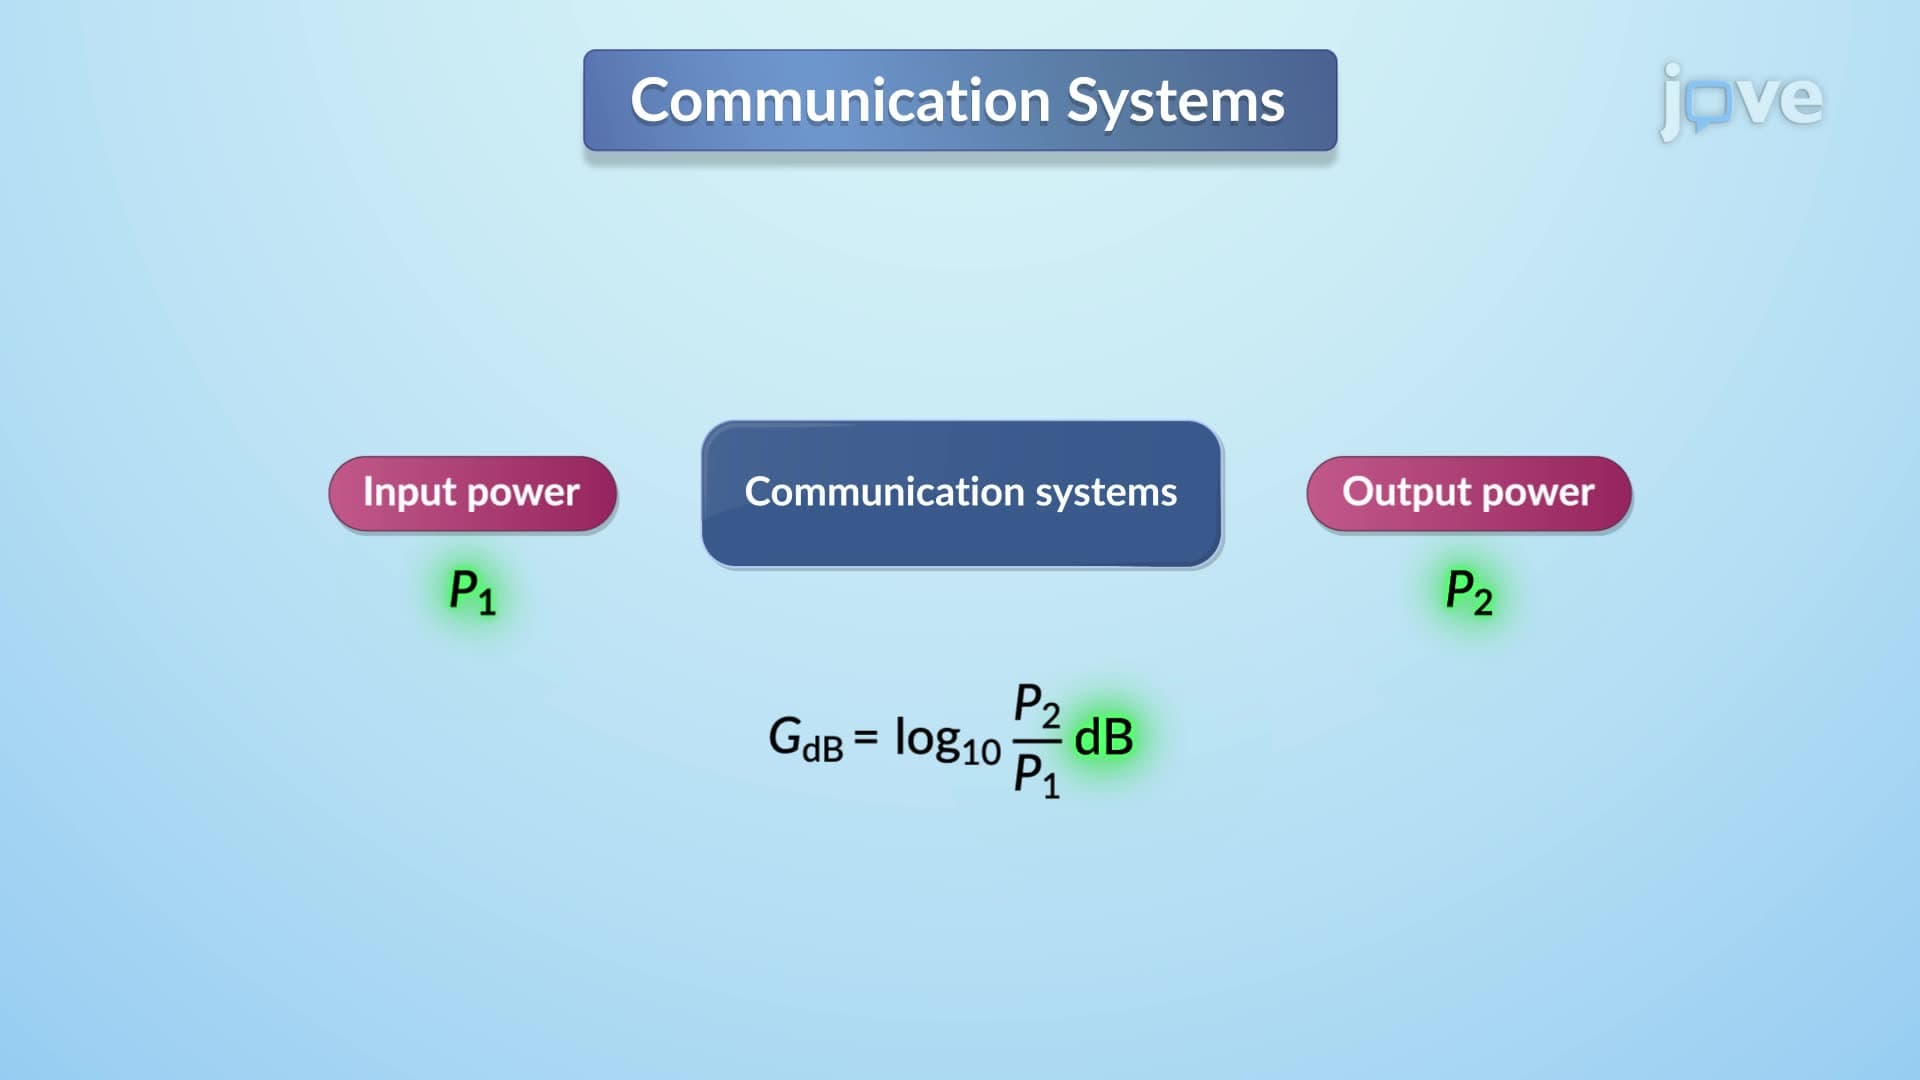
Gain
Gain:
Suppose Vin is the input and Vout is the output signal to a circuit.
 01:13
Induced Pluripotent Stem Cells
 01:33
Adult Stem Cells