Related Experiment Video
Updated: Jan 27, 2026
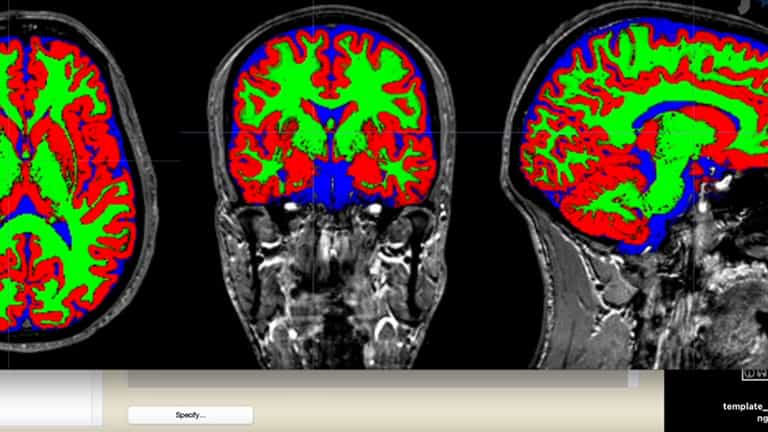

Brain Morphology of Cannabis Users With or Without Psychosis: A Pilot MRI Study
Published on: August 18, 2020
Optimizing antipsychotic dosing for relapse prevention in cannabis-induced psychosis: A nationwide cohort study
Antti Mustonen1, Solja Niemelä2, Alexander Denissoff2
1Faculty of Medicine and Health Technology, Tampere University, Tampere, Finland; Department of Clinical Neuroscience, Karolinska Institutet, Stockholm, Sweden; Department of Psychiatry, Seinäjoki Central Hospital, Seinäjoki, Finland.

Background:
Cannabis-induced psychosis (CIP) carries a high risk of relapse. Research has shown that antipsychotic medications are effective in relapse prevention after first diagnosed CIP. Given that antipsychotics carry the potential for dose-related adverse effects, understanding the optimal dose is critical. Therefore, we conducted a dose-response analysis to evaluate the real-world effectiveness of oral antipsychotics in preventing relapse after CIP.
Methods:
We used data from linkage of administrative and health care registers from Sweden to identify all individuals with first diagnosis of CIP (ICD-10 F12.5). We modelled oral antipsychotic exposure (aripiprazole, clozapine, risperidone, olanzapine, quetiapine, antipsychotic polytherapy, other oral antipsychotics) as time-dependent using validated PRE2DUP-method. Dose-response association of antipsychotic exposure and outcome were examined across three predefined daily dose (DDD) categories (<0.6, 0.6-<1.4, ≥1.4) using within-individual models in a stratified Cox-regression analysis. The primary outcome was hospitalization for any psychotic episode, defined as schizophrenia-spectrum disorder (F20-F29) or substance-induced psychosis (F1x.5) as the main diagnosis.
Results:
We identified 1,772 individuals aged 16-64 years with first-time CIP between 2006 and 2021. Antipsychotic polytherapy was associated with reduced risk of psychosis hospitalization across all dose ranges (HRs=0.54-0.65). Clozapine (0.6-<1.4 DDDs/day), olanzapine (≥0.6 DDDs/day), aripiprazole (0.6-<1.4 DDDs/day), risperidone (<0.6 DDDs/day), and other oral antipsychotics (0.6-<1.4 DDDs/day) were effective, while quetiapine showed no significant benefit.
Conclusions:
Findings indicate dose-dependent real-world effectiveness of antipsychotics in CIP, with most agents performing best at 0.6-<1.4 DDDs/day. These results support optimizing dosing of oral antipsychotic medications for relapse prevention after CIP to balance efficacy and adverse effects.


Related Concept Videos
 01:28
Psychosis and Antipsychotic Drugs: Overview
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 01:26
Psychosis: Goals of Pharmacotherapy
 01:21
Antipsychotic Drugs: Therapeutic Uses and Side Effects
Despite these side effects, antipsychotics are used therapeutically for various purposes, including managing schizophrenia, preventing nausea and vomiting, curbing...
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:21
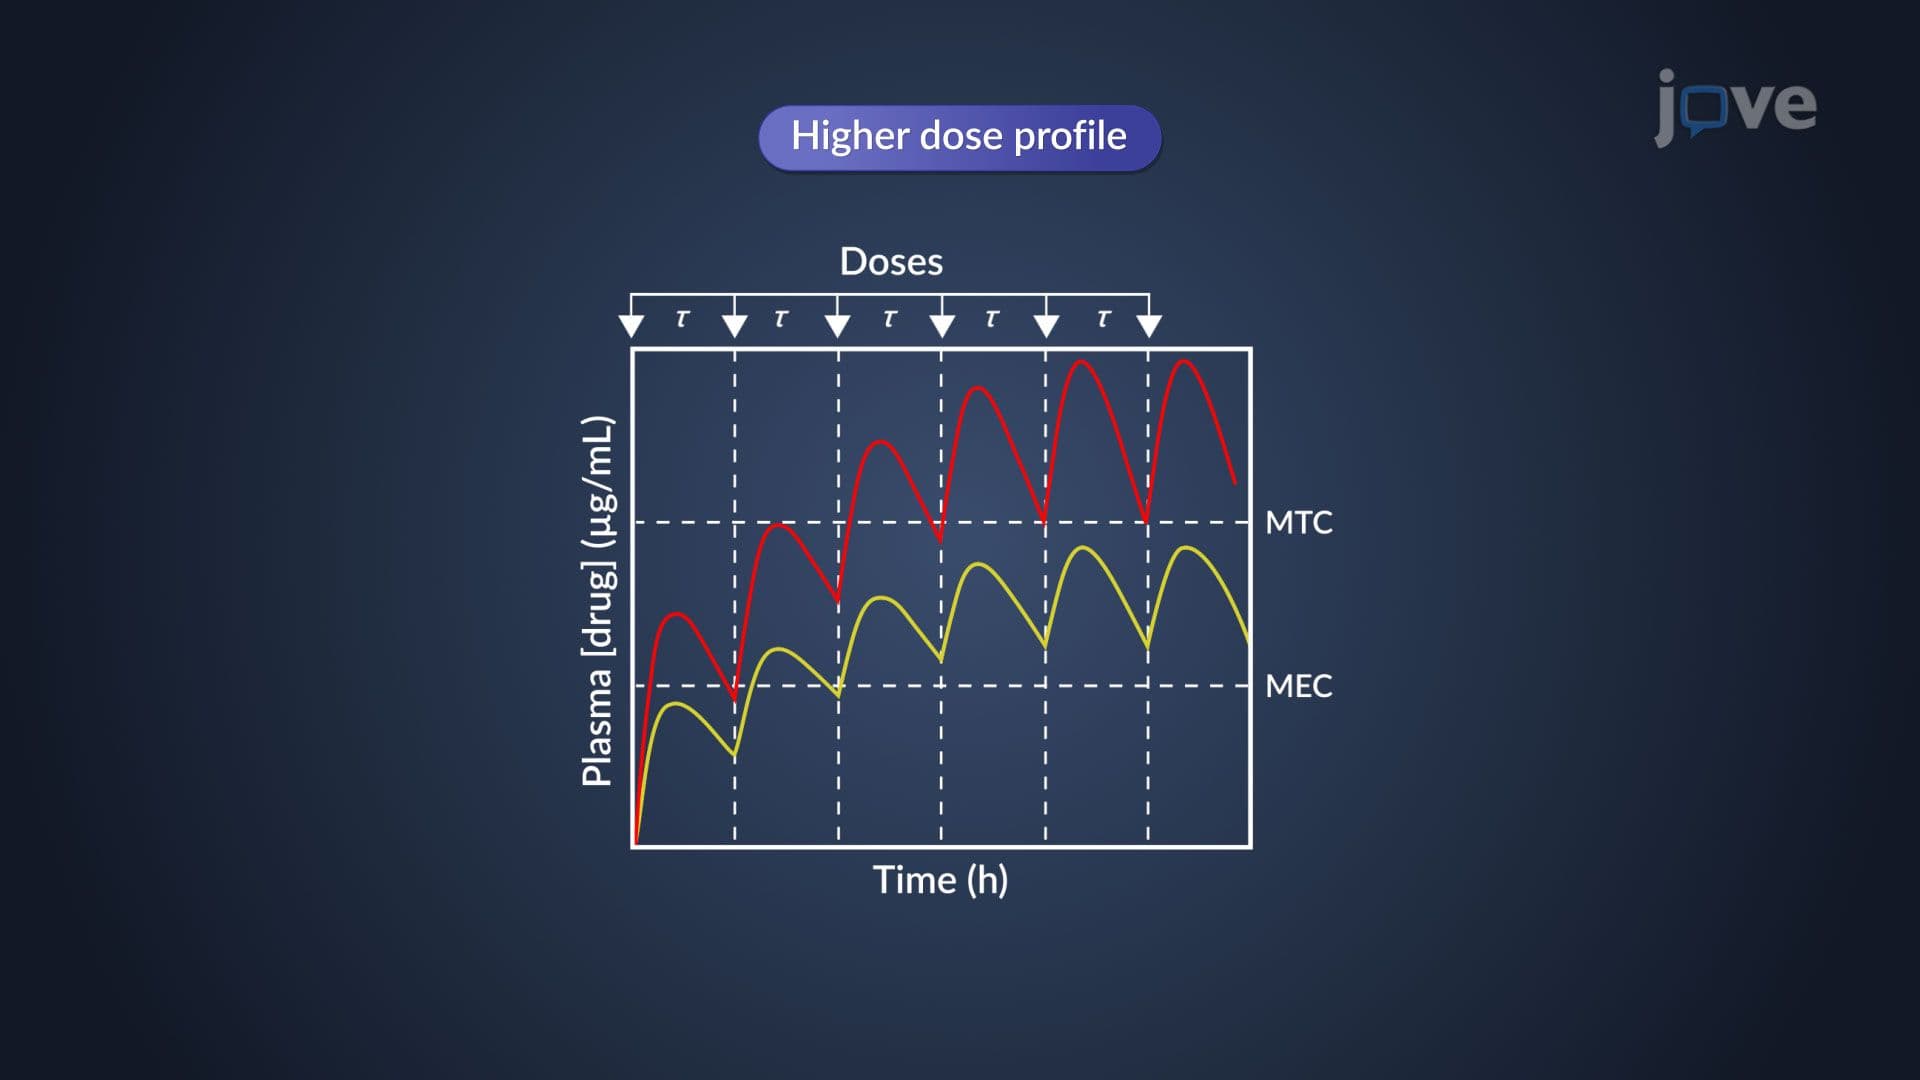
Dose Size and Dosing Frequency: Determination Methods