Related Experiment Video
Updated: Jan 29, 2026
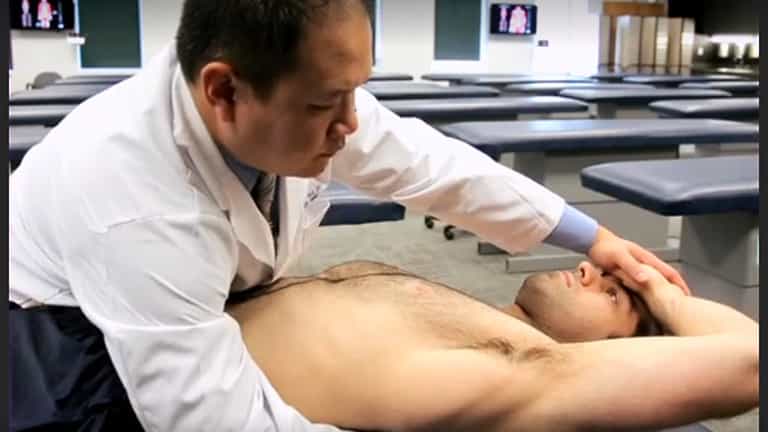

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Timing of Antibiotics in ICU Pneumonia: An Observational Association Between Early Treatment and Higher Mortality
1Department of Internal Medicine, Division of Pulmonary, Allergy and Sleep Medicine, HELIOS Clinic Wuppertal, Witten/Herdecke University, Heusnerstr. 40, 42283 Wuppertal, Germany.

Abstract:
Background: Early administration of antibiotics is commonly recommended for pneumonia in intensive care unit (ICU) patients. However, the clinical benefit of very early empirical treatment remains uncertain and may reflect differences in illness severity, baseline risk, or care pathways, particularly in non-septic or hemodynamically stable ICU populations. Methods: We performed a retrospective cohort study using the Medical Information Mart for Intensive Care IV (v2.2) database to evaluate the observational association between antibiotic timing and in-hospital mortality among adult ICU patients with pneumonia. Patients were categorized as receiving early (<3 h) or delayed (≥3 h) antibiotic therapy after ICU admission. A multivariable logistic regression model adjusted only for age and sex. Given the absence of detailed severity-of-illness measures, no causal inference was intended, and all analyses were considered hypothesis-generating. Additional analyses exploring antibiotic class, dosing frequency, and combination therapy were conducted in an exploratory manner, given substantial variation in sample sizes and a high risk of confounding by indication, misclassification, immortal-time, and survivorship bias. Results: Among 7569 ICU patients with pneumonia, 56.5% received antibiotics within three hours of ICU admission. Early antibiotic initiation was associated with higher in-hospital mortality than delayed therapy (26.1% vs. 21.5%; OR 1.30, 95% CI 1.16-1.44; p < 0.001). Because validated severity-of-illness measures were unavailable, residual confounding and confounding by indication are likely and may largely explain this association. A potential signal of increased mortality was observed in patients receiving ≥3 doses of levofloxacin (OR 4.39, 95% CI 1.13-17.02); however, this subgroup was small and the finding is highly susceptible to survivorship and indication bias. Mortality appeared lower in patients receiving two or three antibiotics compared with monotherapy, but marked group imbalances, lack of restriction or stratification, and clinical selection effects limit interpretability. Regimens involving ≥4 agents were rare and primarily associated with prolonged ICU length of stay rather than a clear mortality difference. Conclusions: In this large retrospective ICU cohort, very early antibiotic administration for pneumonia was observationally associated with higher in-hospital mortality. Causality cannot be inferred, and early treatment likely represents a marker of higher baseline risk or clinical urgency rather than a harmful exposure. These findings challenge the assumption that earlier antibiotic initiation is uniformly beneficial and underscore the importance of individualized, stewardship-aligned, and context-dependent decision-making regarding antimicrobial timing and intensity in critically ill patients.


Related Concept Videos
 00:57
Antibiotic Selection
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia II: Pathophysiology
 02:30
Naturalistic Observations
 01:21
Association Areas of the Cortex
Prefrontal Association Area: This area is located in the frontal lobe and is involved in planning, decision-making, and moderating social behavior. It connects with primary motor areas,...
 01:27
Associative Learning
Classical conditioning, also known...