Related Experiment Video
Updated: Jan 30, 2026

An In Vivo Method to Study Mouse Blood-Testis Barrier Integrity
Published on: December 2, 2018
Prevalence, Determinants, and Barriers to Reproductive Health Decision-Making Autonomy Among Married Women in Rural
Shimelis Gobena1, Seifadin Ahmed Shallo2, Gemechu Gelan Bekele3
1Southwest Shewa Zone Health Office, Oromia Regional Health Bureau Wolliso Ethiopia.

Background And Aim:
In rural Ethiopia, where patriarchal norms prevail, women's limited decision-making autonomy significantly restricts their reproductive health (RH) service utilization. However, scarcity of data persists. Hence, this study assesses the prevalence, determinants, and barriers to RH decision-making autonomy among married women in rural parts of Seden Sodo district, Southwest Ethiopia.
Methods:
A community-based mixed-methods study was conducted from December 2022 to January 2023 among 594 systematically selected married women in the Seden Sodo district, Southwest Ethiopia. The quantitative data were collected using structured interviewer-administered questionnaires and analyzed by SPSS version 27. Women's decision-making autonomy was assessed across four key reproductive health areas including family planning, antenatal care, place of delivery, and postnatal care using a weighted scoring system: 2 for sole decision-maker, 1 for joint decisions, and 0 if the husband decided alone. Women who scored above the mean were considered autonomous. Sixteen key informants participated in qualitative interviews analysed thematically to explore contextual barriers with triangulation of the findings.
Results:
Only 53.2% (95% CI: 49-57) of women demonstrated autonomous RH decision-making. Merchant occupation (AOR = 6.88, 95% CI: 3.12-15.14), age at marriage age > 18 years (AOR = 5.49, 95% CI: 3.20-9.43), husband's education (AOR = 3.51, 95% CI: 2.10-5.90), favourable RH perceptions (AOR = 2.08, 95% CI:1.05-4.12) and women's education (AOR = 0.47, 95% CI: 0.30-0.76) were significantly associated with RH decision-making autonomy. Qualitative analysis revealed three key barriers: entrenched male dominance in health decisions, female economic marginalization, and mobility restrictions impeding service access.
Conclusion And Recommendation:
While approximately half of rural women demonstrate some RH decision-making autonomy, significant barriers persist. Therefore, programs promoting women's economic participation, challenging patriarchal norms, and engaging male partners are critical to enhancing autonomous RH decisions and improving maternal health outcomes.


Related Concept Videos
 01:09
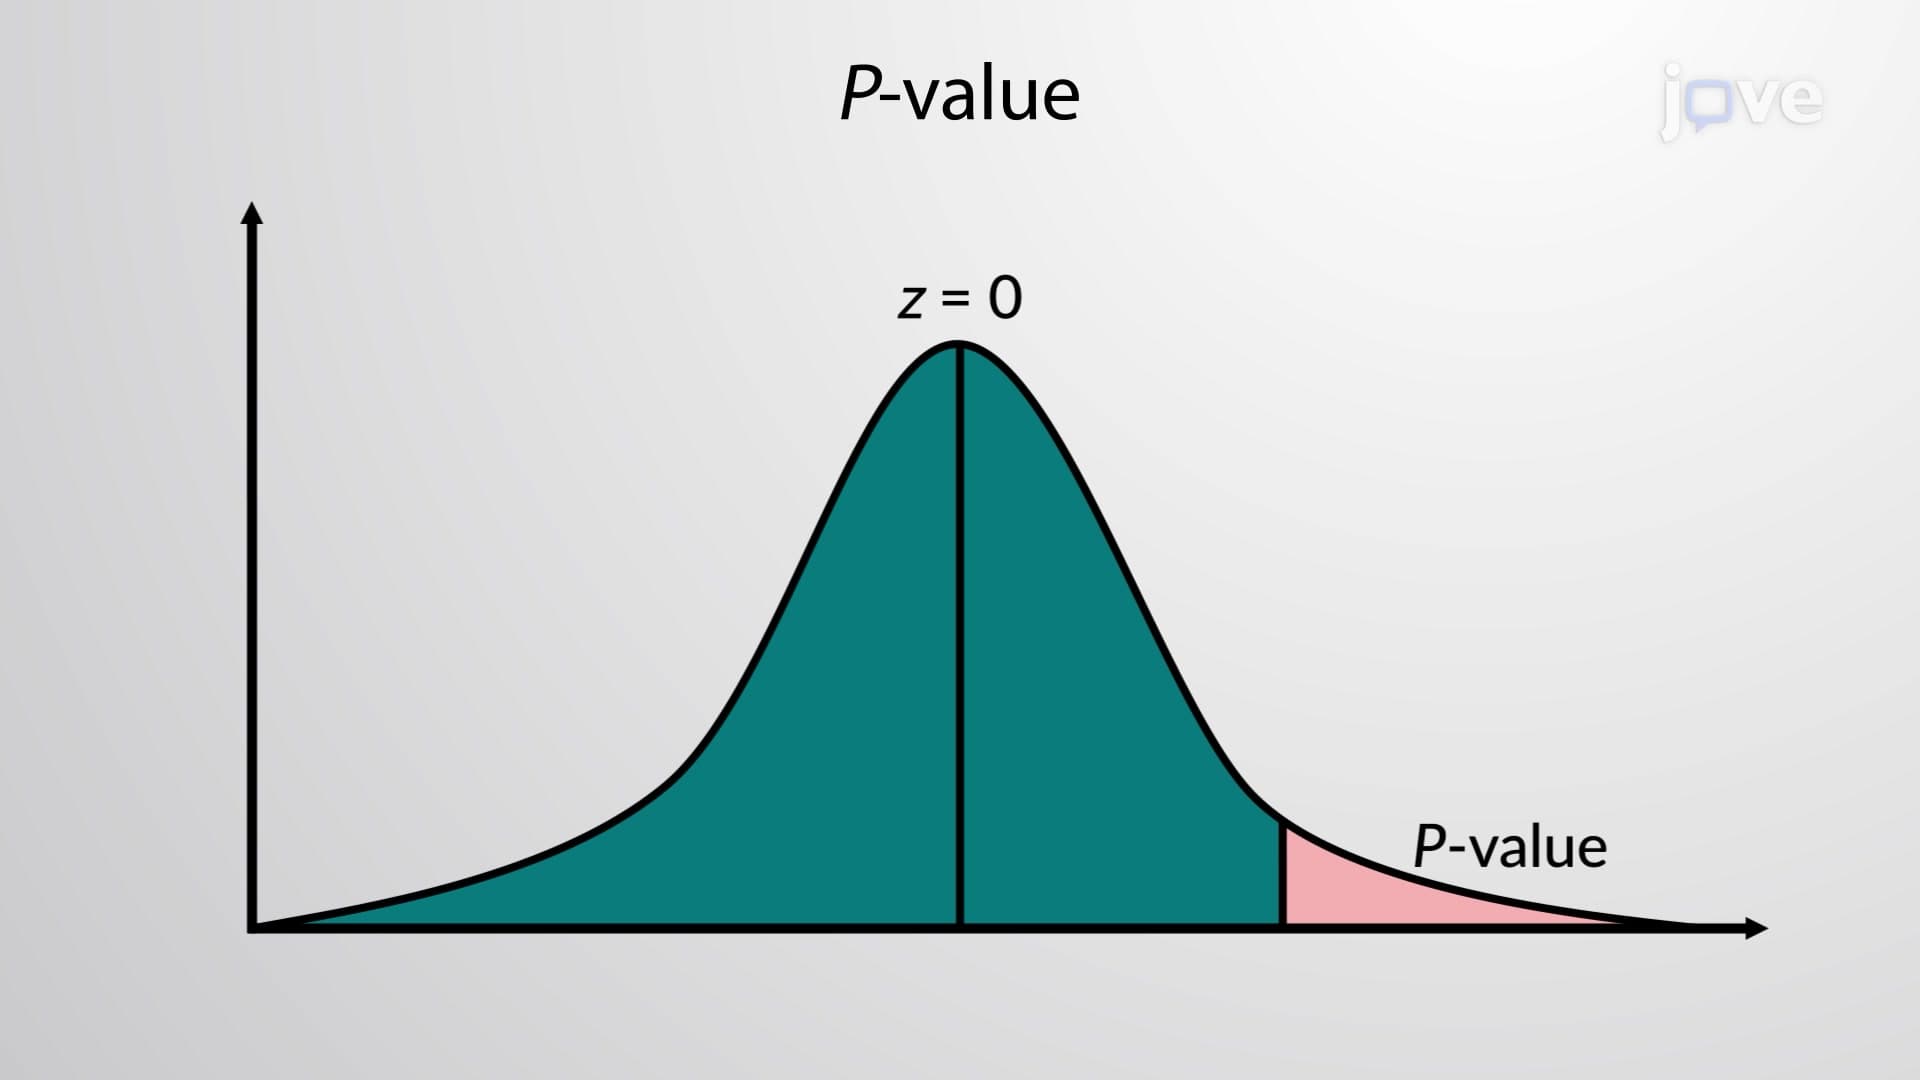
Decision Making: P-value Method
First, a specific claim about the population parameter is proposed. The claim is based on the research question and is stated in a simple form. Further, an opposing statement to the claim is also stated. These statements can act as null and alternative hypotheses: a null hypothesis would be a neutral statement while the alternative hypothesis can...
 01:08
Prevalence and Incidence
Prevalence indicates the proportion of individuals in a population who have a specific disease or health...
 01:14
Decision Making: Traditional Method
First, a specific claim about the population parameter is decided based on the research question and is stated in a simple form. Further, an opposing statement to this claim is also stated. These statements can act as null and alternative hypotheses, out of which a null hypothesis would be a...
 01:27
Reproductive Cloning
Somatic Cell Nuclear Transfer
In SCNT, an egg cell is taken from an animal and its nucleus is removed, creating an enucleated egg. Then a somatic...
 01:20
Decision Making
Automatic decision-making is fast, intuitive, and relies on gut feelings...
 02:38
Asexual Reproduction