Related Experiment Video
Updated: Feb 1, 2026
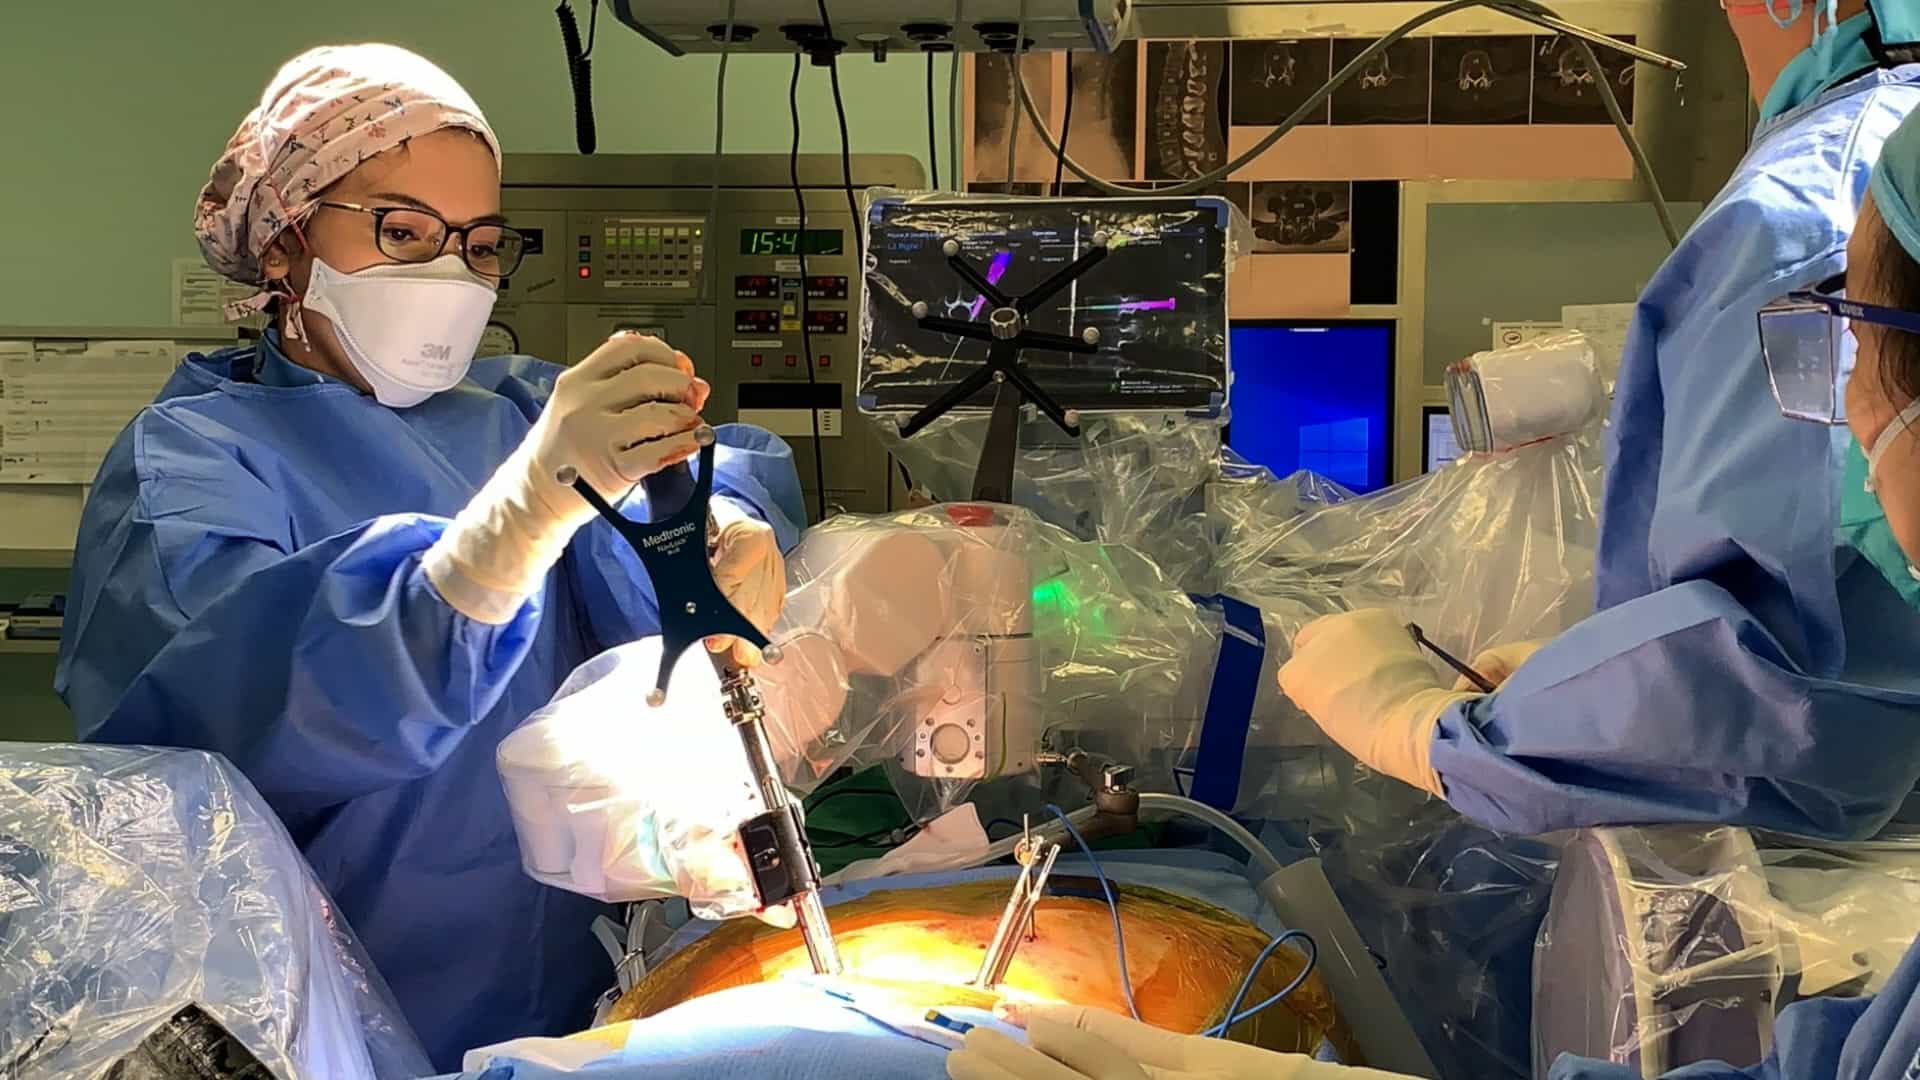

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Interspinous process fixation versus posterior lumbar interbody fusion following decompression for single-level grade
Jingbo Ma1,2, Tusheng Li1,3, Nan Shen1
1Orthopedics of TCM Senior Department, The Sixth Medical Center of People's Liberation Army General Hospital, Beijing, 100048, China.

Objective:
To compare clinical outcomes and radiographic parameters between interspinous process fixation (ISPF) and posterior lumbar interbody fusion (PLIF) in patients with single-level degenerative lumbar spinal stenosis (LSS) associated with Meyerding Grade I spondylolisthesis.
Methods:
We retrospectively analyzed 107 patients who underwent ISPF (n = 55) or PLIF (n = 52) between January 2019 and January 2023. Propensity score matching (PSM) was performed using covariates including age, sex, BMI, symptom duration, smoking history, diabetes mellitus, hypertension, and affected spinal level, resulting in 36 matched pairs. Clinical efficacy was evaluated using the Visual Analog Scale (VAS), Oswestry Disability Index (ODI), Japanese Orthopaedic Association (JOA) score, and Macnab criteria. Radiographic assessments included lumbar lordosis (LL), pelvic incidence (PI), pelvic tilt (PT), segmental angle (SA), and disc height (DH). All patients completed more than 24 months of follow-up.
Results:
Post-matching analysis demonstrated good baseline balance (SMD < 0.20, P > 0.05). ISPF showed superior short-term outcomes, with significantly greater improvement in VAS scores both immediately postoperatively (2.52 ± 1.39 vs. 3.21 ± 1.23, P = 0.0078) and at the 3-month follow-up (1.83 ± 1.31 vs. 2.54 ± 1.20, P = 0.0042). Similarly, ODI favored ISPF at the immediate postoperative evaluation (38.64 ± 8.86 vs. 42.17 ± 6.77, P = 0.0221) and at 3 months (25.61 ± 8.84 vs. 30.15 ± 6.75, P = 0.0035), whereas no significant between-group differences were observed at 1 year and at the final follow-up (both P > 0.05). Radiographically, ISPF achieved superior LL (45.13° ± 4.97 vs. 40.37° ± 7.37, P = 0.0002) and lower PT (12.49° ± 7.62 vs. 15.80° ± 8.26, P = 0.0334), whereas PLIF demonstrated greater correction of the slip angle (SA: 10.99° ± 2.53 vs. 12.52° ± 1.48, P = 0.0004). Long-term clinical outcomes and patient satisfaction rates were comparable (Macnab excellent-to-good: 86.11% ISPF vs. 83.33% PLIF, P = 0.9420).
Conclusions:
ISPF provided better short-term clinical recovery and maintenance of sagittal alignment, whereas PLIF offered greater slip correction. Both procedures yielded comparable long-term clinical outcomes, supporting individualized surgical decision-making in patients with degenerative LSS and Grade I spondylolisthesis.
Related Concept Videos
 02:45
Nuclear Fusion
A helium nucleus has a mass that is 0.7% less than that of four hydrogen nuclei; this lost mass is converted into energy during the fusion. This reaction produces about...
 01:17
Sign Test for Matched Pairs
To conduct the sign test, we first calculate the differences in...
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:19
Graded Potential
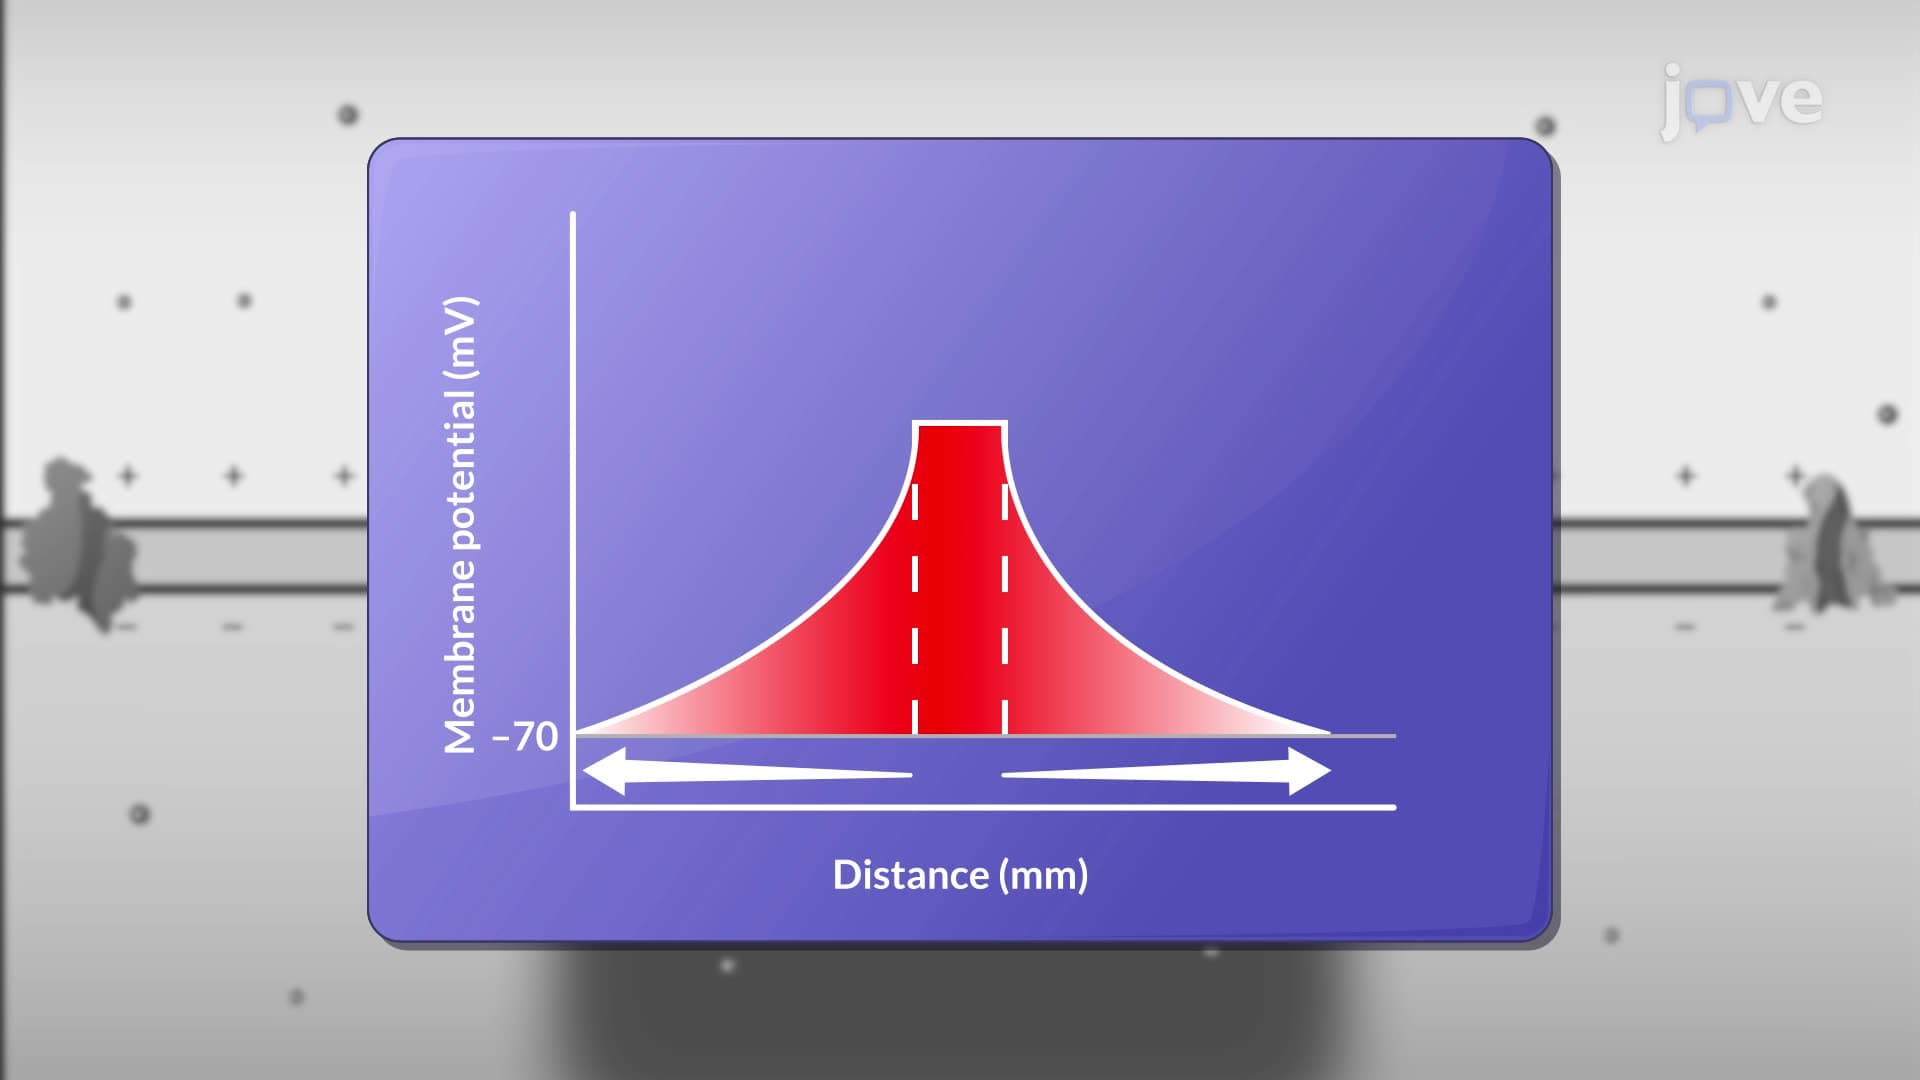
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:06
Introduction to z Scores
z scores...
 01:05
Introduction to z Scores
z scores...