Related Experiment Video
Updated: Feb 2, 2026


Controlled Cortical Impact Model for Traumatic Brain Injury
Published on: August 5, 2014
Reduction of Neuro Check Intervals in Traumatic Brain Injury Patients is Associated with Lower Delirium Risk
Jayati Atahar1, Jeremy Hayward1, Alex I Halpern1
1Department of Surgery, The George Washington University School of Medicine and Health Sciences, Washington, DC.

Introduction:
Delirium is a common finding among patients with traumatic brain injuries (TBIs). Lack of sleep has been identified as contributing factors to the development of delirium. However, TBI patients in the intensive care unit (ICU) often undergo every-hour neurologic examinations (Q1 neuro checks) that disrupt their sleep. We sought to better understand the association between Q1 neuro check duration and delirium in ICU TBI patients. We hypothesize that shorter duration of Q1 neuro checks in TBI patients would be associated with fewer delirium diagnosis delirium without increased complications.
Methods:
We performed a single-institution retrospective cohort analysis of ICU patients with TBI who underwent Q1 neuro checks at a level 1 trauma center from December 2021 to July 2023. We excluded minors and patients who died within 24 h of admission, and patients with catastrophic brain injury incompatible with life. We divided the cohort between those who underwent Q1 neuro checks for less than 24 h and those who underwent Q1 neuro checks for greater than 24 h. We used univariate and multivariate analyses to evaluate our primary outcome, delirium. Delirium diagnosis was done by the ICU clinicians based on the Diagnostic and Statistical Manual of Mental Disorders, 5th Edition criteria. We used multivariate logistic and linear regression models to analyze unplanned return to ICU, intracranial rebleed, other complications, mortality, hospital and ICU length of stay (LOS), and a Cox proportional hazards model to analyze the hazard ratios for all the complications and death.
Results:
We identified 153 patients, 93 underwent Q1 neuro checks for less than 24 h and 60 underwent Q1 neuro checks for greater than 24 h. On univariate analysis, there was not a significant difference in rates of delirium between the groups who underwent Q1 neuro checks for less than 24 h and for greater than 24 h (odds ratio [OR] 2.15; 95% confidence interval [CI] 0.79-5.91, P = 0.14). However, on multivariate analysis, after controlling patient demographics, initial Glasgow Coma Scale (GCS), Injury Severity Score, injury status, ventilation requirement, and presence of complications; patients undergoing Q1 neuro checks for more than 24 h had a statistically significant increased risk of delirium (OR 9.73; 95% CI 1.14-82.90, P < 0.05), mortality (OR 17.11; 95% CI 1.72-170.77, P < 0.05), and ICU LOS (2.57 days; 95% CI 1.23-3.92, P < 0.05) compared to the Q1 ≤ 24 h group. There was no significant difference in overall complications between the two groups (hazard ratio = 1.52, 95% CI 0.76-3.06, P = 0.24).
Conclusions:
This study found that Q1 neuro checks for more than 24 h for TBI patients were associated with a significantly increased risk of delirium, mortality, and ICU LOS with no significant increase in overall complications. Further studies with larger patient populations are required to confirm these results and to better understand which TBI patients would benefit from a shorter duration of Q1 neuro checks.


Related Concept Videos
 03:28
Vapor Pressure Lowering
 01:03
Prediction Intervals
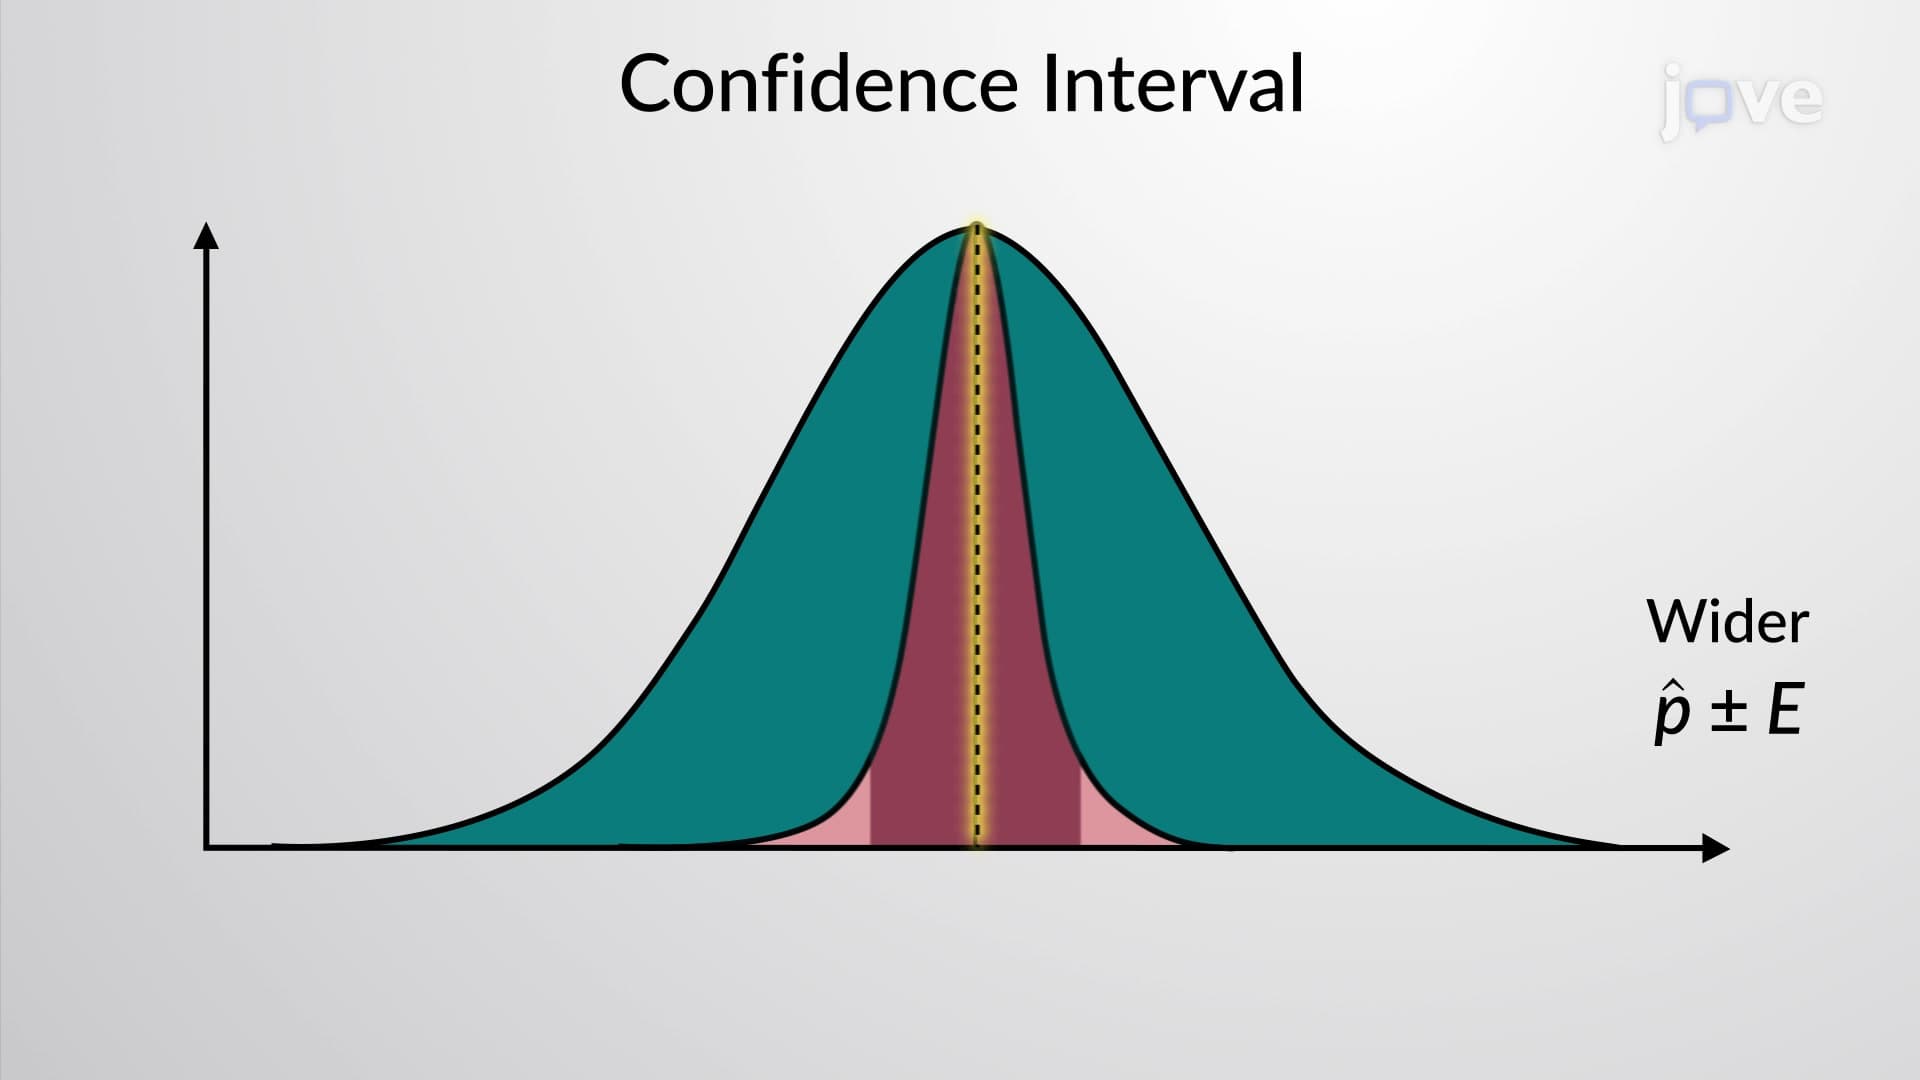
However, the point estimate is most likely not the exact value of the population parameter, but close to it. After calculating point estimates, we construct interval estimates, called confidence intervals or prediction intervals. This prediction interval comprises a range of values unlike the point estimate and is a better predictor of the observed sample value, y.
 01:29
Protein Folding Quality Check in the RER
 03:11
Oxidation-Reduction Reactions
 01:21
Confidence Intervals
A...
 01:12
Relative Risk