Related Experiment Video
Updated: Feb 2, 2026


A Surgical Procedure for Resecting the Mouse Rib: A Model for Large-Scale Long Bone Repair
Published on: January 21, 2015
Age, glenoid bone fragment, and glenoid bone loss increase recurrence risk after arthroscopic bony Bankart repair
Petar Golijanin1, Paolo Spinello2, Fabrizio Brindisino3
1The University of Texas at Austin Dell Medical School, Austin, Texas, USA.

Aims:
Numerous studies have identified risk factors for recurrent anterior shoulder dislocation, but the exact impact of each remains unclear. This study analyzes outcomes after arthroscopic bony Bankart repair (ABBR) and evaluates how time to surgery, number of preoperative instability events, age, glenoid bone loss (GBL), glenoid bone fragment (GBF), age at surgery, and preoperative Western Ontario Shoulder Instability (WOSI) scores influence recurrence.
Methods:
A retrospective review was conducted of patients who underwent ABBR between January 2008 and December 2018. Data included demographic details, number of instability episodes, time to surgery, age at first dislocation, GBL, GBF size, WOSI scores, and recurrence rates.
Results:
A total of 243 patients with bony Bankart lesions were included. The mean age was 25.4 years (17 to 46). Recurrence occurred in 24 patients (9.9%). Compared with the non-recurrence group, patients with recurrence had smaller GBF (6.5% (SD 4.2) vs 8.8% (SD 5.6); p = 0.049), longer elapsed time since initial instability (20.0 months vs 13.2 months; p < 0.001), younger age at initial instability (21.9 years (SD 6.9) vs 25.6 years (SD 5.2); p = 0.002), and more preoperative instability events (5.7 (SD 3.1) vs 3.8 (SD 2.0); p < 0.001). Postoperative WOSI scores improved in both groups but were not significantly different (447 (SD 141) vs 381 (SD 98)). Regression analysis showed that older age, larger GBF, and lower GBL were independently associated with reduced recurrence risk.
Conclusion:
Patients without recurrence were generally older, had shorter delay from the initial instability event, fewer preoperative instability events, and larger GBF for incorporation in the repair. In younger patients, smaller GBF and greater GBL were strongly associated with recurrence. These findings indicate that the longer the elapsed time, the greater the reabsorption of the glenoid bone fragment and, consequently, the greater the glenoid bone loss. Therefore, strategies aimed at preserving fragment size, potentially through timely surgical intervention, may help reduce recurrence. In patients aged over 40 years, GBL and GBF did not confer the same recurrence risk. Further studies are needed to clarify the thresholds for elapsed time and number of instability events that significantly affect recurrence after ABBR.
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 02:31
Habitat Fragmentation
 01:55
Bone Structure
 01:40
Bone Remodeling
 01:27
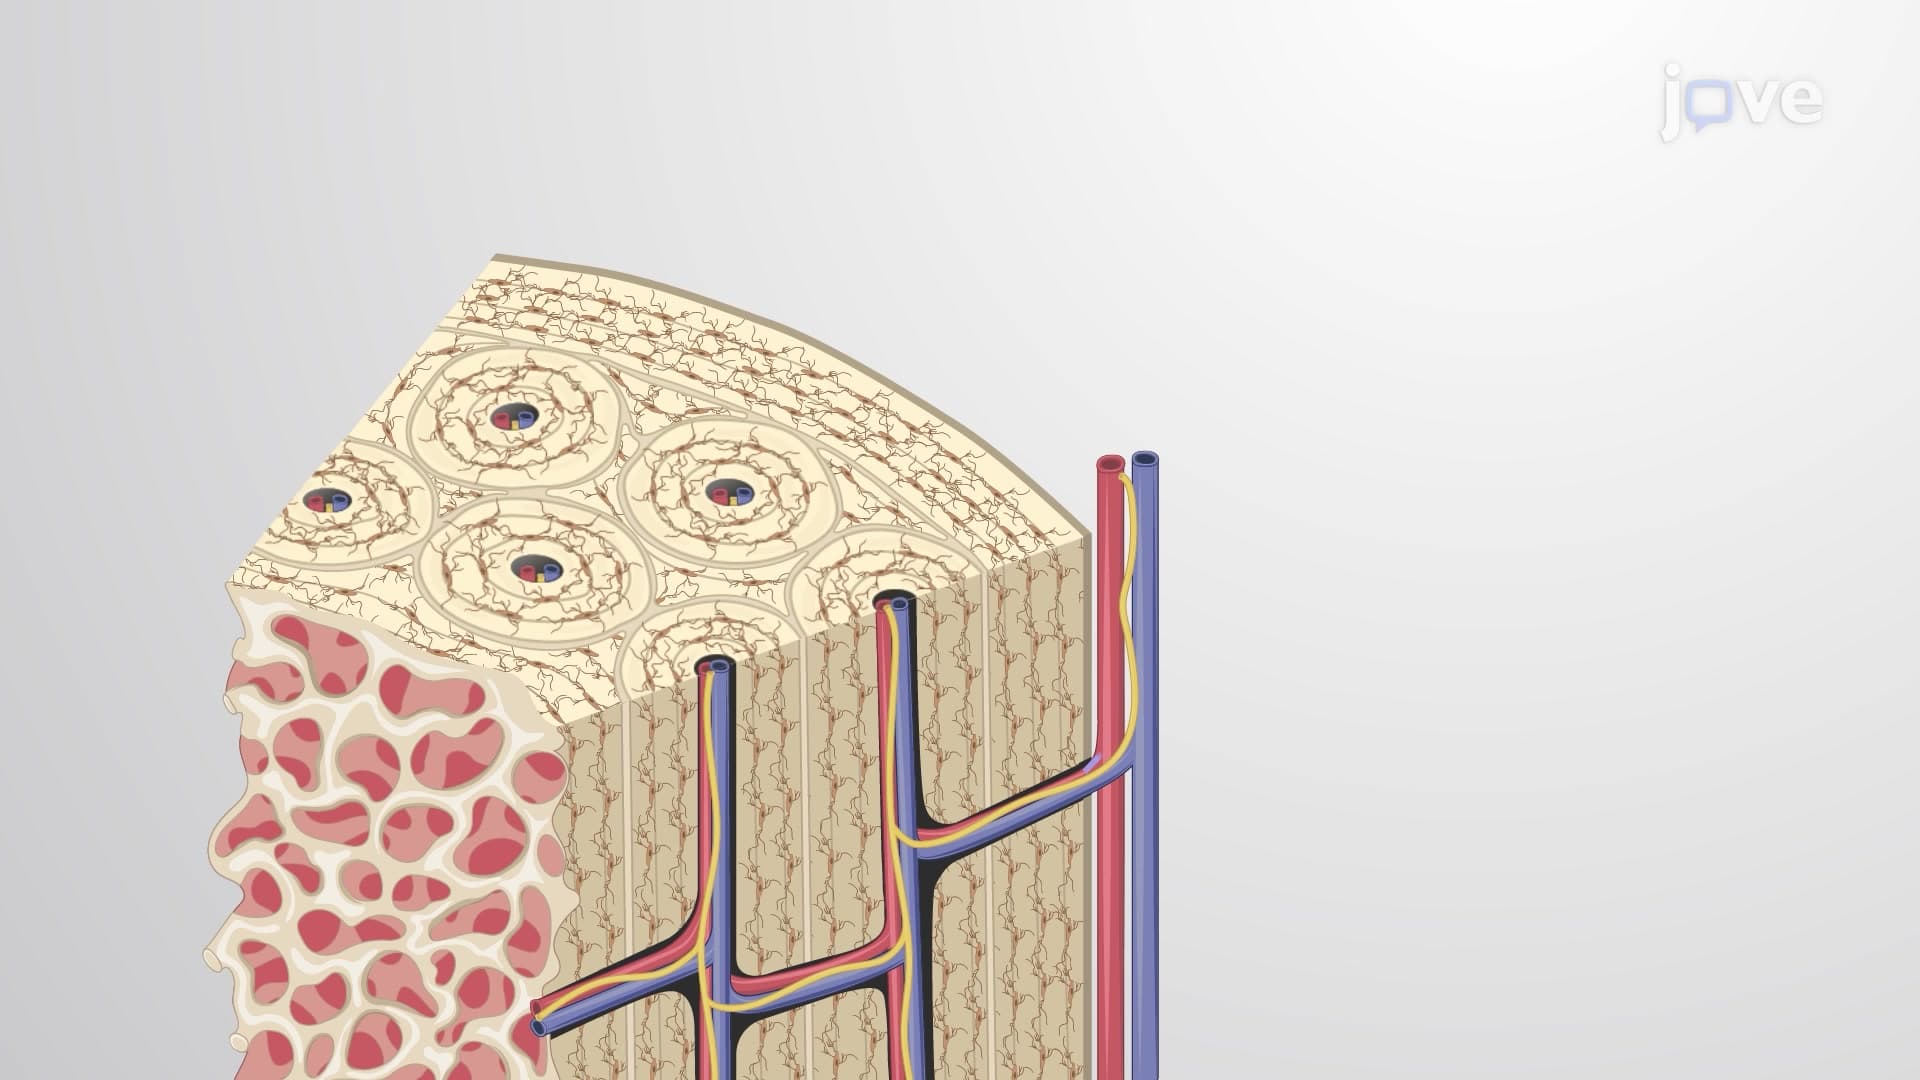
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...