Related Experiment Video
Updated: Feb 4, 2026
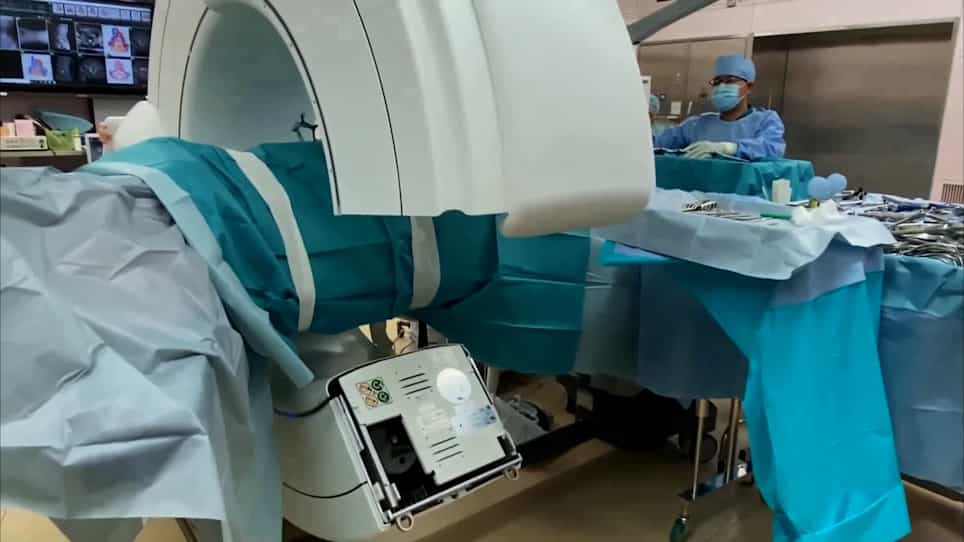
Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Interlaminar Versus Transforaminal Full-Endoscopic Lumbar Discectomy for L4-L5 Disc Herniation: Operative Time,
Tomasz Sienkiel1,2, Marcin Gaska1,2, Jakub Kalisz1,2
1Department of Orthopedics, University Orthopedic and Rehabilitation Hospital, Zakopane, POL.

Background L4-L5 disc herniation is a common cause of radiculopathy, yet the optimal full-endoscopic lumbar discectomy approaches: interlaminar endoscopic lumbar discectomy (IELD) or transforaminal endoscopic lumbar discectomy (TELD), remain debated due to level-specific anatomical constraints. This study compared operative efficiency, radiation exposure, complications, and clinical outcomes between IELD and TELD at the L4-L5 level. Methods A retrospective analysis of 131 consecutive L4-L5 full-endoscopic discectomies (42 IELD, 89 TELD) performed between 2021 and 2023 was conducted. Operative time, fluoroscopic dose-area product, anesthesia type, complications, and patient-reported outcomes (VAS, ODI) were recorded at baseline, 3 months, and 12 months. Temporal trends and learning-curve patterns were evaluated. Results A marked shift from IELD to TELD occurred over the study period, with TELD accounting for 90% of cases by 2023, and conscious analgesia was used in 94%. Operative time improved for both techniques, plateauing at 47 minutes for IELD and 42 minutes for TELD. Radiation exposure declined substantially for both approaches, decreasing from 160 to 120 µGym² for IELD and from 280 to 180 µGy·m² for TELD; however, TELD remained numerically higher than IELD in the late phase. All complications (five total) occurred early in the study period, with none recorded after 2022. Both approaches produced significant improvements in VAS and ODI scores, with comparable long-term clinical outcomes between groups. Conclusions Both IELD and TELD produced significant and sustained improvements in VAS and ODI, with no differences in long-term clinical outcomes. TELD showed a steeper learning-curve pattern and shorter operative times after proficiency was achieved, and it was increasingly performed under conscious analgesia. Fluoroscopy dose declined substantially over time for both approaches; however, TELD required higher radiation exposure during early adoption and remained numerically higher than IELD in late phases. Approach selection at L4-L5 should therefore prioritize anatomy, surgeon experience, and perioperative goals rather than expectations of superior long-term outcomes.
Background L4-L5 disc herniation is a common cause of radiculopathy, yet the optimal full-endoscopic lumbar discectomy approaches: interlaminar endoscopic lumbar discectomy (IELD) or transforaminal endoscopic lumbar discectomy (TELD), remain debated due to level-specific anatomical constraints. This study compared operative efficiency, radiation exposure, complications, and clinical outcomes between IELD and TELD at the L4-L5 level. Methods A retrospective analysis of 131 consecutive L4-L5 full-endoscopic discectomies (42 IELD, 89 TELD) performed between 2021 and 2023 was conducted. Operative time, fluoroscopic dose-area product, anesthesia type, complications, and patient-reported outcomes (VAS, ODI) were recorded at baseline, 3 months, and 12 months. Temporal trends and learning-curve patterns were evaluated. Results A marked shift from IELD to TELD occurred over the study period, with TELD accounting for 90% of cases by 2023, and conscious analgesia was used in 94%. Operative time improved for both techniques, plateauing at 47 minutes for IELD and 42 minutes for TELD. Radiation exposure declined substantially for both approaches, decreasing from 160 to 120 µGym² for IELD and from 280 to 180 µGy·m² for TELD; however, TELD remained numerically higher than IELD in the late phase. All complications (five total) occurred early in the study period, with none recorded after 2022. Both approaches produced significant improvements in VAS and ODI scores, with comparable long-term clinical outcomes between groups. Conclusions Both IELD and TELD produced significant and sustained improvements in VAS and ODI, with no differences in long-term clinical outcomes. TELD showed a steeper learning-curve pattern and shorter operative times after proficiency was achieved, and it was increasingly performed under conscious analgesia. Fluoroscopy dose declined substantially over time for both approaches; however, TELD required higher radiation exposure during early adoption and remained numerically higher than IELD in late phases. Approach selection at L4-L5 should therefore prioritize anatomy, surgeon experience, and perioperative goals rather than expectations of superior long-term outcomes.
Related Concept Videos
 02:59
Biological Effects of Radiation
 01:24
Hemodialysis II: Procedure and Complications
 01:17
Radiation: Applications
The average...
 01:05
Absorption of Radiation
 02:44
Heating and Cooling Curves
For instance, the addition of heat raises the temperature of a solid; the amount of heat absorbed depends on the heat capacity of the solid (q = mcsolidΔT). According to thermochemistry, the relation between the amount of heat absorbed or released by a substance, q, and its...
 01:30
Pneumonia III: Complications and Assessment