Related Experiment Video
Updated: Feb 4, 2026
Author Spotlight: Advancements and Challenges in Machine Perfusion for Liver Transplantation
Published on: June 14, 2024
Impact of Model for End-stage Liver Disease Cutoffs on Liver Transplant Access in the United States: A Regression
Tomohiro Tanaka1,2,3, Michael P Jones2,4, George Wehby2,3,5,6
1Division of Gastroenterology and Hepatology, University of Iowa Carver College of Medicine, Iowa City, IA.

Background:
Since Share-35 and continuing under the Acuity Circle (AC) policy, US liver transplant (LT) allocation has relied on Model for End-Stage Liver Disease (MELD) thresholds that may distort fair and seamless access.
Methods:
We analyzed adult LT candidates listed from January 2016 to June 2024. Regression discontinuity analysis using Poisson regression for top-5 offer rates and discrete-time hazard regression for transplant rates and waitlist mortality estimated policy effects at a MELD score of 35 (MELD-35; Share-35) and MELD scores of 33 and 37 (MELD 33/37; AC). Secondary analyses were used to analyze the offer decline rates and donor characteristics at each MELD threshold.
Results:
In total, 98 896 candidates were analyzed. During Share-35, crossing the MELD-35 threshold was associated with significant increases in offers (rate ratio [RR], 3.39; 95% confidence interval [CI], 3.22-3.57) and transplants (odds ratio [OR], 2.13; 95% CI, 1.89-2.41). Under AC, smaller but significant effects were observed at MELD-37 (RR, 1.37; 95% CI, 1.31-1.44; OR, 1.15; 95% CI, 1.01-1.30) and at MELD-33 (RR, 1.48; 95% CI, 1.21-1.38 and OR, 1.16; 95% CI, 1.03-1.30). Candidates with an MELD score <37 experienced significantly higher waitlist mortality (OR, 0.40; 95% CI, 0.24-0.67). Secondary analyses showed higher decline rates at MELD-35 under Share-35, but lower rates at MELD 33/37 under AC with reduced marginal donor use.
Conclusions:
MELD thresholds continue to influence LT access and donor quality/selection, creating artificial discontinuities and unintended disparity that misalign allocation with true disease severity. These findings support avoiding rigid score-based cutoffs not only in future US allocation models (eg, continuous distribution), but also in broader international allocation frameworks moving forward.
Related Concept Videos
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:27
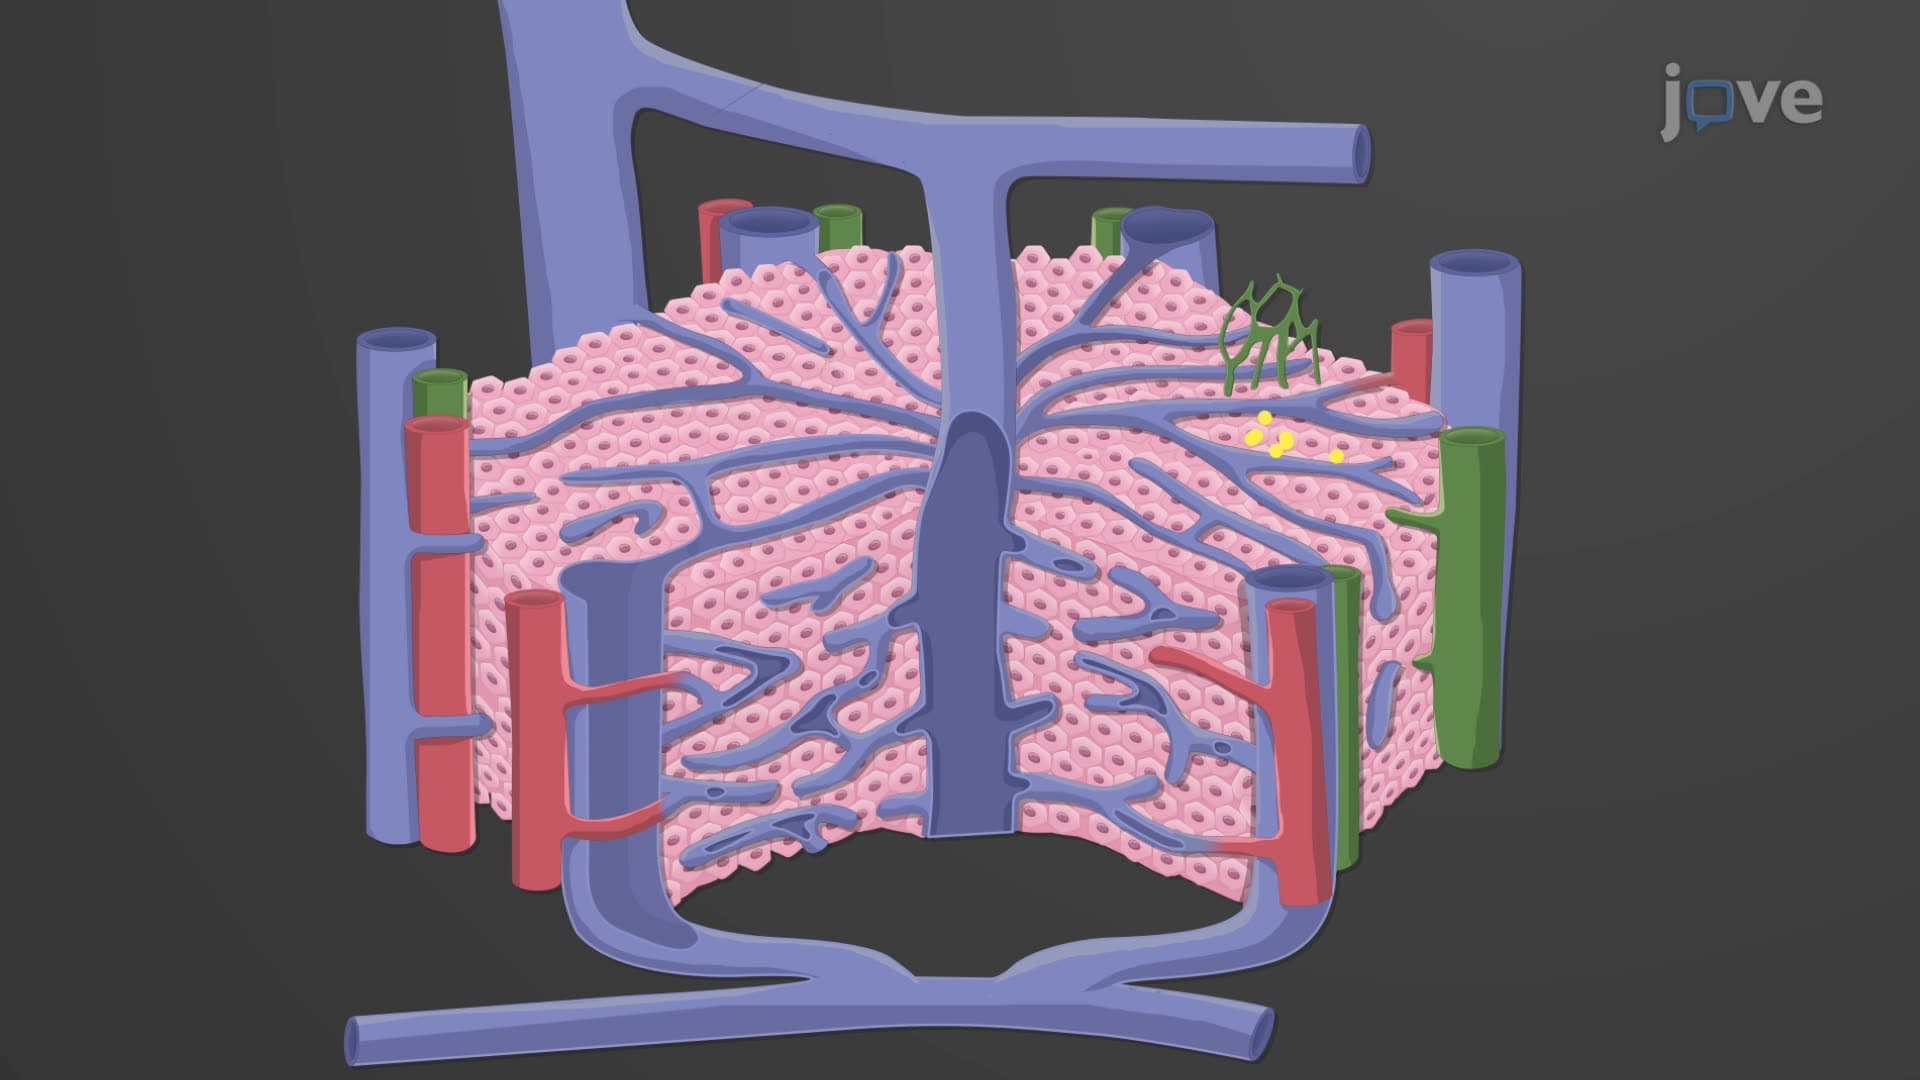
Liver Histology
Hepatocytes perform a variety of essential functions. They secrete...
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can...
 01:24
Liver Regeneration
Cells of Liver
The liver comprises four major types of cells— hepatocytes, stellate, Kupffer, and sinusoidal endothelial cells. The hepatocytes are...
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:52
Regression Toward the Mean