Related Experiment Video
Updated: Feb 4, 2026
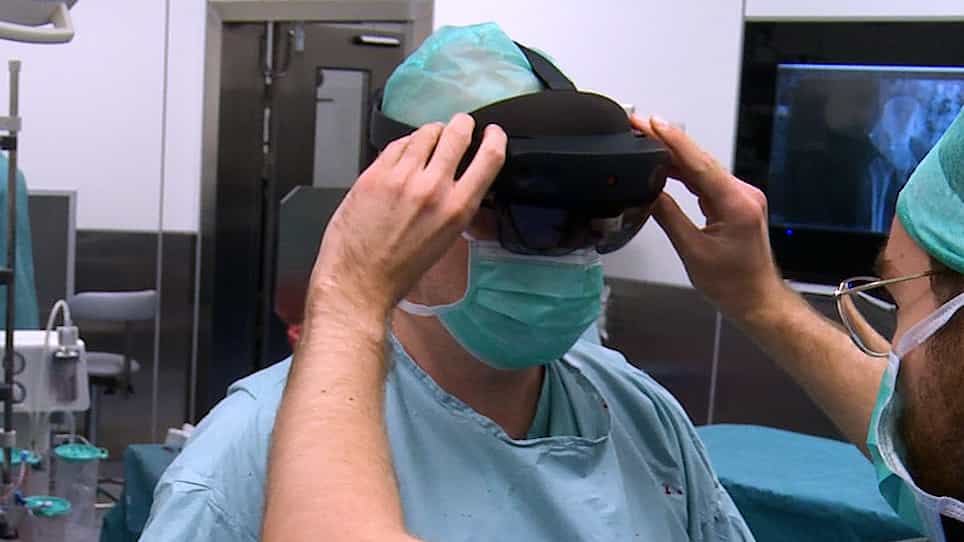
The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Why revision of total hip arthroplasty fails: a retrospective consecutive cohort study of 963 patients
Valentin Cascales1, Constant Foissey2, Marcelle Mercier3
1Department of Orthopaedic and Traumatological Surgery, Spine Surgery Unit, University Hospital of Nîmes (CHU), Nîmes, France.

Aims:
The aims of this study are to identify the causes and independent risk factors for failure following revision total hip arthroplasty (RTHA).
Methods:
We conducted a retrospective multicentre cohort study involving 963 patients who underwent RTHA between January 2016 and December 2021 across three French university hospitals, with a minimum follow-up of two years. Data collected included demographic details, revision rank (R1= first revision, R2= second revision, R ≥ 3=third or subsequent revision), surgical variables, complications, reoperations, re-revisions, and mortality. RTHA failure was defined as any reoperation or re-revision. Multivariate logistic regression was used to determine independent risk factors for failure.
Results:
The mean patient age was 72 years (14 to 104), with 55% of patients being female. The most common indications for RTHA were aseptic loosening (35.6%), periprosthetic fracture (32.0%), periprosthetic joint infection (PJI; 15.2%), and dislocation (5.7%). Failure occurred in 135 patients (14.0%), most frequently due to PJI (53%), of which 61% were new infections. Among patients revised for dislocation, recurrent instability accounted for 43.7% of failures. Most failures (70%) occurred within one year of revision. Independent risk factors included age ≥ 75 years (odds ratio (OR) 0.61), revision rank ≥ 3 (OR 1.96), PJI (OR 2.0), dislocation (OR 2.86), use of revision (OR 2.38), and constrained acetabular cups (OR 5.38).
Conclusion:
Aseptic loosening remains the leading indication for revision surgery, while PJI is the principal cause of failure following RTHA, both as a new infection and as iterative failure. Recurrent dislocation continues to pose a complex challenge despite modern implant strategies, underscoring the need for meticulous surgical planning in high-risk patients.
Related Concept Videos
 01:17
Hypothesis: Accept or Fail to Reject?
There are two ways to indicate that the null hypothesis is not rejected. 'Accept' the null...
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:12
Total Voids in Concrete
 01:05
Total Internal Reflection Fluorescence Microscopy
 01:24
Static, Stagnation, Dynamic and Total Pressure
 01:13
Patient-centered Care