Related Experiment Video
Updated: Feb 6, 2026

Author Spotlight: Advancements and Challenges in Surgical Treatments for Postamputation Pain
Published on: March 8, 2024
Optimizing the protocol for modified natural cycle frozen embryo transfer (mNC-FET): a multicentre, single-blinded
Marte Saupstad1, Clara Colombo1, Sara Johanna Bergenheim1
1Fertility Clinic, Department of Gynaecology, Fertility and Obstetrics, Copenhagen University Hospital-Rigshospitalet, Copenhagen, Denmark.

Study Question:
Can the use of progesterone luteal phase support (LPS) and timing of blastocyst transfer, at 6 versus 7 days following hCG-trigger, improve the live birth rate (LBR) in modified natural cycle (mNC) frozen-thawed embryo transfer (FET)?
Summary Answer:
Use of LPS and advanced timing of blastocyst transfer did not significantly improve the LBR in mNC-FET.
What Is Known Already:
Transfer of a frozen-thawed blastocyst in the mNC protocol is routinely conducted 7 days after the ovulation trigger, and progesterone LPS is commonly used despite limited evidence.
Study Design Size Duration:
This multicentre, single-blinded, randomized controlled superiority trial investigated the effect of LPS and timing of blastocyst transfer on live birth rates following mNC-FET conducted from January 2019 to February 2024. Using an online randomization programme, patients were randomized 1:1:1:1 to: (A) transfer day 6 following ovulation trigger (Day 0) with LPS; (B) transfer day 7 with LPS; (C) transfer day 6 without LPS; (D) transfer day 7 without LPS. Use of LPS was masked from treating clinicians. The sample size calculation required 604 women to participate to detect an increase in live birth rate from 21% in control groups (LPS: C + D, timing: B + D) to 31% in intervention groups (LPS: A + B, timing: A + C). In total, 679 women were enrolled, and 610 women were randomized. Ultimately, 602 women (A: n = 151; B: n = 150; C: n = 149; D: n = 152) were included in the per-transfer analyses.
Participants/Materials Setting Methods:
Participants were women aged 18-41 years undergoing mNC-FET with a single autologous good-quality blastocyst, from eight public fertility clinics at tertiary care centres across Denmark.
Main Results And The Role Of Chance:
Our study found that use of LPS did not significantly affect the LBR compared with no LPS: 34.9% (105/301) versus 31.9% (96/301) (adjusted risk difference (aRD) 3.18, 95% CI: -4.13 to 10.49; P = 0.39). Comparing blastocyst transfer on Day 6 versus Day 7, there was again no significant difference in LBR: 33.8% (99/300) versus 33.0% (99/302) (aRD -0.62, 95% CI: -7.99 to 6.75; P = 0.87).
Limitations Reasons For Caution:
The sample size calculation was based on LBRs of studies using transfer of slow-frozen and cleavage stage embryos, but today's LBRs are higher. Consequently, the sample size might not have been sufficient to detect discrete differences in reproductive outcomes under present conditions. Further, despite using liberal inclusion criteria, most women participating were young (≤35 years) and lean, and had a good quality embryo available for transfer, giving them an a priori good treatment prognosis. Hence, our findings might not apply to all women undergoing mNC-FET.
Wider Implications Of The Findings:
This RCT demonstrates that supplementary progesterone likely does not improve live birth rates, and that flexibility in scheduling blastocyst transfers is possible for most women undergoing mNC-FET following their first to third IVF/ICSI treatment. Our results pave the way for a less restricted approach to FET, hence reducing patient burden and costs without compromising success rates.
Study Funding/Competing Interests:
Study funding was from Rigshospitalet's Research Foundation and Gedeon Richter (forward grant, FORWARD2018_5). The funders of the study had no role in study design, data collection, data analysis, data interpretation, writing of this report, or the decision to submit the article for publication. M.S. reports an unrestricted research grant paid to the institution from Gedeon Richter to fund present work, a travel grant from Gedeon Richter paid to the institution, and personal honoraria for lectures from Gedeon Richter and IBSA. L.P. reports payments to the institution for travel from IBSA, Ferring Pharmaceuticals, and Merck, and payments to the institution from Ferring Pharmaceuticals for participation on a data safety monitoring board or advisory board. N.l.C.F. reports research grants paid to the institution from Gedeon Richter, Merck, and Cryos, personal consulting fee from Merck, personal honoraria for lectures from Merck, and travel grants paid to the institution from Merck, Ferring Pharmaceuticals, IBSA, and Gedeon Richter. Additionally, N.l.C.F. is a chair in the steering committee for the guideline groups for the Danish Fertility Society (unpaid). A.K. reports personal honoraria for lectures from Organon and Merck and travel grants paid to the institution from Merck and Ferring Pharmaceuticals. B.O.-M. reports travel grants paid to the institution by Gedeon Richter and personal fees for participation on a data safety monitoring board or advisory board from Ferring Pharmaceuticals. P.H. reports research grants paid to the institution from Merck and Gedeon Richter and personal honoraria for lectures from Merck, IBSA, and Gedeon Richter. E.C.L.L. reports personal honoraria for lectures from Pfizer and Gedeon Richter, travel grants from Merck and Gedeon Richter, and payment to the institution for participation on a data safety monitoring board or advisory board from Astellas Pharma. K.L. reports a research grant paid to the institution from Gedeon Richter, personal consulting fees from Ferring Pharmaceuticals, personal honorarium for a lecture from Ferring Pharmaceuticals, and personal travel grants from Ferring Pharmaceuticals and Merck. A.P. reports research grants from Gedeon Richter, Ferring Pharmaceuticals, and Merck, personal consulting fees from Gedeon Richter, Ferring Pharmaceuticals, and Merck, personal honoraria for lectures from Gedeon Richter, Ferring Pharmaceuticals, Merck, and Abbott, and a travel grant from Gedeon Richter. All other authors declare no competing interests.
Trial Registration Number:
The trial was registered with ClinicalTrials.gov (NCT03795220) and EudraCT (2018-002207-34) and is completed.
Trial Registration Date:
The study was registered at clinicaltrials.gov on 4 December 2018.
Date Of First Patient’S Enrolment:
The first patient was enrolled on 6 January 2019.
More Related Videos
 03:53
Author Spotlight: Regenerative Peripheral Nerve Interface (RPNI) Surgery in Postamputation Pain Management
Published on: March 15, 2024
 08:53
Randomized, Triple-Blind, and Parallel-Controlled Trial of Transcranial Direct Current Stimulation for Cognitive Rehabilitation after Stroke
Published on: June 6, 2025
Related Concept Videos
 02:07
Blind Procedures
 01:28
The Cell Cycle Control System
Cyclins and cyclin-dependent kinases (Cdks) are the primary cell cycle regulators and...
 02:11
The Cell Cycle Control System
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:21
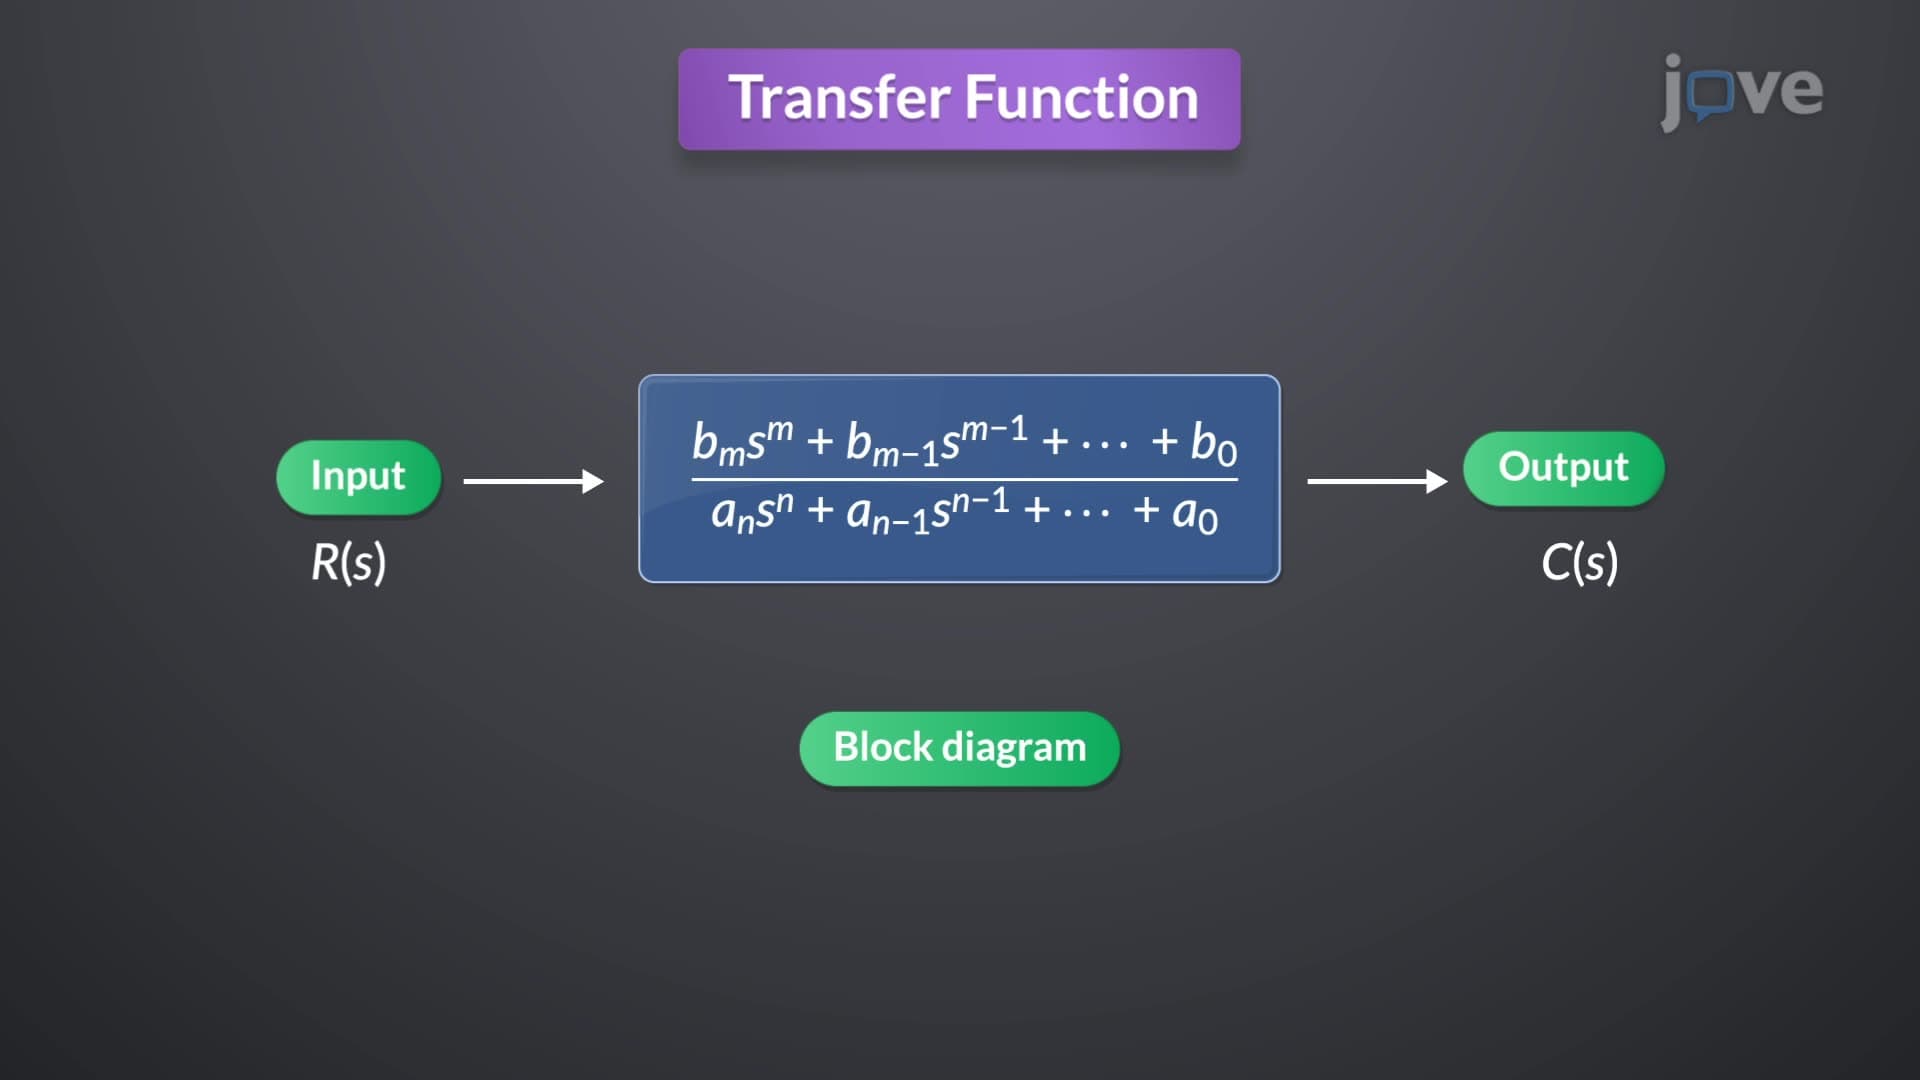
Transfer Function in Control Systems
To derive the transfer function, consider a general nth-order linear time-invariant...
 01:22
Biasing of FET
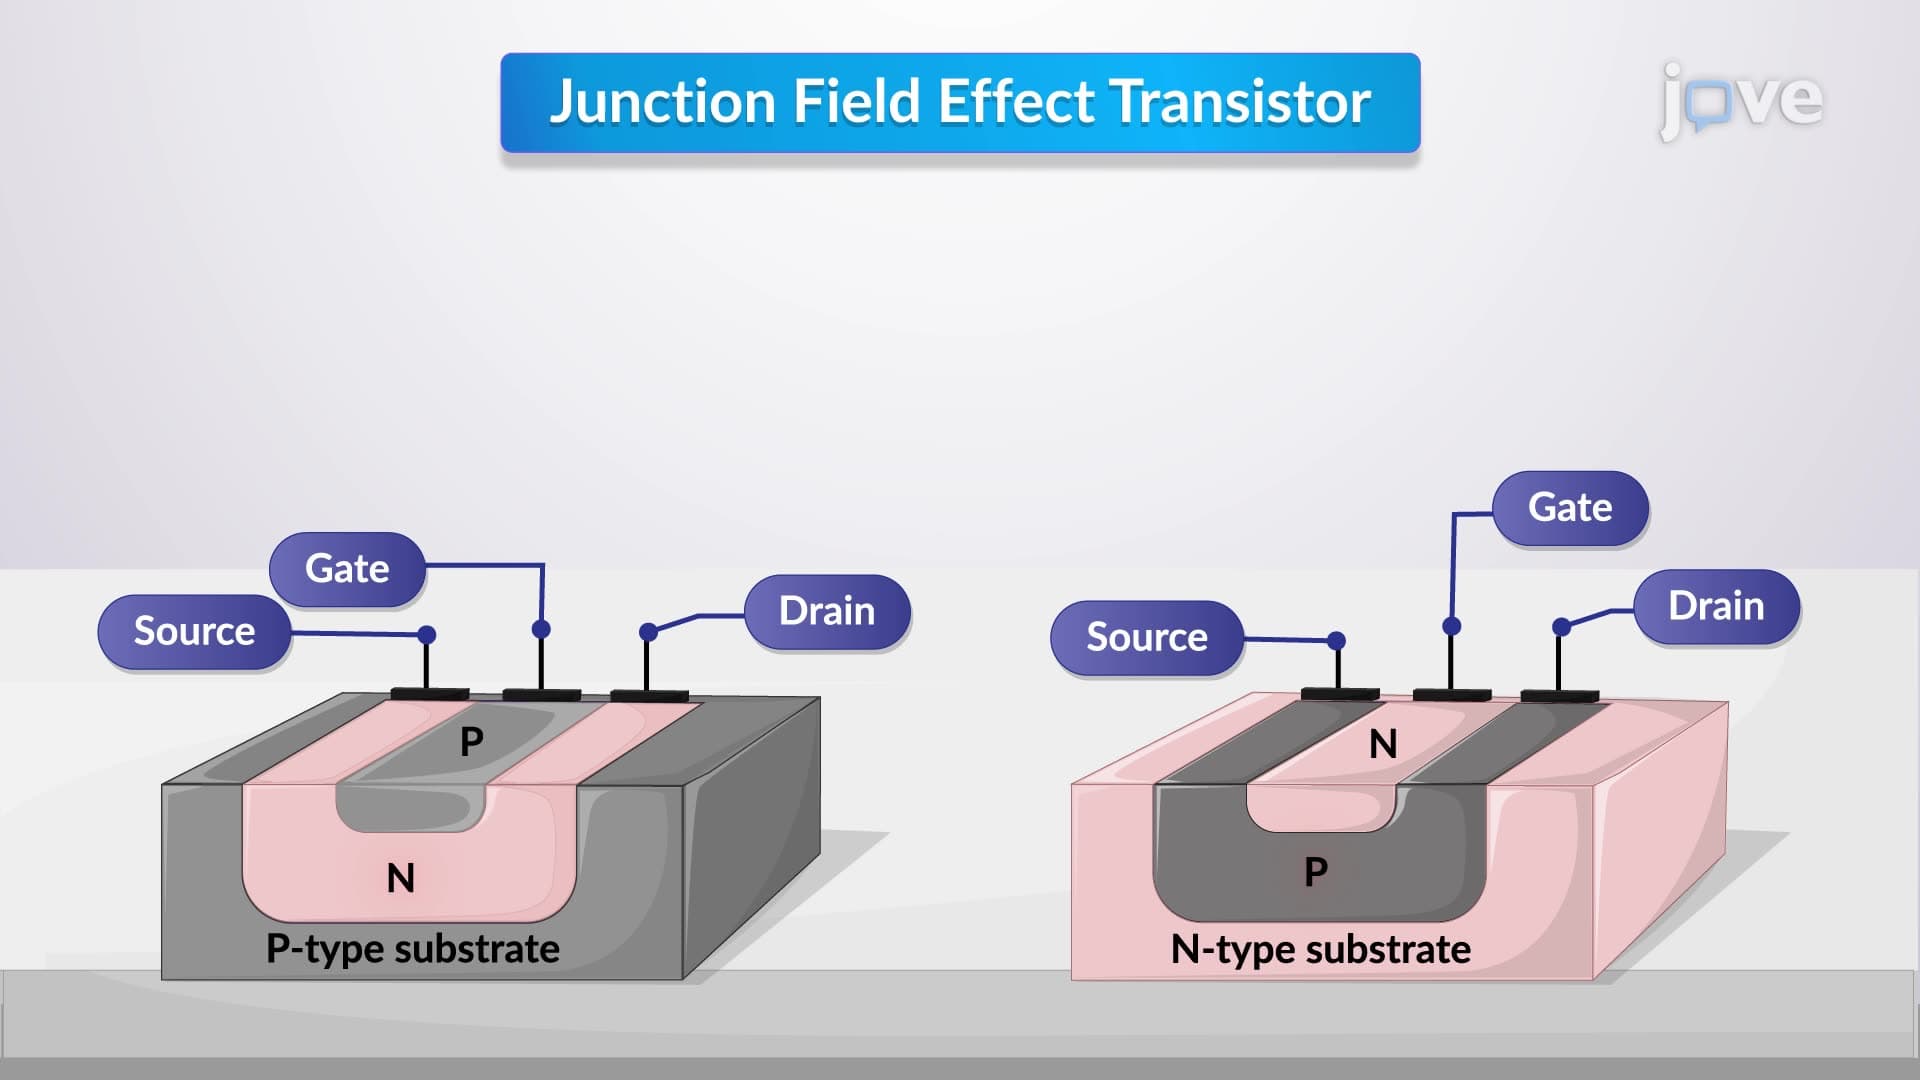
In an N-channel JFET, the structure consists of N-type material forming the channel on a P-type substrate, with the...