Related Experiment Video
Updated: Feb 7, 2026


A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
Morphological Predictors and Preventive Strategies for Type IA and II Endoleaks After Endovascular Aneurysm Repair: A
Antonio Bozzani1, Edoardo Destefanis1, Ilaria Salzillo1
1Vascular and Endovascular Surgery Unit, Fondazione IRCCS Policlinico San Matteo, Pavia, Italy.

Background:
Type IA and type II endoleaks remain among the most frequent and clinically relevant complications following endovascular aneurysm repair (EVAR). These events compromise aneurysm exclusion, may cause sac enlargement, and are associated with an increased risk of late rupture. The ability to identify morphological features predisposing to endoleak formation and to apply targeted preventive strategies could substantially improve the long-term durability of EVAR.
Design:
Single-center retrospective cohort study.
Methods:
We analyzed 250 consecutive patients who underwent EVAR for infrarenal abdominal aortic aneurysm between 2000 and 2019. Patients were divided into 2 periods reflecting the evolution of graft technology and the adoption of preventive measures: period 1 (2000-2014) and period 2 (2015-2019). Preoperative computed tomography angiography was reviewed for aortic neck length and angulation, thrombus burden, and the patency and caliber of lumbar arteries and the inferior mesenteric artery. In period 2, selective embolization of patent branch vessels and the use of fenestrated endografts for short or angulated necks were implemented. Primary outcomes were freedom from type I and II endoleaks and freedom from reintervention.
Results:
Three-year freedom from any endoleak was significantly higher in period 2 (85% vs. 70%, P = 0.03), as was freedom from reintervention (90% vs. 75%, P = 0.02). Short proximal necks (<10 mm; hazard ratio [HR], 3.2; 95% confidence interval [CI], 1.8-5.6), large patent lumbar or mesenteric arteries (>3 mm; HR, 2.7; 95% CI, 1.5-4.9), and sac thrombus involving >50% of the circumference (HR, 1.9; 95% CI, 1.1-3.3) were independent predictors of type I or II endoleaks. Preventive interventions were protective (HR, 0.6, P = 0.04).
Conclusion:
Comprehensive preoperative morphological assessment enables accurate identification of patients at increased risk for endoleak development. A patient-specific, anatomy-driven strategy significantly improves long-term endoleak-free and reintervention-free survival after EVAR.
More Related Videos
 07:21
Microsurgical Creation of Giant Bifurcation Aneurysms in Rabbits for the Evaluation of Endovascular Devices
Published on: September 8, 2023
 09:32
Time-Resolved, Dynamic Computed Tomography Angiography for Characterization of Aortic Endoleaks and Treatment Guidance via 2D-3D Fusion-Imaging
Published on: December 9, 2021
Related Concept Videos
 01:08
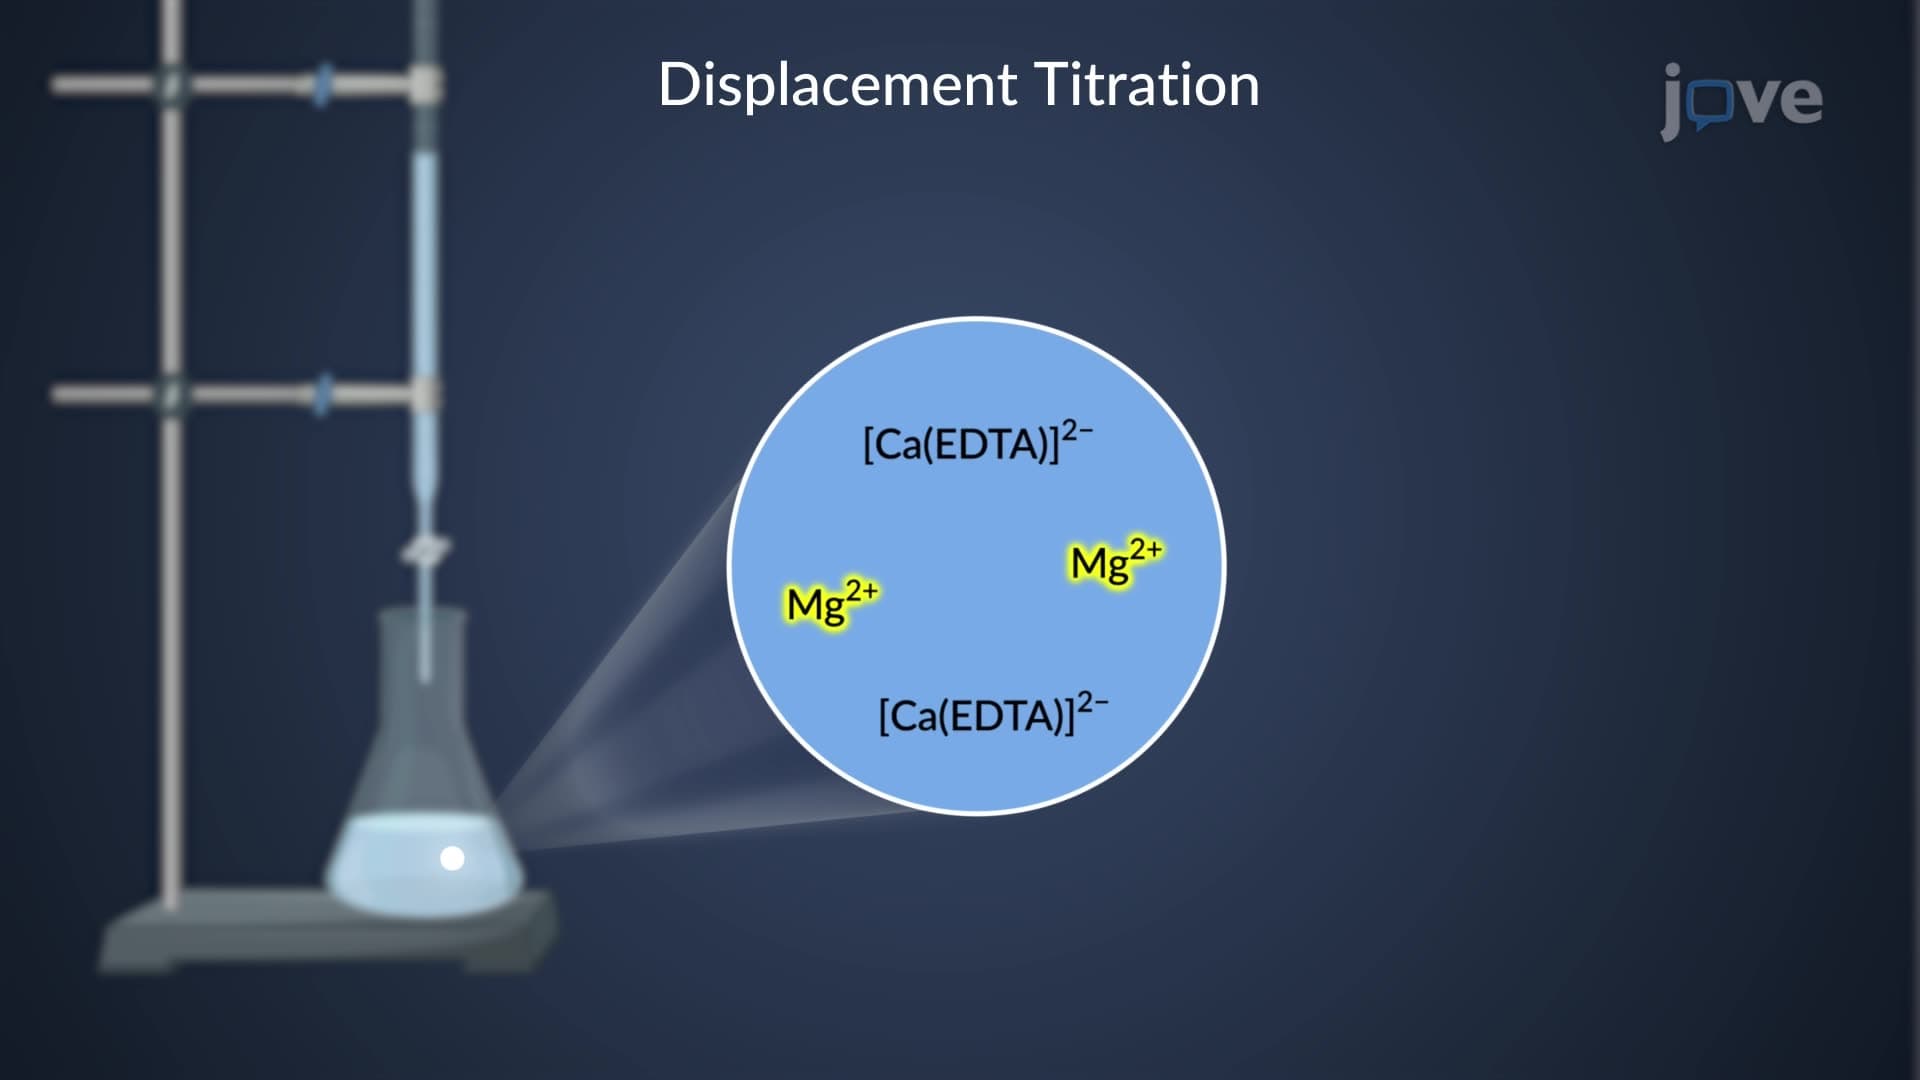
Titrimetric Methods: Types and Commonly Used Strategies
 02:25
Overview of DNA Repair
Chemically...
 01:36
Mismatch Repair
 01:02
Long-patch Base Excision Repair
 01:08
Nucleotide Excision Repair
 01:54
Base Excision Repair
The first step of...