Related Experiment Video
Updated: Feb 7, 2026
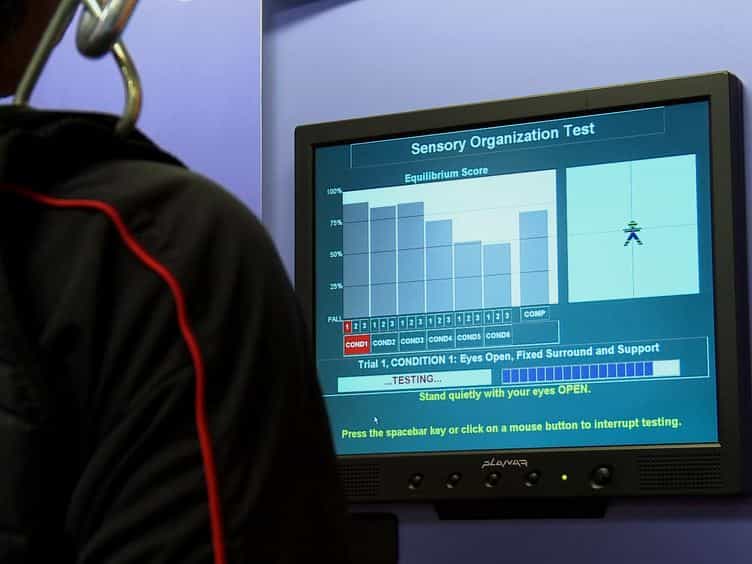

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Validation of the Society for Vascular Surgery Appropriate Use Criteria for management of intermittent claudication
Alejandro A Vega1, Christine Mavilian1, Olamide Alabi2
1Division of Vascular Surgery, Department of Surgery, University of California, Los Angeles, Los Angeles, CA.

Objective:
The aim of this study was to perform a multi-institutional retrospective validation of the Society for Vascular Surgery Appropriate Use Criteria (AUC) for management of intermittent claudication (IC).
Methods:
A retrospective review of patients treated for IC from 2005 to 2024 was performed across seven institutions. Inclusion criteria followed AUC assumptions. All treated limbs were rated as appropriate (benefit outweighs risk [B>R]), indeterminate (IND) or inappropriate (R>B) per the original AUC by two authors, who resolved discrepancies through discussion. Analysis was performed on the patient level. If one limb was rated as R>B, the patient was rated as R>B. For the purposes of comparison, B>R and IND were grouped together (B>R/IND).
Results:
A total of 372 patients were included. The median follow-up was 1190 days (interquartile range, 433-2115 days). Treatment was classified as B>R/IND in 245 patients (66%) and R>B in 127 (34%). More patients in the R>B group identified as Black (12.7% vs 6.7%) and Hispanic (19.8% vs 9.2%) (P = .006). Fewer patients in the R>B group were on optimal medical therapy at the time of evaluation (58.3% vs 75.9%; P < .01). More patients in R>B had mild or moderate lifestyle limitations (93.7% vs 68.6%; P < .01) and fewer patients in R>B had exercise therapy prior to revascularization (22% vs 54%; P < .01). The most affected segments were aortoiliac (30.9%) and femoropopliteal (49.7%). Revascularization was performed in 231 patients (104 B>R/IND and 127 R>B). Of the patients who underwent revascularization, 149 underwent unilateral revascularization, and 82 underwent bilateral revascularization. Interventions were most often performed in the femoropopliteal (48.1%) and aortoiliac (35.1%) segments. At 2 years from initial consultation with the vascular surgeon, 19% in the R>B group were free from revascularization compared with 57% in the B>R/IND group (P < .01). Freedom from symptom recurrence at 2 years was lower in the R>B group but did not reach statistical significance (48.9% vs 60%; P = .07). Freedom from reintervention at 2 years following revascularization was significantly lower in the R>B group (64% vs 84%; P = .01). A total of 10 major amputations and 11 minor amputations occurred in 17 patients (4.6%) over the study period. Among patients who had mild/moderate lifestyle limitations and were classified as R>B, 15 (11.8%) underwent nine minor amputations and 10 major amputations. Among patients who had mild or moderate lifestyle limitations and were classified as B>R/IND, no patients underwent any type of amputation.
Conclusions:
In this retrospective multi-institutional cohort, patients with IC who were treated inappropriately (R>B) per the Society for Vascular Surgery AUC experienced significantly worse outcomes compared with those who received appropriate/indeterminate (B>R/IND) treatment.
More Related Videos
 05:15
Author Spotlight: Accessible M&M-Based Mouse Model for Investigating Binge Eating Disorder - Insights into Eating Behaviors, Anxiety, and Neural Mechanisms
Published on: January 10, 2025
 08:06
Assessment of the Metabolic Effects of Isocaloric 2:1 Intermittent Fasting in Mice
Published on: November 27, 2019
Related Concept Videos
 01:28
Criteria for Causality: Bradford Hill Criteria - II
 01:30
Criteria for Causality: Bradford Hill Criteria - I
 01:29
Reliability and Validity
 03:24
Seedless Vascular Plants
 01:15
Data Validation
Key parameters for method validation include:
 01:03
Data Validation
Nursing assessment guides are generally based on holistic models rather than medical...