Related Experiment Video
Updated: Feb 7, 2026


A Novel Digital Platform for a Monitored Home-based Cardiac Rehabilitation Program
Published on: April 19, 2019
Surveillance practices of pediatric intestinal failure patients by North American intestinal rehabilitation programs
Christina Belza1,2, Glenda Courtney-Martin1,2,3,4,5, Yaron Avitzur1,2,5
1Group for Improvement of Intestinal Function and Treatment (GIFT), The Hospital for Sick Children, Toronto, Canada.

Insights
Pediatric intestinal failure (IF) patients on long-term parenteral nutrition (PN) have varied monitoring practices. A consensus on surveillance is needed to improve outcomes and prevent complications in IF management.
Area of Science:
- Pediatric Gastroenterology
- Clinical Nutrition
- Health Services Research
Background:
- Improved survival in pediatric intestinal failure (IF) necessitates long-term parenteral nutrition (PN).
- Current monitoring practices for IF patients lack standardization, hindering complication prevention.
- North American intestinal rehabilitation programs (IRPs) require evaluation for surveillance consistency.
Purpose of the Study:
- To assess current surveillance practices in North American IRPs for children with IF on PN.
- To identify variations in monitoring for potential complications.
- To highlight the need for standardized surveillance protocols.
Main Methods:
- A cross-sectional survey was distributed to IRPs in Canada and the United States.
- Data collected included program demographics and surveillance of various health parameters (e.g., liver function, bone health, neurocognition).
- Responses were analyzed descriptively, stratifying programs by patient volume.
Main Results:
- Fifty-one percent of surveyed IRPs responded, representing 971 patients on PN.
- Significant variation exists in monitoring practices, with only 2 programs reporting renal function evaluation.
- Routine abdominal ultrasounds (79.2%) and venous patency monitoring (72%) were common, but bone health, neurocognitive, and quality of life assessments varied widely.
Conclusions:
- Wide variability in surveillance practices exists among pediatric IRPs in North America.
- Evidence-based data is crucial to support the development of standardized surveillance protocols.
- A consensus surveillance schedule could enhance early complication detection and management, improving patient outcomes.
Introduction:
Advancements in the survival of pediatric intestinal failure (IF) has resulted in a larger population of children requiring long-term parenteral nutrition (PN). Monitoring to prevent or address complications is vital in IF management, but currently there is no consensus on what to monitor or frequency. Our objective was to determine surveillance practices in North American (Canada and the United States) intestinal rehabilitation programs (IRPs).
Material And Methods:
A cross-sectional survey was completed using a questionnaire developed by our center. Surveys were emailed to centers identified from the American Society of Parenteral and Enteral Nutrition IF working group. Data collected included program demographics and surveillance of liver and renal function, venous patency, bone health, macro- and micronutrients, growth, neurocognitive development, and quality of life (QoL). Descriptive analysis was performed on pooled responses with programs stratified into those with greater and lesser than 50 patients on home PN.
Results:
Twenty-five of 49 programs (51 %) responded with a total representation of 2995 patients including 971 patients on PN. Twenty IRPs (79.2 %) perform routine abdominal ultrasounds, however only 2 programs report evaluation of renal function. Eighteen IRPs (72 %) monitor venous patency and 56 % have schedule to evaluate bone health. Five programs (20 %) report formal neurocognitive follow up and 25 % monitor child and family QoL.
Conclusion:
There is wide variation in surveillance practices among Canada and US based pediatric IRPs. Data to support surveillance practices is needed. A consensus surveillance schedule could ensure early recognition and mitigation of complications to help improve outcome in this population.


Related Concept Videos
 01:23
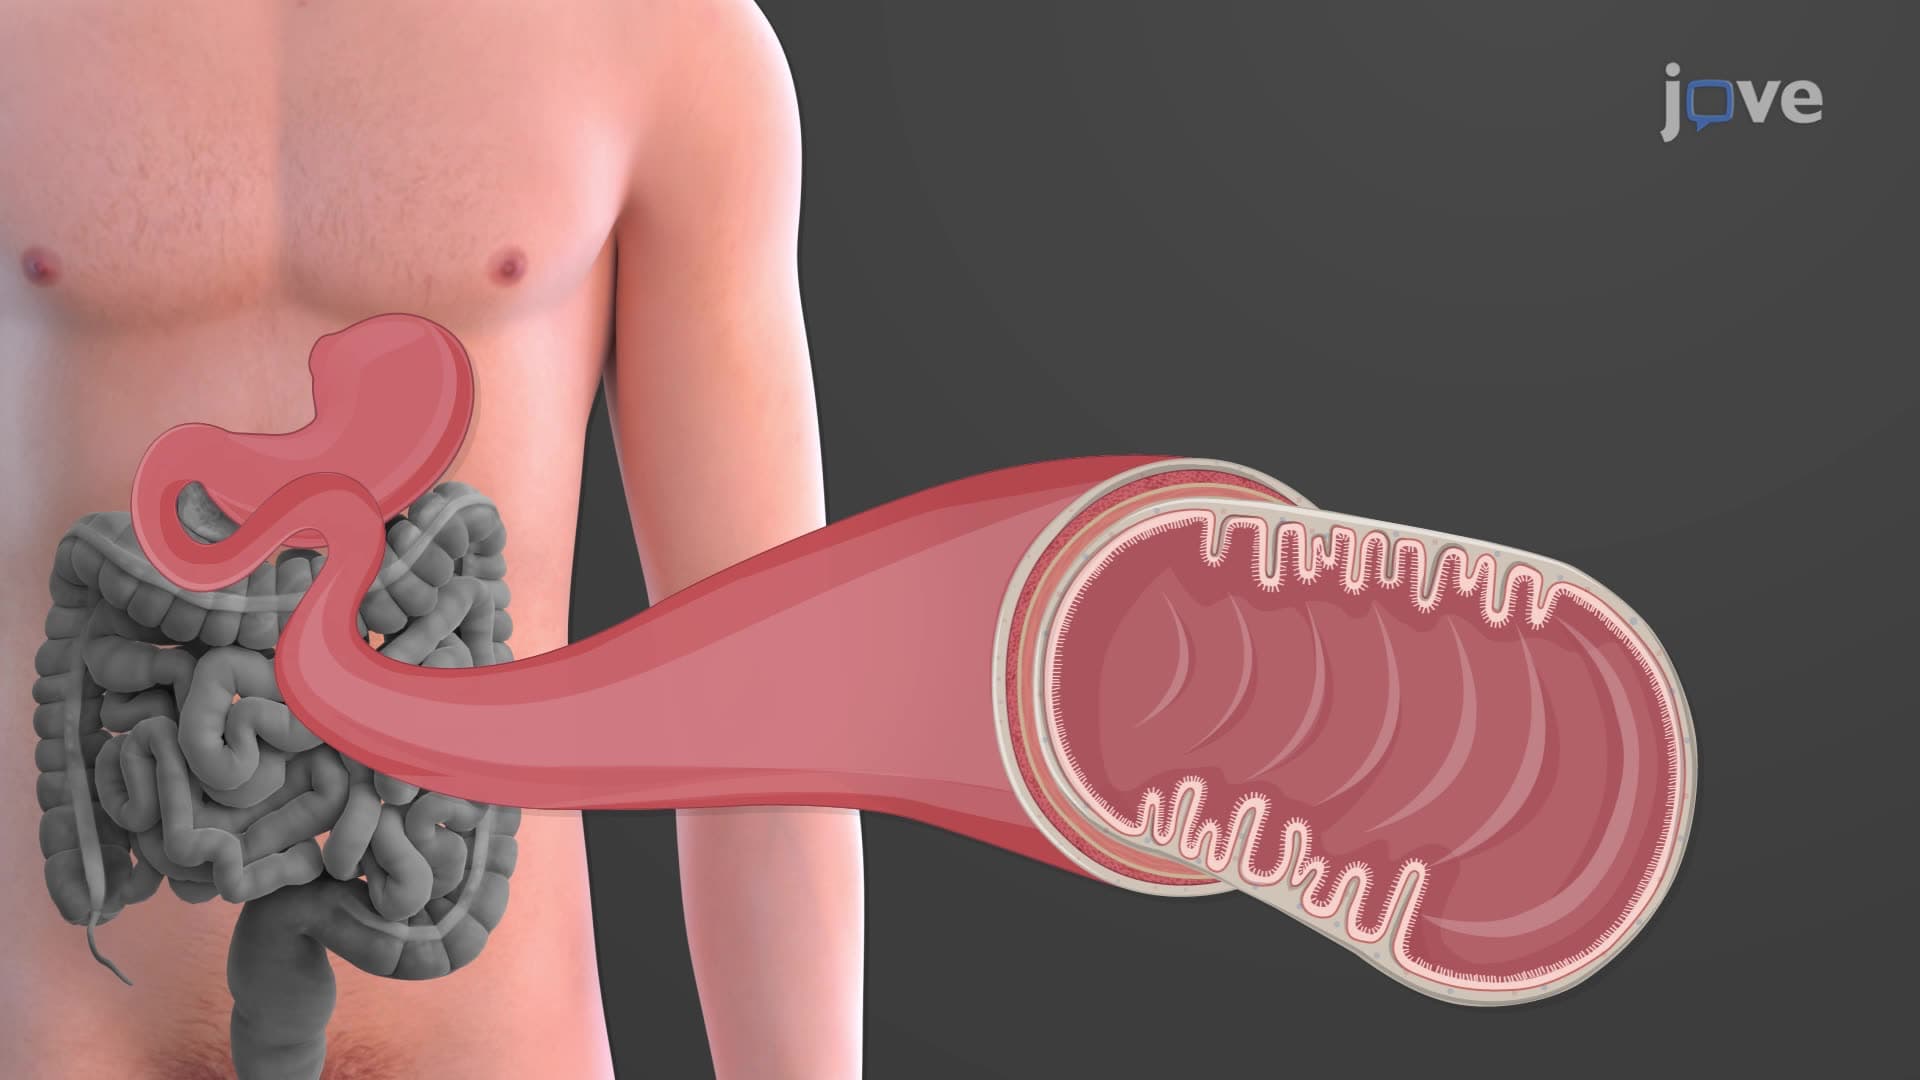
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:15
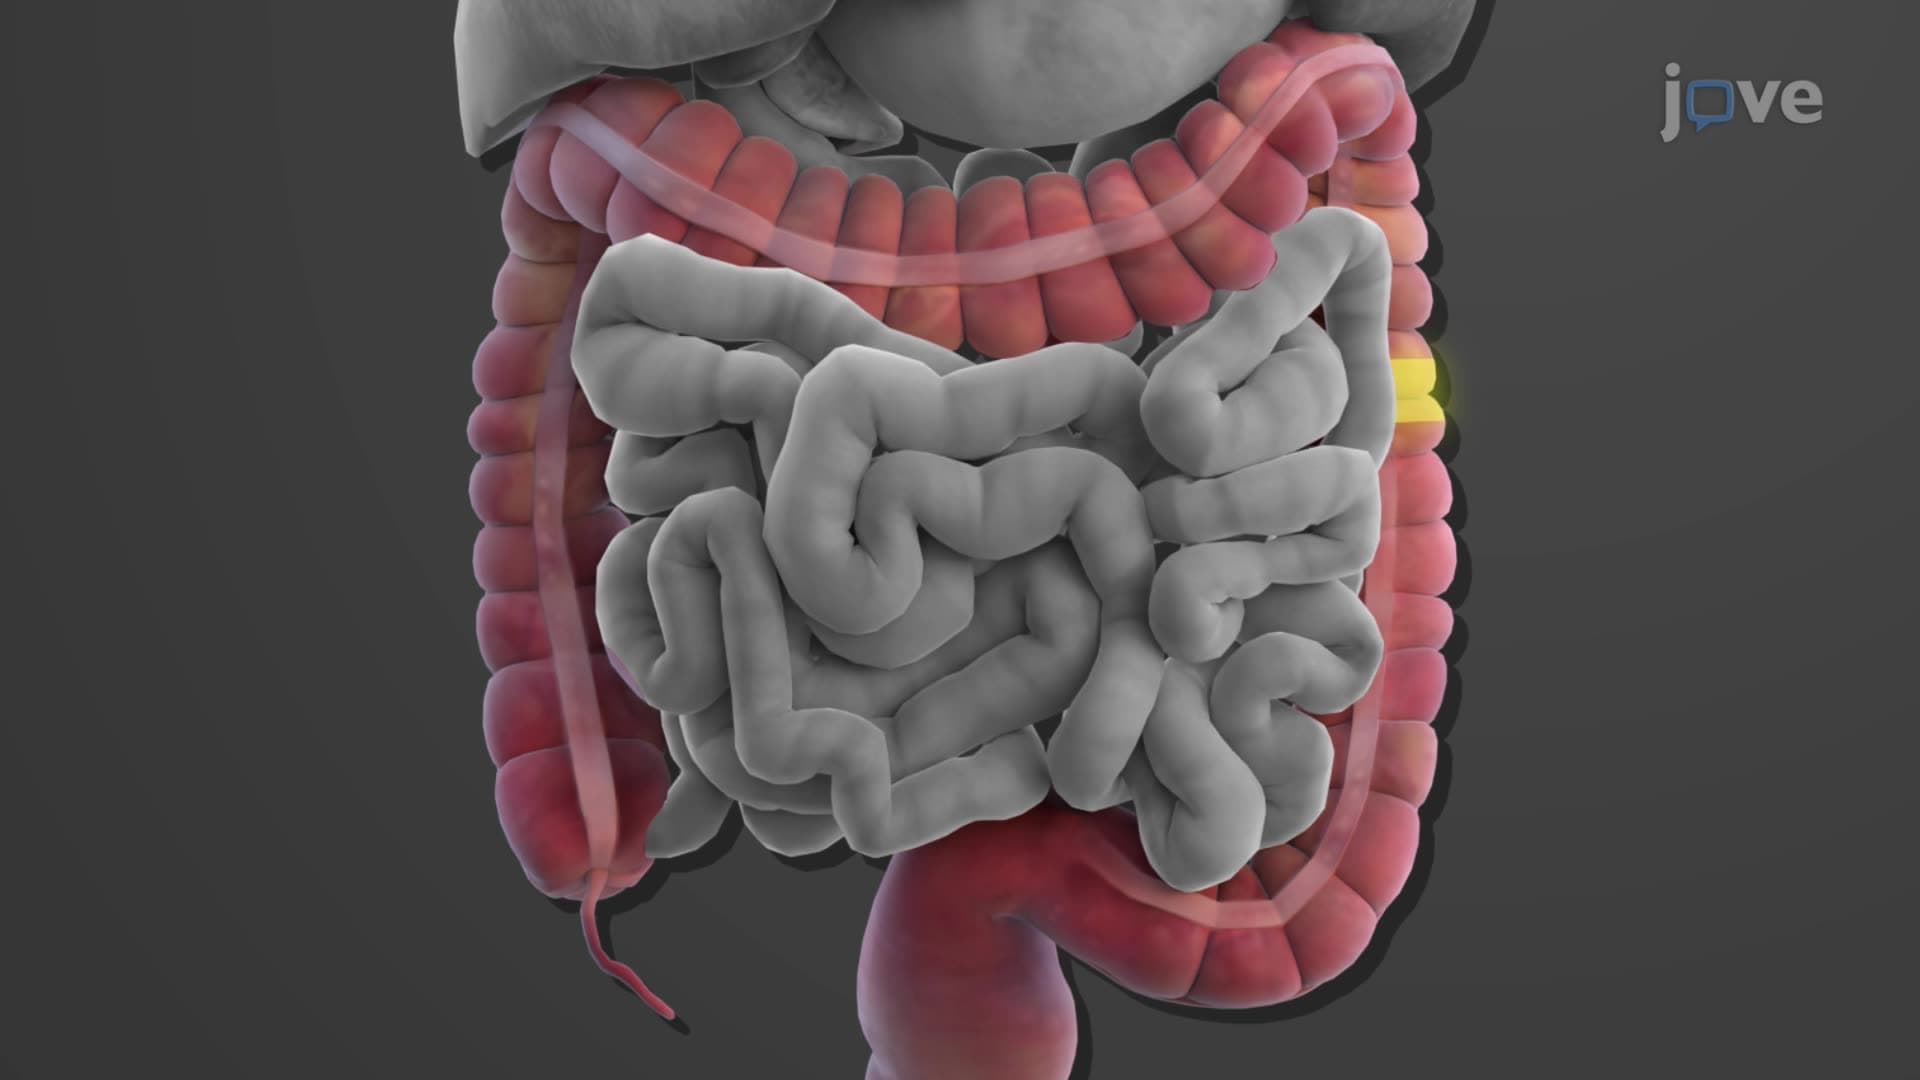
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
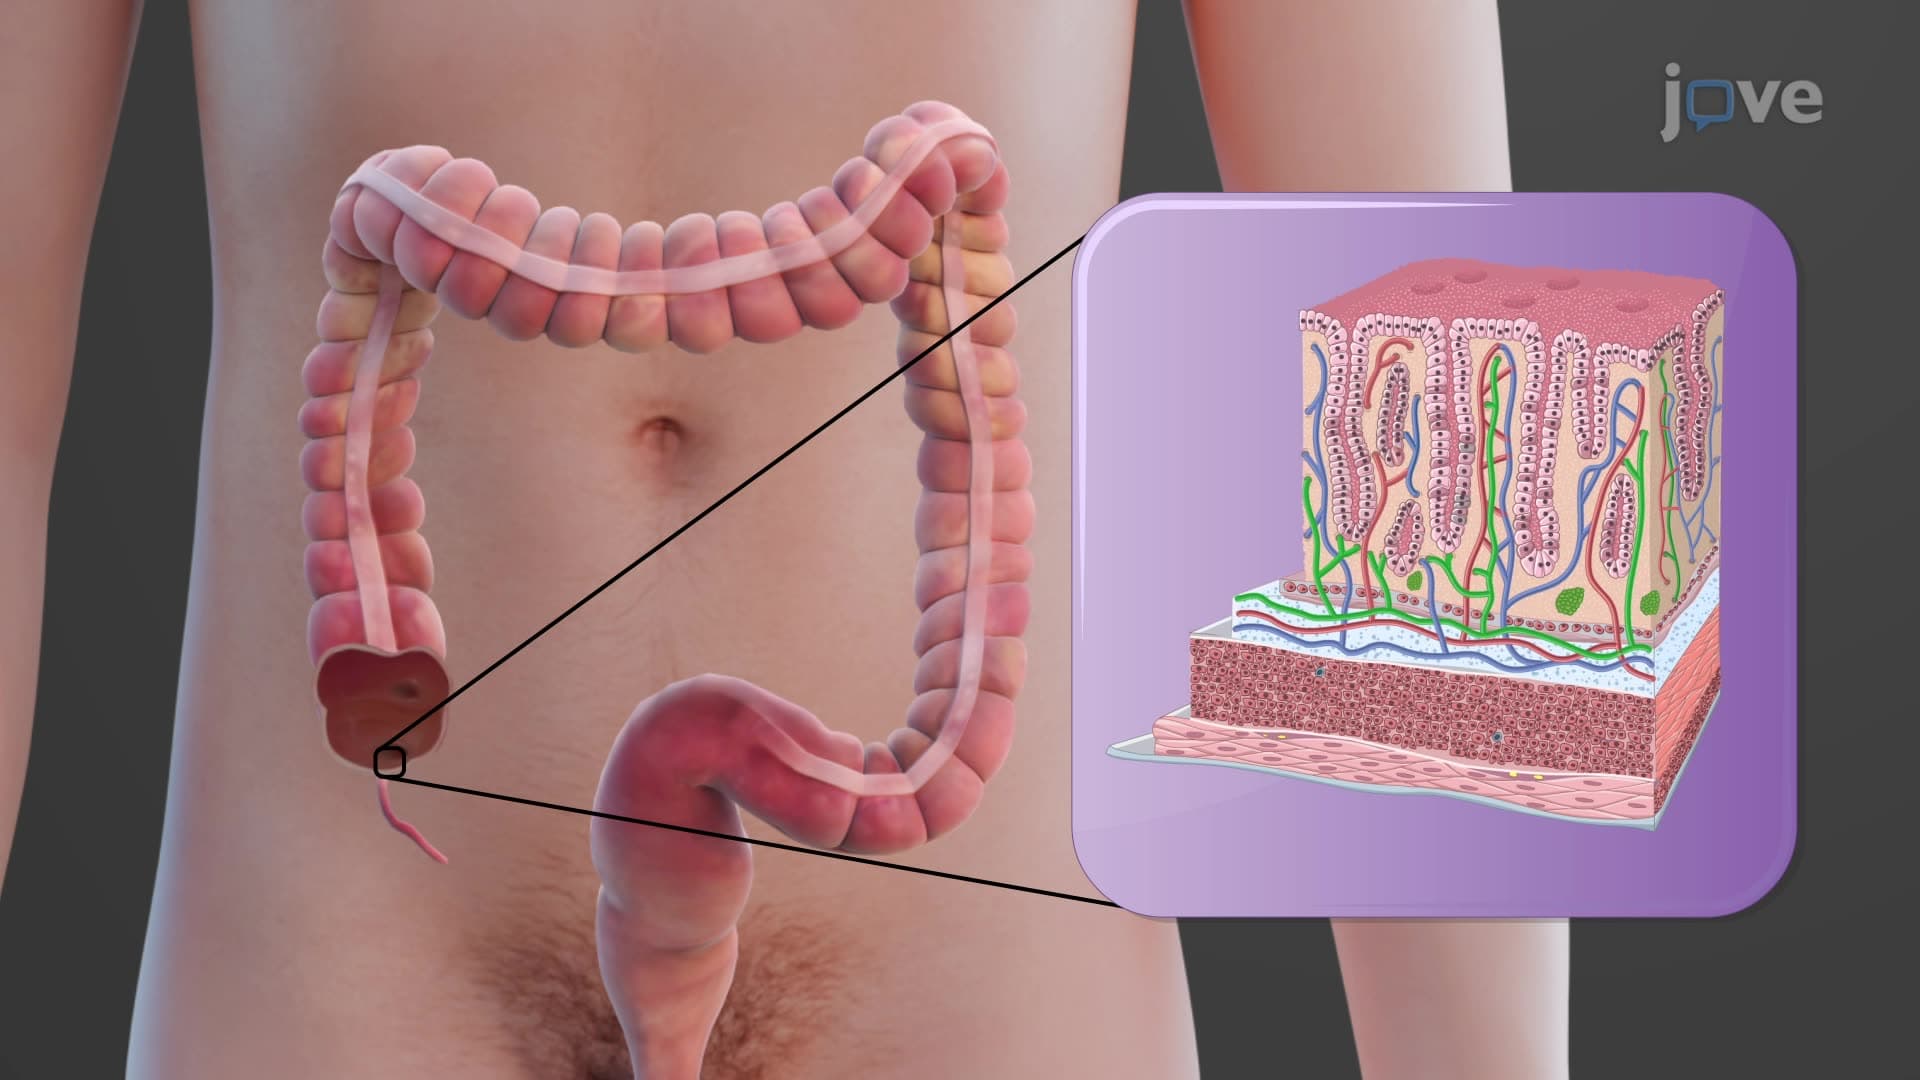
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
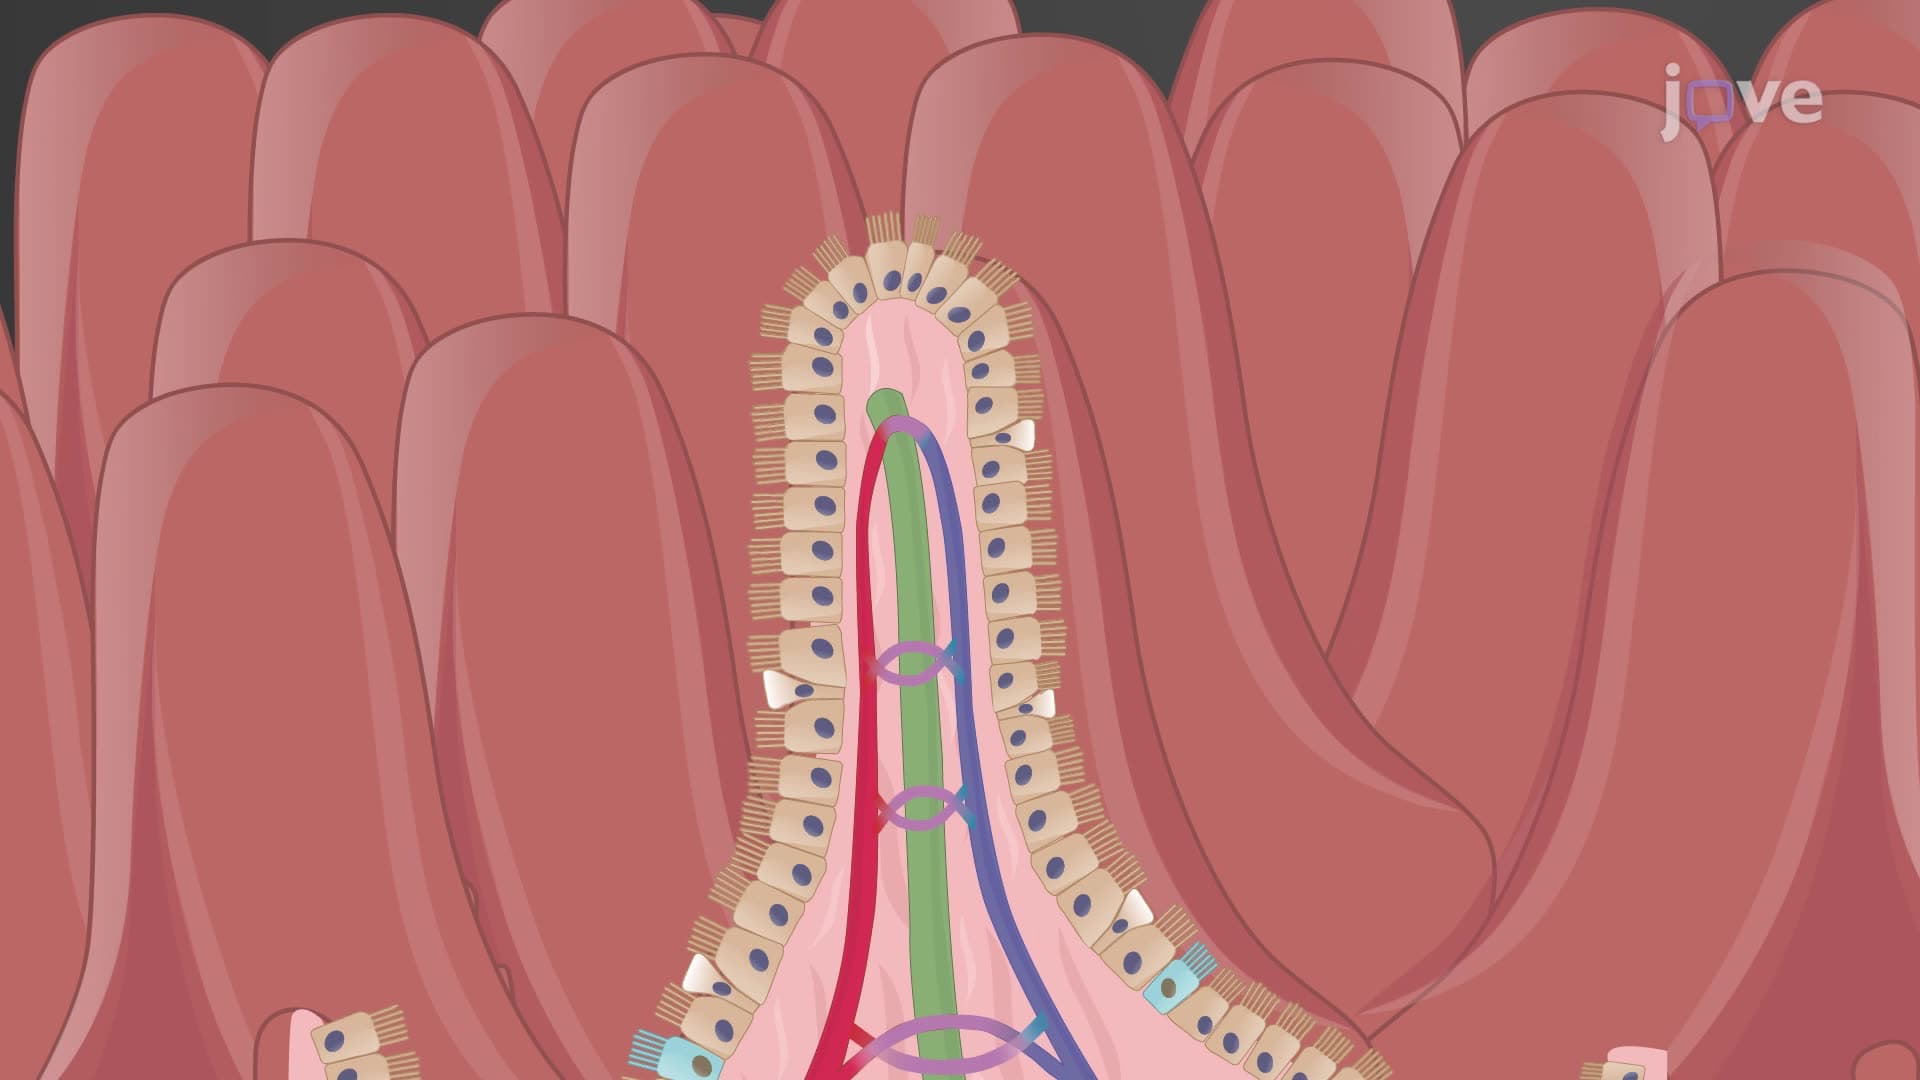
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:29
Bacterial Flora of the Large Intestine
The normal gut flora of the colon plays a critical role in generating essential vitamins such as vitamins K, B5, and B7.