Related Experiment Video
Updated: Feb 8, 2026


Murine Model of Leukemia Relapse to Induction Chemotherapy for Acute Lymphoblastic Leukemia
Published on: October 17, 2025
Varnimcabtagene autoleucel for adults with relapsed or refractory B-cell precursor acute lymphoblastic leukaemia in
Valentín Ortiz-Maldonado1, Núria Martínez-Cibrian1, Leticia Alserawan2
1Department of Haematology, Hospital Clínic de Barcelona, Barcelona, Spain; Fundació de Recerca Clínic Barcelona-Institut d'Investigacions Biomèdiques August Pi i Sunyer, Barcelona, Spain; University of Barcelona, Barcelona, Spain.

Background:
Varnimcabtagene autoleucel (var-cel) is an autologous CD19-directed chimeric antigen receptor (CAR) T-cell therapy with adaptive intra-patient dose escalation and was approved in Spain in 2021 for patients older than 25 years with relapsed or refractory B-cell precursor acute lymphoblastic leukaemia. We report activity and safety from var-cel's pivotal trial in this patient population.
Methods:
This multicentre, single-arm, phase 2 trial was conducted at nine academic centres in Spain. Eligible patients had CD19+ B-cell precursor acute lymphoblastic leukaemia in the first relapse or refractory disease, either ineligible for allogeneic haematopoietic cell transplantation (HCT) or with relapsed disease after allogeneic HCT; centralised measurable disease in peripheral blood or bone marrow, or both, using flow cytometry; were aged 18-70 years; and had an Eastern Cooperative Oncology Group performance status of 0-2. Patients received a single course of intravenous lymphodepleting chemotherapy with fludarabine (30 mg/m2 per day for 3 days) plus cyclophosphamide (300 mg/m2 per day for 3 days), followed by intravenous fractionated var-cel escalation (0·1, 0·3, 0·6, and 2·0 × 106 CAR T cells per kg) separated by at least 24 h, with each fraction contingent on safety criteria. The primary endpoint was complete response with undetected measurable residual disease (MRD; sensitivity of ≤10-5) determined by flow cytometry by day 28 from var-cel administration, assessed in the efficacy population (defined as all patients who received at least one var-cel fraction). Safety was analysed in patients that initiated lymphodepletion. This study is registered with ClinicalTrials.gov, NCT04778579 (completed).
Findings:
Between May 19, 2021, and July 6, 2023, 50 patients were assessed for eligibility, 12 were ineligible, and 38 were enrolled. 37 (97%) of 38 underwent leukapheresis (ITT population), 33 (87%) initiated lymphodepleting chemotherapy (safety population), and 32 (84%) received at least one var-cel fraction (efficacy population). Five patients who underwent leukapheresis did not receive var-cel due to rapid disease progression (n=3), death due to veno-oclusive disease (n=1), and persistent COVID-19 (n=1). Patients receiving var-cel had a median age of 40 years (33-48); of whom, 16 (50%) were female and 16 (50%) were male. By data cutoff (Jan 18, 2024), the median follow-up from infusion was 8·6 months (IQR 5·1-14·4) and 27 (84·4% [95% CI 67·2-94·7]) of 32 patients who received at least one dose of var-cel had a complete response with undetected MRD by day 28. Treatment-emergent adverse events occurred in 31 (94%) of 33 patients. The most common grade 3 or higher adverse events were neutropenia in 15 (45%) patients, thrombocytopenia in seven (21%), anaemia in five (15%), and cytokine release syndrome in four (12%). Immune effector cell-associated neurotoxicity syndrome and cerebral oedema was observed in one patient (3%; grade ≥3), and immune effector cell-associated hemophagocytic lymphohistiocytosis-like syndrome occurred in two (6%; one resulted in death after protocol violation due to infusion during uncontrolled sepsis).
Interpretation:
Var-cel induced deep remissions with low incidence of severe cytokine release syndrome and any-grade immune effector cell-associated neurotoxicity syndrome, supporting fractionated dose escalation as a strategy that preserves activity, limits acute toxic effects, and supports a hospital-based approach that could expand access to CAR T-cell therapy.
Funding:
Instituto de Salud Carlos III Subdirección General de Evaluación y Fomento de la Investigación Sanitaria and Fondo Europeo de Desarrollo Regional, CaixaResearch, Servei Català de la Salut, Servicio Madrileño de Salud, Servicio Murciano de Salud, Salud de Castilla y León, Servicio Andaluz de Salud, and Servicio Navarro de Salud-Osasunbidea.
Translation:
For the Spanish translation of the abstract see Supplementary Materials section.

Related Concept Videos
 01:28
Inductance: Single-Phase And Three-Phase Line
Single-Phase Two-Wire Line:
A single-phase line consists of two solid cylindrical conductors, denoted as x and y. Each conductor carries phasor currents ix and iy, respectively. Given that the sum of these currents is...
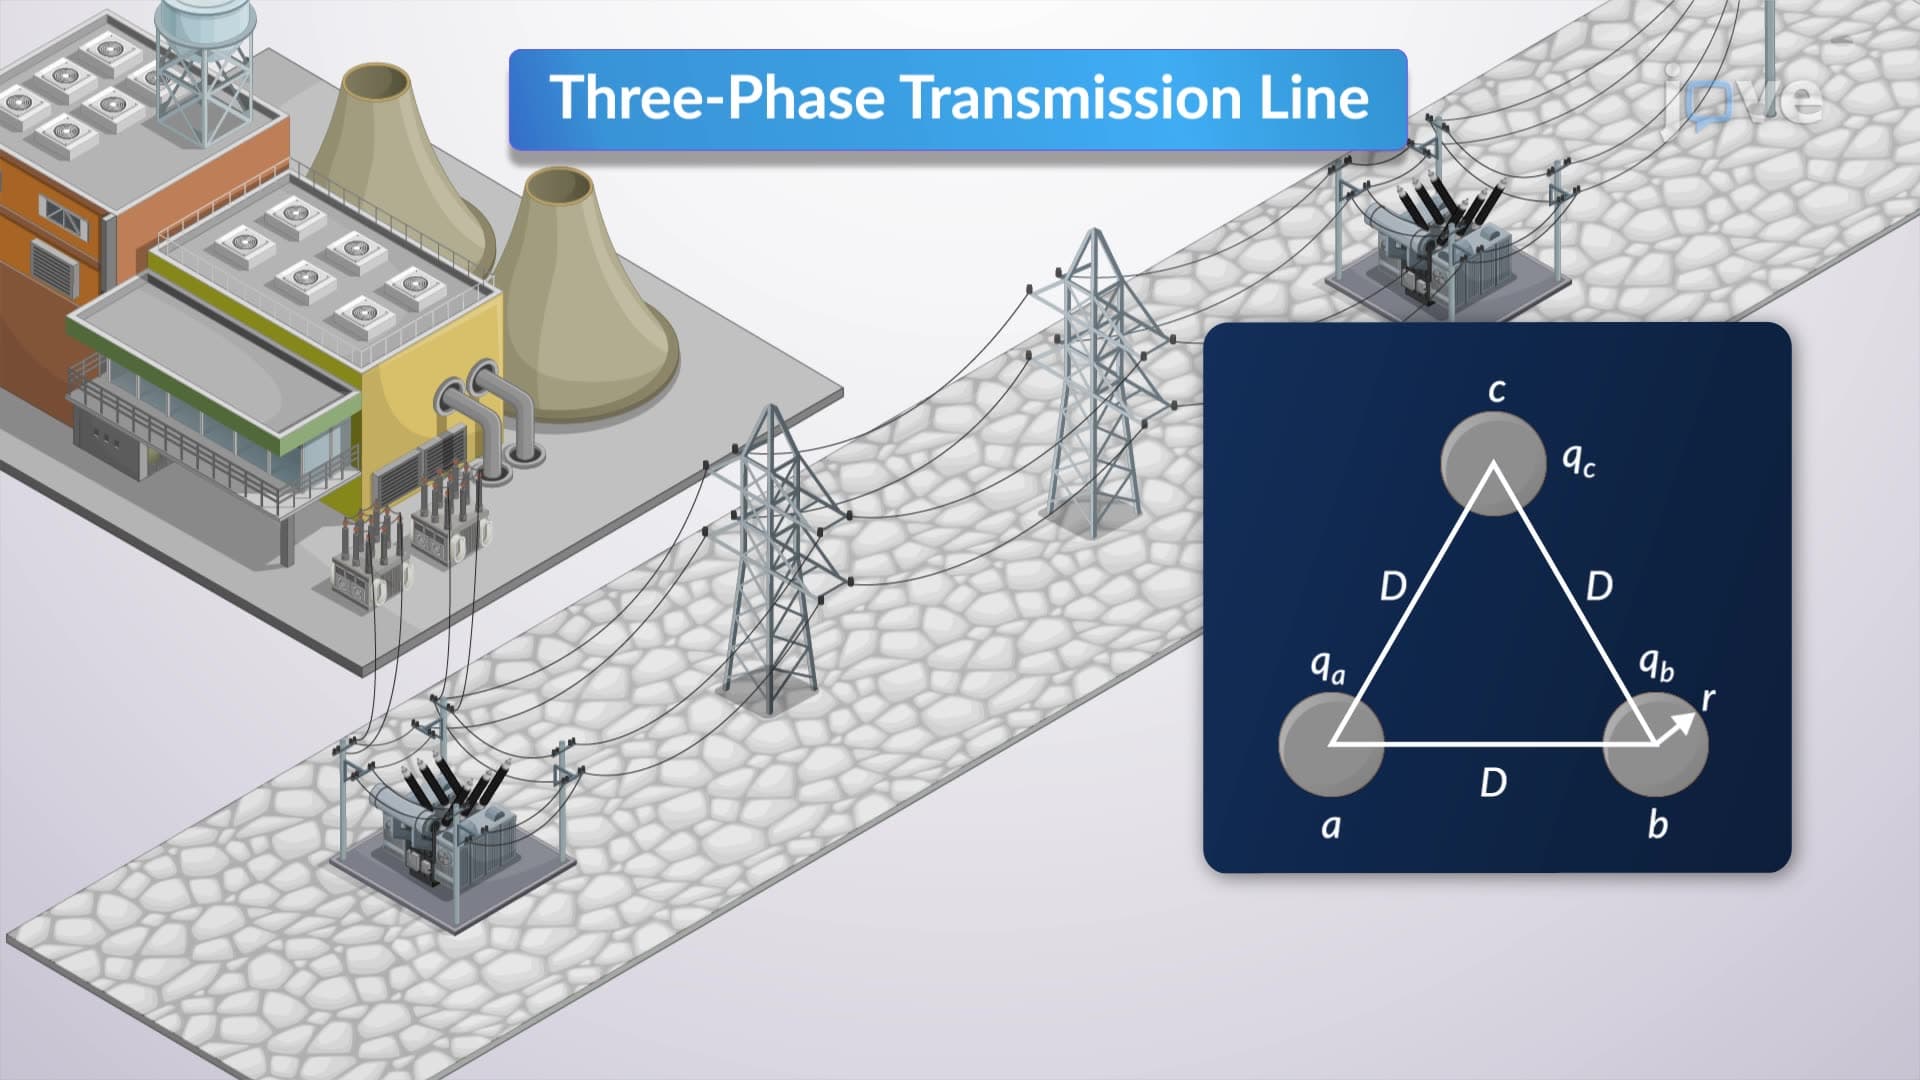 01:25
Capacitance: Single-Phase And Three-Phase Line
Single-Phase Lines
Consider a single-phase, two-wire transmission line with equal phase spacing energized by a voltage source. One conductor carries a uniform positive charge, while the other carries an equal negative charge. The capacitance C of the line can be derived from the voltage V between the conductors. For a one-meter section of the line, the capacitance is given...
 01:17
Power Distribution in Three-phase and Single Phase Circuits
Single-Phase Power Distribution:
Single-phase circuits are typical in household settings;...
 01:33
Adult Stem Cells
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:11
Clinical Trials: Overview